Shared course · by demo

Nutrition basics: how the body uses food

Understand macronutrients, energy balance, and how to read a nutrition label and a study headline without being taken in by either.

lessons
61
to learn
16h 54m
questions
193
written
61/61
Start reading BeginnerEnglish

The path

WrittenNot yet

  1. The energy equation: calories in, calories out25 min2 questions
  2. What is a calorie?10 min4 questions
  3. Basal metabolic rate12 min2 questions
  4. Thermic effect of food10 min3 questions
  5. Physical activity energy15 min3 questions
  6. Energy balance and weight change12 min3 questions
  7. The three macros: protein, fat and carbohydrate30 min4 questions
  8. Protein: building and repairing12 min3 questions

Lesson 1

The energy equation: calories in, calories out

You will be able to state what a calorie measures and how energy balance determines weight change. Covers the definition of a kilocalorie, basal metabolic rate, the thermic effect of food, and physical activity. Prevents the belief that a calorie is a physical object rather than a unit of heat.

25 min2 assessments

Your body runs on energy. Every bite of food and every sip of drink delivers energy, and every thought, heartbeat, step, and breath burns it. The difference between what comes in and what goes out is called energy balance, and it's the core reason your body weight changes.

A calorie is simply a unit of heat energy – the amount needed to raise one kilogram of water by one degree Celsius. It is not a substance, a toxin, or something you “burn off” as if it were wood. When a food label says 200 calories (which is really 200 kilocalories in scientific terms), it tells you how much energy your body can extract from that food for work, warmth, or storage.

The energy equation is straightforward:

Energy In (food + drink) = Energy Out (basal metabolism + digestion cost + physical activity)

  • Energy In comes from the macronutrients in what you eat and drink.
  • Energy Out is the sum of:
  • Your basal metabolic rate – the energy your organs and cells need just to keep you alive at rest.
  • The thermic effect of food – the energy your body spends digesting and processing what you ate.
  • Physical activity – every movement, from fidgeting to running.

When Energy In equals Energy Out, your weight stays steady. When In exceeds Out, your body stores the surplus (mostly as fat). When Out exceeds In, your body taps into its stored energy, and you lose weight. The direction depends on the balance, not on any single food or exercise.

This section gives you the mental model. Later nodes will break down each component so you can estimate your own numbers.

The energy balance equation: what comes in versus what goes out determines whether the body stores or burns energy.

Analogy

Think of your body as a bank account. Calories are the currency. Every time you eat, you make a deposit. Every time you move, breathe, digest, or even think, you make a withdrawal. Your body weight is the account balance.

  • Surplus (more deposits than withdrawals) – your balance goes up. The extra energy is stored as fat, like cash sitting in a savings account.
  • Deficit (more withdrawals than deposits) – your balance goes down. The body writes cheques against its stored energy (fat and some glycogen) to cover the gap.

This analogy helps you remember that weight change is a mathematical consequence of net flow, not a moral judgment or a mysterious process.

Where the analogy breaks down

A bank account earns interest and allows overdrafts in ways that don't match human metabolism. Your body doesn’t just linearly add or subtract calories; it adapts. If you starve it, your metabolic rate slows down to conserve energy (the bank doesn't penalize you for low balance). Also, the body can’t ‘borrow’ energy from future deposits – deficits must be covered right now from what’s stored. And unlike a bank, the type of deposit (protein vs. fat) affects how much energy it costs to process (the thermic effect of food). The analogy is useful for the big picture but fails for the details.

  • A calorie is a unit of energy, not a substance – it measures the heat required to raise 1 kg of water by 1°C.
  • Energy balance is the difference between calories consumed (food and drink) and calories expended (basal metabolism + digestion + physical activity).
  • When energy in equals energy out, body weight is stable.
  • A sustained surplus of energy in over out leads to weight gain (energy stored, mostly as fat).
  • A sustained deficit leads to weight loss (energy drawn from stored reserves).
  • The three main components of energy out are basal metabolic rate, the thermic effect of food, and physical activity – each will be covered in detail next.
Check yourself

Check your understanding of the energy equation.

1Multiple choiceChecked instantly

Which of the following best describes a calorie in the context of nutrition?

  • AA calorie is a unit of weight, like a gram, used to measure how heavy a food is.
  • BA calorie is a unit of energy, specifically the heat needed to raise 1 kg of water by 1°C.
  • CA calorie is a chemical compound found in fat that makes you gain weight.
  • DA calorie is the same thing as a kilojoule – they are just two names for the same unit.
2Short answerMarked by AI

A person consumes 2,500 kcal per day and expends 2,200 kcal per day. Describe the energy balance and predict what will happen to their body weight over several weeks if this pattern continues. Explain the reasoning in 2–4 sentences.

Graded on Identifies the energy balance correctly as a surplus (calories in > calories out). · Links the surplus to weight gain and explains the mechanism (stored energy). · Clarity and conciseness (2–4 sentences, on topic).

Lesson 2

What is a calorie?

Definition of a kilocalorie as a unit of heat energy. Clarifies that a dietary calorie is actually a kilocalorie (kcal) in scientific terms. Prevents the misconception that calories are substances or particles.

10 min4 assessments

You've heard "a calorie is a calorie." But what even is a calorie? It is not a substance, not a particle, not a thing you can see under a microscope. A calorie is a unit of energy — specifically, the amount of heat required to raise the temperature of one gram of water by one degree Celsius. That tiny unit is the small calorie (cal). When you read "200 calories" on a food label, you are actually reading 200 kilocalories (kcal) — the dietary Calorie with a capital C means 1 000 small calories. This distinction matters because a single mistake — treating a food label's number as small calories — would make you think an apple provides 0.2 kcal instead of ~100. The energy content of food is measured by burning it in a bomb calorimeter; the heat released warms surrounding water, and the temperature rise tells you the kilocalories. That is how we know carbohydrate and protein give about 4 kcal per gram, fat gives 9 kcal per gram, and alcohol gives 7 kcal per gram.

  • A calorie is a unit of heat energy, not a substance.
  • The dietary Calorie (capital C) equals one kilocalorie (1 000 small calories).
  • A bomb calorimeter measures the energy in food by burning it and measuring the temperature rise of water.
  • Carbohydrate and protein each provide 4 kcal per gram; fat provides 9 kcal per gram; alcohol provides 7 kcal per gram.
  • The common phrase "a calorie is a calorie" is physically true but ignores that different foods affect hunger and metabolism differently.
Practice
0/9 known
1 / 9
Reference

Energy density of macronutrients and alcohol

Carbohydrate

Energy (kcal per gram)
4
Notes
Includes sugars, starches, fibre (fibre gives ~2 kcal, but often counted as 4 in labels)

Protein

Energy (kcal per gram)
4
Notes
Amino acids; some energy loss in urea production, but labels use 4

Fat

Energy (kcal per gram)
9
Notes
Most energy-dense; includes saturated, unsaturated, trans

Alcohol

Energy (kcal per gram)
7
Notes
Ethanol; not a nutrient, but provides energy

These are averages from bomb calorimetry; actual available energy varies slightly by food matrix.

Go deeper

Read these when you want the full history and technical details of the calorie definition and the 'a calorie is a calorie' debate.

Check yourself

Check your understanding of what a calorie is and how it works.

1Multiple choiceChecked instantly

Which of the following statements about a dietary calorie (Calorie) is correct?

  • AIt is a type of fat stored in the body.
  • BIt is a unit of energy equal to one kilocalorie.
  • CIt is the energy required to raise 1000 grams of water by 1 degree Celsius.
  • DIt is a particle found in food that gives energy.
2Fill the blanksChecked instantly
3Select all that applyChecked instantly

Which of the following macronutrients provide 4 kcal per gram? (Select all that apply.)

  • ACarbohydrate
  • BProtein
  • CFat
  • DAlcohol
4Numeric answerChecked instantly

A food contains 10 grams of protein, 20 grams of carbohydrate, and 5 grams of fat. How many kilocalories does it provide?

Lesson 3

Basal metabolic rate

Energy the body burns at rest for vital functions. Factors affecting BMR: age, sex, lean mass, hormones. How to estimate BMR using simple formulas. Prevents the belief that BMR is the same for everyone.

12 min2 assessments

You already know that total daily energy expenditure splits into three parts: basal metabolic rate (BMR), the thermic effect of food, and physical activity. BMR is the largest piece—60 to 75 percent of the total. It's the energy your body needs while lying still, awake, after a 12-hour fast: heartbeating, lungs breathing, brain thinking, cells repairing.

You might think BMR is roughly the same for everyone your size, but it varies a lot. Factors that raise it: more lean mass, younger age, male sex (on average, because men tend to have more muscle), higher thyroid hormone levels, fever, pregnancy. Factors that lower it: aging (muscle loss), starvation or very low caloric diets (the body slows down), hypothyroidism.

Since BMR is individual, scientists created formulas to estimate it from simple measurements: weight, height, age, and sex. The most widely used today is the Mifflin-St Jeor equation. We'll use it next.

Estimate the BMR of Tom, a 40-year-old man who weighs 85 kg and is 175 cm tall. Use the Mifflin-St Jeor equation for males.

  1. 1

    BMR_male = 10 × weight(kg) + 6.25 × height(cm) − 5 × age(y) + 5

    This is the Mifflin-St Jeor equation for males. All units are metric.

1/3
Try it

Switch the gender slider between male and female while keeping weight, height and age the same. The difference is exactly 166 kcal (the constant shift). Now slowly increase age: you'll see BMR drop by roughly 5 kcal per year. Which input causes the biggest change? Move weight up and down—the coefficient 10 makes weight the most powerful factor. Notice the diminishing return: each added kilogram gives the same linear increase; there's no threshold where it changes.

30 years
70.0 kg
170 cm
0

Estimated BMR

—

This browser cannot run the calculation (Web Workers are unavailable).

Go deeper

For deeper reading on BMR measurement methods, factors, and the distinction between basal and resting metabolic rate.

  • BMR accounts for 60–75% of daily energy expenditure.
  • It is determined primarily by lean body mass, age, sex, and hormonal state.
  • The Mifflin-St Jeor equation estimates BMR: for men 10w + 6.25h − 5a + 5; for women 10w + 6.25h − 5a − 161 (w=kg, h=cm, a=years).
  • BMR declines with age as muscle mass decreases; strength training can mitigate the drop.
  • Very low calorie diets lower BMR below prediction, making weight loss harder over time.
Check yourself

Check your understanding of BMR estimation and factors.

1Numeric answerChecked instantly

Using the Mifflin-St Jeor equation, calculate the BMR of a 45-year-old woman who weighs 68 kg and is 168 cm tall. Round to the nearest whole number and give the answer in kcal/day.

2Short answerMarked by AI

Explain why a 50-year-old man who weighs the same as a 25-year-old man likely has a lower BMR. Name at least two factors that contribute to the difference.

Graded on Identifies age-related muscle loss and its direct effect on BMR · Names a second factor (hormonal change, reduced activity, or other) and explains how it lowers BMR

Lesson 4

Thermic effect of food

Energy cost of digesting, absorbing, and processing nutrients. Protein has the highest thermic effect (20-30%), followed by carbohydrate (5-10%) and fat (0-3%). Practical implications for diet.

10 min3 assessments

Not every calorie you eat is available to your body. Some of the energy in food is spent just to break it down, absorb it, and store it. This energy cost is called the thermic effect of food (TEF), sometimes referred to as dietary-induced thermogenesis. TEF accounts for roughly 10% of your total daily energy expenditure, but that average hides big differences between nutrients.

Protein demands the most work to process — 20 to 30% of the calories from protein are burned during digestion. That means if you eat 100 kcal of chicken breast, only 70–80 kcal actually enter your bloodstream as usable energy. Carbohydrates cost 5–10% of their energy, and fat costs next to nothing — 0 to 3%. So the composition of your meal directly changes how many net calories you end up with.

This is why a high-protein diet can feel thermogenically costly: your body literally heats up as it works through the protein. It also helps explain why you can eat the same number of calories from cookies vs. grilled chicken and get different body responses — the chicken's TEF leaves you with fewer usable calories.

  • The thermic effect of food (TEF) is the energy cost of digesting, absorbing, and metabolising nutrients.
  • TEF accounts for about 10% of total daily energy expenditure on a mixed diet.
  • Protein has the highest TEF: 20–30% of its calories are used in processing.
  • Carbohydrates have a moderate TEF: 5–10%.
  • Fat has the lowest TEF: 0–3% — almost all of its calories become available.
Reference

Thermic effect of macronutrients

Protein

Thermic effect (%)
20–30
Examples
Chicken, eggs, tofu, beans
Net calories per 100 kcal eaten
70–80 kcal

Carbohydrate

Thermic effect (%)
5–10
Examples
Rice, bread, fruit, pasta
Net calories per 100 kcal eaten
90–95 kcal

Fat

Thermic effect (%)
0–3
Examples
Butter, oil, cheese, nuts
Net calories per 100 kcal eaten
97–100 kcal

The net calorie value is approximate; exact TEF varies with meal composition, cooking method, and individual metabolism.

Practice
0/7 known
1 / 7
Check yourself

Test your understanding of the thermic effect of food.

1Multiple choiceChecked instantly

What is the approximate thermic effect of protein?

  • A0–3%
  • B5–10%
  • C20–30%
  • D50%
2Select all that applyChecked instantly

Which of the following statements about the thermic effect of food are true? Select two.

  • AThe thermic effect of food reduces the net calories available from a meal.
  • BProtein has a higher thermic effect than carbohydrate or fat.
  • CFat has the highest thermic effect of all macronutrients.
  • DThe thermic effect of food is the same for all nutrients.
3Fill the blanksChecked instantly

Lesson 5

Physical activity energy

Energy burned through movement. How to estimate energy expenditure for different activities using METs. Distinction between NEAT (non-exercise activity thermogenesis) and purposeful exercise.

15 min3 assessments

A 30‑minute run and a 30‑minute walk don't burn the same amount of energy — even if the clock says the same. The difference is captured by METs (Metabolic Equivalents), a standard measure of how many times your resting metabolic rate an activity requires.

– 1 MET = the energy you burn sitting quietly (~1 kcal per kg of body weight per hour). – A MET value of 5 means you burn five times your resting rate.

Energy burned (kcal) = MET value × body weight (kg) × time (hours)

Physical activity energy splits into two categories: – Purposeful exercise: planned, structured activity like running, cycling, or lifting weights. – NEAT (Non‑exercise Activity Thermogenesis): all the movement that isn't exercise — walking to the bus, fidgeting, gardening, doing dishes. NEAT can vary by 200–500 kcal per day between two people of the same weight, making it the most personal and adjustable part of the energy equation.

  • Physical activity energy (PA) is the most variable component of total daily energy expenditure.
  • MET (Metabolic Equivalent) is a unit that measures activity intensity relative to resting metabolism.
  • Energy expenditure from an activity (kcal) = MET × weight (kg) × hours.
  • NEAT includes all non‑exercise movement; it can differ by hundreds of calories per day between individuals.
  • Purposeful exercise produces a relatively predictable energy burn, while NEAT is harder to measure but equally important.

A 75 kg person goes hiking with a backpack (MET = 5.0) for 1 hour and 20 minutes. How many kilocalories do they burn?

  1. 1

    1 hour 20 min = 1 + (20/60) = 1.3333 hours

    Convert the time from hours and minutes to hours only. 20 minutes is 20/60 = 0.3333 hours.

1/3
Try it

Notice that doubling any one of the three inputs (weight, MET, or duration) doubles the result — the relationship is perfectly linear. Try to match the energy burned by a short intense activity (e.g., 15 min at MET 10) with a long light one (e.g., 60 min at MET 2.5). What combination gives the same 175 kcal?

70 kg
3.5 MET
30 min

Energy burned

—

This browser cannot run the calculation (Web Workers are unavailable).

Check yourself

Test your ability to calculate and think about physical activity energy.

1Numeric answerChecked instantly

A 68 kg person takes a 45‑minute brisk walk (MET = 4.0). How many kilocalories does she burn?

2Numeric answerChecked instantly

John weighs 80 kg and cycles at a moderate pace (MET = 8.0) for 20 minutes. How many kilocalories does he burn? (Answer to one decimal place.)

3Short answerMarked by AI

In your own words, explain the concept of NEAT and why it is considered the most variable component of total daily energy expenditure. Give one concrete example of a NEAT activity that could be increased to boost daily caloric burn.

Graded on Defines NEAT and relates it to total daily energy expenditure · Provides a concrete example of increasing NEAT · Explains why NEAT is the most variable component

Go deeper

For an extensive list of MET values for hundreds of activities, see the compendium of physical activities (linked from Wikipedia). Non‑exercise activity thermogenesis is well described in the NEAT article; it explains why this often overlooked component matters so much.

Lesson 6

Energy balance and weight change

How calorie surplus leads to weight gain and deficit leads to weight loss. The 3,500-kcal rule myth vs reality. Why energy balance is dynamic, not static. Prevents oversimplified thinking about weight change.

12 min3 assessments

You've learned that energy balance equals calories in minus calories out. But that equation is alive: as your weight changes, the 'calories out' side changes too.

When you eat more than you burn (a surplus), the excess is stored as fat and some lean tissue. Each pound of fat burns about 2–3 kcal per day just to exist; each pound of muscle burns 6–7 kcal. So gaining weight raises your total daily energy expenditure (TDEE). That rising expenditure shrinks the surplus — a negative feedback loop. Eventually, even if you keep eating the same surplus, you reach a new weight where your TDEE matches intake again.

Deficit works the same way in reverse. Lose weight and your BMR drops (less tissue, lower thermic effect, less NEAT). The same 500 kcal deficit you started with becomes a smaller effective deficit. Weight loss slows and eventually plateaus unless you adjust intake or activity.

The old '3,500-kcal rule' — that cutting 3,500 kcal equals one pound of loss — treats the body as a simple calorimeter. It came from a 1950s study of fasting men who lost about a pound per 3,500 kcal. But that ignores that in real people, losing weight lowers TDEE, so the same deficit produces less loss over time. The relationship is curvilinear, not linear.

This dynamic understanding explains why crash diets often fail, why the same deficit works differently for different people, and why sustainable change requires adjusting habits as your weight changes.

Energy balance feedback loop. Weight change alters metabolic rate, which changes expenditure and thus the balance, leading to a new equilibrium.

Analogy

Think of your energy balance like a bank account. Calories in are deposits; calories out are withdrawals. If you deposit more than you withdraw, your balance grows (weight gain). If you withdraw more, your balance shrinks (weight loss).

But here's the twist: the bank's interest rate changes depending on your balance. When your balance is high, the bank pays you a higher interest rate — your metabolism speeds up because you carry more tissue. That extra interest (increased TDEE) makes it harder to keep growing. When your balance is low, the bank cuts the interest rate — your metabolism slows down, making it harder to keep shrinking.

This "variable interest" analogy explains why a deficit that works initially becomes less effective over time: the bank (your body) alters the rate.

Where the analogy breaks down

In reality, the body's metabolic adaptation is not a fixed percentage like a bank interest rate; it is non-linear, varies widely between individuals, and includes hormonal changes the bank has no equivalent for. Also, you cannot bring your account to zero — your body defends a minimum essential fat mass.

Common misconception

“I can predict exactly how much weight I'll lose by calculating a daily deficit of 500 calories and expecting 1 pound per week consistently.”

The math is simple: 500 kcal × 7 days = 3,500 kcal, and textbooks and articles have repeated the "3,500-kcal rule" for decades. Initial weight loss often seems to match that estimate.

What is actually true

The body adapts: as you lose weight, your total daily energy expenditure decreases (less tissue, lower thermic effect, lower NEAT), so the same 500 kcal deficit becomes a smaller effective deficit. Weight loss follows a curvilinear curve, not a straight line. The 3,500-kcal number came from short-term fasting studies and does not account for individual body composition, hormones, or metabolic adaptation. It can serve as a rough starting point for the first few pounds only.

  • Energy balance is a dynamic system: changes in body weight alter total daily energy expenditure (TDEE).
  • Weight gain increases TDEE (via higher BMR, TEF, and NEAT), creating a negative feedback that dampens further gain.
  • Weight loss decreases TDEE, reducing the effective deficit and slowing further loss.
  • The 3,500-kcal rule is a historical simplification that ignores metabolic adaptation; actual weight change is curvilinear.
  • A new equilibrium is reached when intake and expenditure are balanced again at a different body weight.
  • Sustainable weight management requires adjusting intake or activity as weight changes, not assuming a fixed deficit.
Check yourself

Check your understanding of energy balance dynamics.

1Multiple choiceChecked instantly

Which of the following best describes the relationship between a calorie deficit and weight loss over a long period?

  • AEach 3,500 kcal deficit always leads to exactly one pound of weight loss.
  • BWeight loss remains linear indefinitely if you maintain the same daily deficit.
  • CAs weight decreases, metabolic rate drops, so the same deficit produces less weight loss over time.
  • DWeight loss stops once you hit a calorie limit; it does not change.
2Short answerMarked by AI

Maria starts a diet with a 500 kcal daily deficit. She loses 2 lb in the first two weeks, but only 1 lb in the next two weeks. Using the concept of energy balance dynamics, explain why her rate of weight loss slowed. (2–4 sentences)

Graded on Identifies metabolic adaptation as the cause of slowing · Explains connection between weight loss and expenditure change

3EssayMarked by AI

Compare the static energy balance model (where weight change is proportional to cumulative deficit) with the dynamic model (where expenditure adapts). In your analysis, describe one situation where the static model would mislead a person trying to lose weight, and explain what the dynamic model would predict instead. (200–400 words)

Graded on Accuracy of describing both models · Concrete example of static model misleading · Dynamic model prediction for same scenario

For you · never graded

Once you understand energy balance dynamics, how does it change your view of quick-fix diets or calorie-counting apps that promise linear results? Jot down your thoughts.

Lesson 7

The three macros: protein, fat and carbohydrate

You will be able to name the three macronutrients, state their energy density per gram, and describe their primary roles in the body. Covers the structural, hormonal and fuel functions of each. Prevents the mistake of treating one macronutrient as universally good or bad.

30 min4 assessments

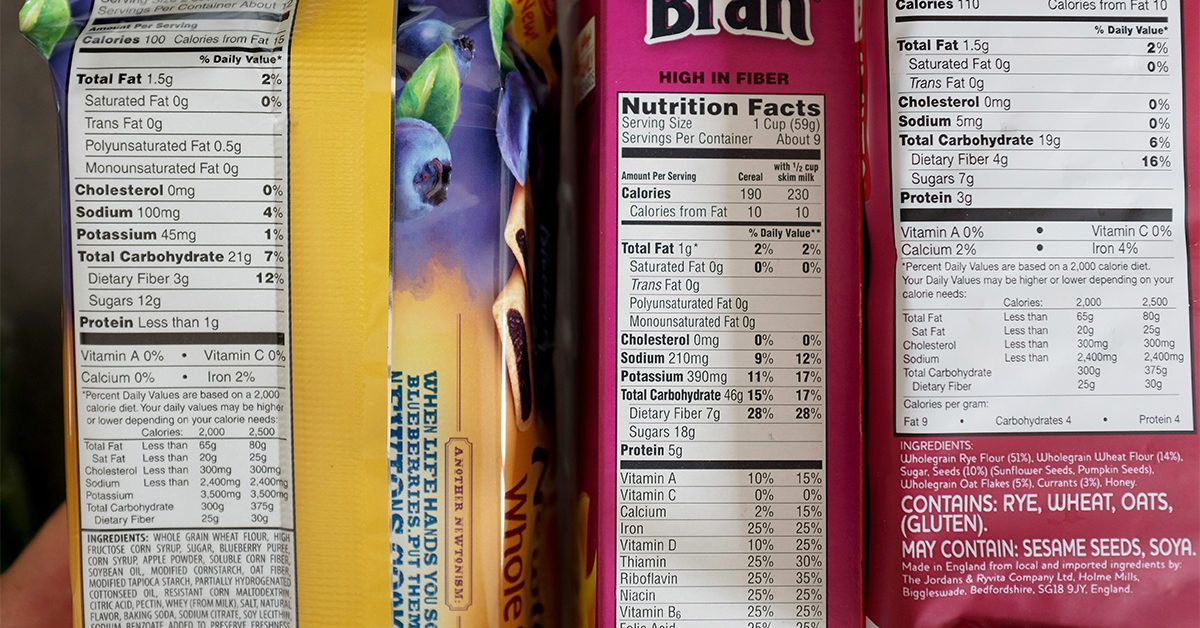
Read the nutrition panel on any packaged food and you will meet the same three names: protein, fat and carbohydrate. Those three — the macronutrients — are the only nutrients in food that supply energy, so every calorie in the previous step's energy equation arrived as one of them. The label lists grams, not calories, so turning the label into an actual number means multiplying grams by each macro's energy density: 4 kcal per gram for protein, 4 for carbohydrate, 9 for fat.

Those two numbers already tell you something practical. A gram of fat carries more than twice the energy of a gram of protein or carbohydrate, which is why two foods of equal weight can be wildly different in calories. But the macros are not interchangeable fuel tanks. Carbohydrate is the body's preferred immediate fuel — it powers the brain and working muscles, and what you do not burn gets stored as glycogen. Protein is mostly building material: muscle, skin, enzymes, and some hormones. It has no dedicated storage depot, so your intake needs to be reasonably steady. Fat is the long-term energy reserve, but it is also architecture — it forms cell membranes and is a precursor for some hormones.

The roles split along a clean line: carbohydrate for fast fuel, protein for structure, fat for both storage and signaling. No macro is good or bad on its own; the question is whether your intake matches what your body needs to do with each one.

Reference

The three macronutrients at a glance

Carbohydrate

Energy density
4 kcal/g
Primary roles
Immediate fuel for the brain and muscles; spares protein from being burned as fuel
Storage form
Glycogen in liver and muscle — limited supply

Protein

Energy density
4 kcal/g
Primary roles
Structural building blocks: muscle, skin, enzymes, some hormones
Storage form
None — the body draws down muscle when intake falls short

Fat

Energy density
9 kcal/g
Primary roles
Long-term energy reserve; cell membranes; precursor for some hormones
Storage form
Adipose tissue — nearly unlimited capacity

Alcohol supplies energy too, but it is not a macronutrient, so it does not appear in this table.

From grams on a label to calories in a bowl

A chicken rice bowl has three components. Multiply each gram by the right factor, then add:

ComponentProteinFatCarbohydrate
120 g chicken breast24 g2 g0 g
15 ml olive oil0 g14 g0 g
150 g cooked rice3 g0 g36 g

Work the arithmetic — 4 kcal/g for protein and carbohydrate, 9 kcal/g for fat:

  • Chicken protein: 24 × 4 = 96 kcal
  • Chicken fat: 2 × 9 = 18 kcal
  • Oil fat: 14 × 9 = 126 kcal
  • Rice carbohydrate: 36 × 4 = 144 kcal
  • Rice protein: 3 × 4 = 12 kcal

Total: 96 + 18 + 126 + 144 + 12 = 396 kcal

Now look at where the calories concentrate. The bowl contains 16 g of fat, and those 16 g contribute 144 kcal — 36% of the total energy. The 39 g of protein and carbohydrate together make up most of the bowl's food weight, yet deliver the other 64%. That single fact is why a drizzle of oil can turn a light meal into a heavy one without changing how full it makes you feel.

Practice
0/10 known
1 / 10
  • Protein, fat and carbohydrate are the only three nutrients in food that supply energy.
  • Protein and carbohydrate each supply 4 kcal per gram; fat supplies 9 kcal per gram.
  • Carbohydrate is the body's preferred immediate fuel; excess is stored as glycogen in the liver and muscles.
  • Protein is the body's building material — muscle, skin, enzymes and some hormones — and has no dedicated storage depot.
  • Fat serves as the long-term energy reserve and is also required for cell membranes and as a precursor for some hormones.
  • Energy density drives the calorie content of food: equal weights of two foods can differ by more than twofold in calories because of their fat content.
Check yourself

Four quick checks on the macro facts.

1Numeric answerChecked instantly

A snack contains 15 g of protein, 5 g of fat and 30 g of carbohydrate. Using the 4/4/9 values (protein 4 kcal/g, carbohydrate 4 kcal/g, fat 9 kcal/g), how many kilocalories does the snack supply in total? Give the number only.

2Multiple choiceChecked instantly

Which macronutrient supplies 9 kcal per gram — more than double the energy density of the other two?

  • ACarbohydrate
  • BFat
  • CProtein
  • DAlcohol
3Select all that applyChecked instantly

Which statements about the primary roles of the macronutrients in the body are correct? Select all that apply — more than one is correct.

  • ACarbohydrate is the body's preferred immediate fuel.
  • BProtein is the body's main long-term energy store.
  • CFat forms cell membranes and is a precursor for some hormones.
  • DProtein builds and repairs tissue and forms enzymes.
  • ECarbohydrate is stored in unlimited amounts as adipose tissue.
4Fill the blanksChecked instantly

Lesson 8

Protein: building and repairing

Primary roles: structural components, enzymes, some hormones. 4 kcal per gram. Essential amino acids. Sources: animal and plant.

12 min3 assessments

Your body is under constant construction. Every day, tissues are damaged, cells die, and enzymes wear out. Protein is the raw material for all of that repair. Unlike carbohydrate and fat, protein's primary job is not to provide energy—though it can, at 4 kcal per gram. Protein's real job is structural: muscles, skin, hair, nails, and the collagen that holds your joints together. It also makes enzymes and many hormones (insulin, for example, is a protein). Most importantly, the body cannot make all the amino acids it needs. Nine of the 20 amino acids are essential—they must come from food. Animal sources (meat, eggs, dairy) provide all nine, making them complete proteins. Most plant sources are incomplete, missing one or more essential amino acids. That does not make plant protein inferior, but it means you need variety—beans, grains, nuts, seeds—to cover all nine across the day.

The journey of dietary protein from food to body function.

Analogy

Think of protein as a construction crew. Each amino acid is a worker with a specific skill—some are welders, some electricians. The crew must have all the necessary skills to build a structure. The essential amino acids are the workers you cannot hire from within the company; you must recruit them from outside (your diet). The workers build and repair the body's structures (proteins). When the crew is oversized (excess protein), the extra workers are laid off and either used as fuel or sent to storage (fat). The crew also recycles materials after a demolition (amino acid recycling).

Where the analogy breaks down

A construction crew does not turn into fuel when the company runs out of energy; but the body can convert amino acids into glucose (gluconeogenesis) or ketones. Also, workers in a crew are not interchangeable; but some amino acids can be converted into others (non-essential) if needed.

  • Protein provides 4 kcal per gram.
  • 9 essential amino acids must come from the diet; the body can make the other 11.
  • Complete proteins (animal sources) contain all nine essential amino acids; most plant proteins are incomplete.
  • Primary roles of protein: structure (muscles, skin, hair), enzymes, hormones, immune function.
  • Excess protein is not stored as muscle; it is stored as fat or used for energy.
  • The RDA for protein is 0.8 g per kg of body weight per day.
Common misconception

“Eating more protein automatically builds more muscle.”

Muscle is made of protein, and bodybuilders eat high-protein diets to gain mass.

What is actually true

Muscle growth requires a combination of adequate protein, resistance exercise, and a caloric surplus. Extra protein without exercise is stored as fat or excreted. The body has a limit on how much protein it can use for synthesis per meal; excess nitrogen is removed and excreted as urea.

Check yourself

Check your understanding of protein's role in the body.

1Multiple choiceChecked instantly

A person requires 56 grams of protein per day. Which of the following meals provides the most protein? (Assume values are per serving as listed)

  • A200g chicken breast (31g protein per 100g)
  • B2 cups of cooked lentils (18g protein per cup)
  • C3 large eggs (6g protein per egg)
  • D150g tofu (8g protein per 100g)
2Short answerMarked by AI

Explain the process by which the body uses dietary protein to build new proteins. Include the steps of digestion, absorption, and synthesis. Also, describe what happens to excess amino acids.

Graded on Describes digestion and absorption of amino acids · Explains protein synthesis and role of essential amino acids · Describes fate of excess amino acids

3Short answerMarked by AI

Evaluate the claim: 'Plant proteins are inferior to animal proteins because they lack essential amino acids.' In your response, explain the concept of complementary proteins and why a varied plant-based diet can meet protein needs.

Graded on Correctly explains incomplete vs complete proteins · Describes complementary proteins and gives examples · Evaluates the claim with evidence

Lesson 9

Fat: energy and structure

Roles: energy storage, cell membranes, hormone precursors. 9 kcal per gram. Saturated, unsaturated, trans fats distinction.

12 min3 assessments

You already know that fat packs 9 kcal per gram — more than double the energy of protein or carbohydrate. That density evolved because fat is the body's long-term fuel depot. A gram of glycogen (stored carb) holds about 1 gram of water alongside it; a gram of fat sits nearly dry, so you can carry weeks of energy without lugging a water tank.

But fat isn't just a reserve tank. It's the foundation of every cell membrane (phospholipids are fat molecules), and it's the raw material for steroid hormones like testosterone and oestrogen. Without dietary fat, your body cannot absorb fat-soluble vitamins A, D, E and K.

The critical distinction is which fat you eat. Saturated fats — solid at room temperature, found in butter, coconut oil, animal fat — are stable and used for structure. Unsaturated fats — liquid oils from plants and fish — contain double bonds that make them fluid, which is essential for flexible cell membranes. Trans fats are unsaturated fats that have been chemically hydrogenated to make them solid; they pack tightly into membranes and disrupt signalling. Natural trans fats exist in tiny amounts in dairy; industrial trans fats (partially hydrogenated oils) are the harmful ones, linked to inflammation and heart disease.

Your goal is not to avoid fat — your body needs roughly 20–35% of daily calories from it, mostly unsaturated.

Classification of dietary fats by chemical structure and physical properties.

Analogy

Think of your body as a house with a pantry and a construction drawer. Carbohydrates are the snacks you eat today: quick energy, runs out fast. Fat is the non-perishable food in the pantry — canned goods that last for weeks and can feed you when the kitchen is closed. But the pantry analogy misses something: fat isn't just stored cans; it's also the nails and boards of the house itself. Your cell walls are built from fat molecules. The pantry only stores; fat also builds.

Where the analogy breaks down

The analogy breaks down because fat is not inert storage — it actively participates in signalling (hormones), membrane fluidity and vitamin transport. A pantry cannot rebuild walls or send messages; fat does all three.

Common misconception

“"Eating fat makes you fat, so I should eat as little fat as possible."”

Fat has 9 kcal per gram, the highest energy density of any nutrient. A cookie with 20 g of fat packs 180 kcal from fat alone — easy to overeat without noticing.

What is actually true

Weight gain is driven by total calorie surplus, not by fat specifically. In fact, a diet too low in fat leads to hormone disruption, dry skin and inability to absorb vitamins A, D, E, K. The type of fat matters more than the amount: swap saturated for unsaturated, avoid industrial trans fats, and keep total calories in check.

Calculating the fat contribution of a grilled chicken salad

Your lunch: 25 g protein, 12 g fat, 8 g carbohydrate. Use the energy values:

  • Fat: 12 g × 9 kcal/g = 108 kcal
  • Protein: 25 g × 4 = 100 kcal
  • Carbs: 8 g × 4 = 32 kcal
  • Total = 108 + 100 + 32 = 240 kcal
  • Fat percentage = 108 ÷ 240 × 100 = 45%

That's above the recommended 20–35% range, but the fat here likely comes from olive oil (unsaturated) — acceptable. If the 12 g were from fried chicken (saturated or trans), you'd reconsider.

Check yourself

Check your understanding of fat's roles and types.

1Multiple choiceChecked instantly

Which of the following is a primary role of dietary fat in the human body?

  • ADirect source of glucose for the brain
  • BComponent of cell membranes and precursor for hormones
  • CPrimary source of fiber for digestion
  • DOnly used for insulation under the skin
2Short answerMarked by AI

Read this nutrition label: Total Fat 15g (Saturated 9g, Trans 0.5g, Unsaturated 5.5g). Explain why the trans fat value of 0.5g may be more concerning than the saturated fat, even though saturated fat is higher. (2–4 sentences)

Graded on Identifies trans fat as industrially hydrogenated and harmful · Compares risk relative to saturated fat · Addresses the quantity relevance

3EssayMarked by AI

Your friend says: "I'm going on a zero-fat diet to lose weight fast. Butter and oil are just empty calories." Write a short response (200–400 words) that explains why this approach is flawed. Reference at least two essential functions of fat in the body and distinguish between harmful and beneficial fat sources.

Graded on Identifies essential functions of fat beyond energy · Distinguishes between harmful and beneficial fat sources · Addresses weight loss mechanism correctly

Lesson 10

Carbohydrate: primary fuel

Roles: immediate energy, glycogen storage, sparing protein. 4 kcal per gram. Simple vs complex carbs. Fiber's role.

12 min3 assessments

Your body runs on glucose. When you eat carbohydrates, digestion breaks them down into sugars — mostly glucose — that enter your bloodstream. Glucose is the preferred fuel for your brain, muscles, and every cell.

But not all carbohydrates are the same. Simple carbohydrates (like table sugar, fruit juice, honey) are made of one or two sugar molecules. They are absorbed quickly, giving a rapid rise in blood glucose. Complex carbohydrates (like whole grains, legumes, vegetables) are chains of many sugar molecules. They take longer to digest, providing a slower, steadier release of energy.

What happens to the glucose you don't use immediately? Your liver and muscles store it as glycogen — a compact, branched molecule that can be rapidly mobilised when you need energy between meals or during exercise. Your body can store about 300–500 grams of glycogen, enough for roughly 12–24 hours of moderate activity.

If glycogen stores are full and you still have excess glucose, the liver converts it into fat for long-term storage. This is why a chronic surplus of carbohydrates (or any calories) can lead to weight gain.

Carbohydrates also spare protein. When you eat enough carbs, your body uses glucose for energy rather than breaking down muscle protein. That's why athletes carb-load before endurance events: to preserve muscle.

Finally, there's dietary fibre — a carbohydrate that your body cannot digest. Fibre passes through the small intestine intact, slows the absorption of sugars, helps you feel full, and feeds your gut bacteria. It doesn't provide energy (0 kcal/g), but it's essential for health.

In short, carbohydrates are the body's primary fuel source, providing 4 kcal per gram, and are stored as glycogen for short-term energy needs. The type and timing of carbohydrates matter for how your body uses them.

How carbohydrates are processed from ingestion to use and storage.

Analogy

Think of carbohydrates as the gasoline in your car. Just as gasoline provides immediate energy for the engine, glucose provides quick energy for your cells. The glycogen stored in your liver and muscles is like a reserve fuel tank — when you run low, the body taps into it. And fibre is like the oil filter: it doesn't power the engine but keeps the system running smoothly by cleaning out waste.

Where the analogy breaks down

Unlike a car that can only run on gasoline, your body can also burn fat and protein for fuel. Also, a car's fuel tank has a fixed capacity; your body can store excess glucose as fat with no theoretical limit, which can lead to weight gain. The analogy also suggests that fibre is optional, whereas it is essential for health.

Common misconception

“All carbohydrates are bad because they make you gain weight.”

Eating too many carbs, especially simple sugars, can lead to fat storage when glycogen stores are full. Many popular diets (like keto) demonise carbs, and people often lose weight when cutting carbs, which reinforces the belief.

What is actually true

Carbohydrates are the body's primary fuel source. Weight gain occurs from a calorie surplus, regardless of whether the extra calories come from carbs, fat, or protein. Complex carbohydrates and fibre are essential for health and sustained energy. The type and quantity of carbs matter more than carbs themselves.

  • Carbohydrates provide 4 kcal per gram of energy.
  • Glucose is the primary fuel for the brain and muscles.
  • Excess glucose is stored as glycogen in the liver and muscles, with a capacity of about 300–500 grams.
  • When glycogen stores are full, excess glucose is converted to fat for long-term storage.
  • Dietary fibre, though indigestible, slows glucose absorption, promotes satiety, and supports gut health.
  • Carbohydrates spare protein by providing energy, preventing muscle breakdown for fuel.
  • Simple carbohydrates are digested quickly; complex carbohydrates provide sustained energy.
Check yourself

Check your understanding of carbohydrate metabolism.

1Multiple choiceChecked instantly

Why is dietary fibre considered a carbohydrate if it does not provide energy?

  • ABecause it is made of sugar molecules that the body can digest.
  • BBecause it is a polysaccharide that the body cannot digest, but it is still classified as a carbohydrate.
  • CBecause it provides 4 kcal per gram like other carbohydrates.
  • DBecause it is stored as glycogen in the liver.
2Short answerMarked by AI

A slice of whole-wheat bread contains 15 grams of carbohydrates. Calculate how many calories come from carbohydrates. Then explain what happens to those carbohydrates after you eat them, assuming you are not in a calorie surplus and your glycogen stores are not full.

Graded on Calorie calculation · Explanation of carbohydrate fate · Clarity and completeness

3EssayMarked by AI

Compare and contrast how a marathon runner and an office worker should approach carbohydrate intake. Consider the roles of glycogen storage, immediate energy, and fibre. Which type of carbohydrate (simple vs complex) is more appropriate for each, and why? Aim for 200–300 words.

Graded on Comparison of energy needs · Carbohydrate type recommendation · Role of fibre · Organization and clarity

Lesson 11

Energy density per gram

Fat 9 kcal/g, alcohol 7 kcal/g, protein and carbohydrate 4 kcal/g. Why this matters for portion sizes and diet composition.

8 min3 assessments

You already know the three macronutrients. Now you learn exactly how many calories each one packs per gram — and why that number changes everything about portion sizes and diet composition.

Energy density is the number of calories in one gram of a food or nutrient. It is why a tablespoon of oil (120 kcal) and a whole bowl of broccoli (also ~120 kcal) feel so different in your stomach.

NutrientEnergy density (kcal/g)
Fat9
Alcohol7
Protein4
Carbohydrate4

Fat is the most energy-dense. Alcohol comes second but provides no other nutrients — it is "empty calories." Protein and carbohydrate tie at 4 kcal/g. Fiber is a carbohydrate that your body cannot fully digest, so it contributes fewer calories (about 2 kcal/g) and is often subtracted on labels.

Why this matters for your plate:

  • A handful of nuts (high fat) can contain as many calories as a full meal of vegetables.
  • If you are trying to lose weight, choosing foods with lower energy density lets you eat a larger volume for the same calories — this is called the "volumetrics" approach.
  • When reading a label, the grams of fat, carbs and protein tell you exactly how many calories are inside: (9 × fat g) + (4 × protein g) + (4 × carb g) + (7 × alcohol g).
Reference

Energy density of common nutrients

Fat

Energy density (kcal/g)
9
Example foods
Butter, oil, nuts, fatty meat

Alcohol

Energy density (kcal/g)
7
Example foods
Beer, wine, spirits

Protein

Energy density (kcal/g)
4
Example foods
Chicken breast, tofu, eggs

Carbohydrate

Energy density (kcal/g)
4
Example foods
Rice, bread, pasta, sugar

Dietary fiber

Energy density (kcal/g)
~2
Example foods
Vegetables, whole grains, legumes

Fiber is a carbohydrate but is only partially digested; its energy contribution is roughly 2 kcal/g and is often excluded from calorie counts on labels.

Practice
0/8 known
1 / 8
  • Fat provides 9 kcal per gram — more than double the energy of protein or carbohydrate.
  • Alcohol provides 7 kcal per gram but has no nutritional value.
  • Protein and carbohydrate both provide 4 kcal per gram.
  • Dietary fiber contributes about 2 kcal per gram because it is only partially digested.
  • Energy density determines how many calories you get per bite: high-density foods (oil, cheese) deliver many calories in a small volume.
  • Choosing low-energy-density foods (vegetables, fruits, broth-based soups) allows larger portions for the same calorie budget.
Check yourself

Check your understanding of energy density per gram.

1Fill the blanksChecked instantly
2Multiple choiceChecked instantly

Which of the following has the highest energy density per gram?

  • AProtein (4 kcal/g)
  • BCarbohydrate (4 kcal/g)
  • CFat (9 kcal/g)
  • DAlcohol (7 kcal/g)
3Select all that applyChecked instantly

Select all statements that are true about energy density.

  • AA food with higher energy density provides more calories for the same weight.
  • BProtein and carbohydrate have the same energy density.
  • CAlcohol has a higher energy density than fat.
  • DFiber contributes exactly 4 kcal/g.
  • EEnergy density affects how full you feel relative to calories.
  • FAll carbohydrates are digested completely and provide 4 kcal/g.

Lesson 12

How food becomes fuel: digestion and absorption

You will be able to trace a meal from mouth to bloodstream, naming the organs and enzymes responsible for breaking down each macronutrient. Covers mechanical and chemical digestion, the role of the small intestine, and the hepatic portal vein. Prevents the misconception that food enters the blood as whole food.

35 min4 assessments

You know the three macros — protein, fat, carbohydrate — and you know they carry energy. But if you swallow a piece of bread, the bread does not crawl into your bloodstream as bread. Something has to take it apart.

That something is your digestive tract — a tube about nine metres long that starts at your mouth and ends at your anus. Everything that happens inside that tube is either mechanical (chewing, churning, mashing) or chemical (enzymes that break bonds). The goal is the same for every macronutrient: get it small enough to cross the wall of the small intestine and enter the blood.

Carbohydrates start first. Saliva contains amylase, which snips starch into shorter sugar chains. Protein waits until the stomach, where pepsin and hydrochloric acid begin uncoiling and cutting protein strands. Fat does almost nothing until the small intestine — it is water-repellent, so enzymes cannot reach it until bile (made by the liver, stored in the gallbladder) emulsifies it into droplets.

Once in the small intestine, pancreatic enzymes finish the job. Pancreatic amylase finishes starch breakdown. Trypsin and chymotrypsin cut proteins into peptides and then amino acids. Pancreatic lipase breaks fat droplets into fatty acids and monoglycerides. The inner surface of the small intestine is lined with villi — finger-like projections — and each villus is covered in microvilli. That folds the surface area to about the size of a tennis court, packed into a tube you could hold in your hand.

Absorbed nutrients do not go straight to your heart. They travel through the hepatic portal vein to the liver first. The liver decides what to store, what to release, and what to convert. That is why your blood sugar does not spike to dangerous levels after a meal — the liver buffers it.

The path of a meal from mouth to bloodstream, showing where each digestive action occurs.

Diagram of the small intestine wall showing villi, microvilli, and the brush border with enzymes that complete digestion of carbohydrates.
CC BY-SA 4.0· Sander kersten source
  • Digestion is both mechanical (chewing, churning) and chemical (enzymes cutting bonds).
  • Carbohydrate digestion begins in the mouth with salivary amylase; protein digestion begins in the stomach with pepsin; fat digestion begins in the small intestine with bile emulsification.
  • The small intestine's villi and microvilli increase surface area to about the size of a tennis court, enabling efficient absorption.
  • Absorbed monosaccharides and amino acids enter capillaries in the villi and travel via the hepatic portal vein to the liver.
  • Long-chain fatty acids and monoglycerides are repackaged into chylomicrons and enter lacteals (lymphatic vessels), bypassing the liver initially.
  • The liver processes absorbed nutrients before they reach general circulation, buffering blood sugar and storing or converting nutrients.
Common misconception

“Food is absorbed into the blood as whole food — the bread I eat becomes bread in my blood.”

We say 'I ate bread' and later 'my blood sugar went up', so it feels like the bread itself entered the bloodstream. The digestive tract is just a pipe, and things that go in one end come out the other.

What is actually true

No whole food molecule larger than a monosaccharide, amino acid, or short fatty chain can cross the intestinal wall. Every starch, protein, and fat must be broken down into its smallest building blocks — glucose, amino acids, fatty acids — before absorption. The bread never enters your blood; the glucose that was once part of the bread does.

Check yourself

Check your understanding of the digestive journey.

1Multiple choiceChecked instantly

Where does chemical digestion of protein begin?

  • AMouth, with salivary amylase
  • BStomach, with pepsin and hydrochloric acid
  • CSmall intestine, with pancreatic trypsin
  • DLarge intestine, with bacterial enzymes
2Short answerMarked by AI

Why does fat digestion require bile, while carbohydrate digestion does not?

3Fill the blanksChecked instantly
4Short answerMarked by AI

Explain why the small intestine has villi and microvilli, and describe what would happen to nutrient absorption if they were absent.

Graded on Identifies the purpose of villi/microvilli · Describes the consequence of their absence · Uses correct anatomical terms

Lesson 13

Mechanical vs chemical digestion

Difference between physical breakdown (chewing, churning) and enzymatic breakdown (salivary amylase, gastric enzymes). Where each occurs.

10 min3 assessments

Digestion breaks food into pieces your body can absorb. But 'breaking down' happens two completely different ways.

Mechanical digestion is physical crushing. Your teeth tear and grind food into smaller chunks. Your stomach churns and squeezes that mush into a soupy paste. No chemical bonds are broken — you're just making the pieces smaller so more surface area is exposed. More surface area means enzymes can reach more food molecules at once.

Chemical digestion is molecular demolition. Enzymes — specialised protein machines — snip specific chemical bonds. Salivary amylase in your mouth starts breaking starch into sugars. In your stomach, pepsin (activated by acid) cuts proteins into fragments. In your small intestine, pancreatic enzymes finish the job on every macronutrient. Bile from the liver isn't an enzyme; it physically emulsifies fats so lipase can reach them, which is a chemical step because it rearranges fat droplets at the molecular level.

Both types happen at the same time in some organs. Your mouth chews (mechanical) while amylase works (chemical). Your stomach churns (mechanical) while pepsin cuts (chemical). Neither works well alone — mechanical digestion without enzymes gives you a ball of undigested food, and enzymes without mechanical breakdown can't reach enough surface to act fast enough.

Mechanical and chemical digestion pathways from mouth to small intestine.

Analogy

Imagine a Lego castle that needs to be broken down into individual bricks so the bricks can be reused.

Mechanical digestion is like smashing the castle with a hammer into smaller clumps. The bricks are still stuck together, but the clumps are smaller.

Chemical digestion is like dipping those clumps into a solvent that dissolves the glue holding the bricks together, freeing each brick.

You need both: hammering alone leaves glued clumps; solvent alone can't reach the glue inside a big castle fast enough.

Where the analogy breaks down

In the analogy, the solvent dissolves glue indiscriminately. Real enzymes are specific — amylase only attacks starch, pepsin only proteins. Also, the 'bricks' (absorbed nutrients) are chemically changed, not reused as the same Lego pieces.

Common misconception

“Stomach acid digests food — that's why it's so strong.”

Acid can dissolve many things, and stomach acid (HCl) is indeed powerful enough to kill bacteria and denature proteins. It feels logical that it would also break down food.

What is actually true

Stomach acid does not break covalent bonds in food. Its main digestive role is to activate the enzyme pepsin (by converting pepsinogen to pepsin) and to unfold proteins so pepsin can reach their bonds. The actual chemical digestion of proteins is done by pepsin, not the acid. Acid alone would leave food largely intact.

Check yourself

Check your understanding of mechanical vs chemical digestion.

1Multiple choiceChecked instantly

Which of the following is an example of chemical digestion?

  • ATeeth grinding food into smaller pieces
  • BThe stomach churning food into chyme
  • CSalivary amylase breaking starch into maltose
  • DPeristalsis moving food down the esophagus
2Short answerMarked by AI

Explain why mechanical digestion is necessary for chemical digestion to work efficiently. Give a specific example.

Graded on States that mechanical digestion increases surface area · Provides a specific example linking mechanical to chemical · Explains why efficiency improves

3Short answerMarked by AI

A patient has a condition where their stomach produces very little acid. How would this specifically affect chemical digestion in the stomach? (Assume mechanical digestion is normal.)

Graded on Identifies that pepsin activation requires acid · Discusses protein denaturation · Considers downstream effects

Lesson 14

The small intestine's role

Duodenum, jejunum, ileum. Brush border enzymes. Pancreatic enzymes (amylase, lipase, proteases). Bile from liver for fat digestion. Absorption through villi and microvilli.

15 min3 assessments

You already know that stomach acid and pepsin turn your meal into chyme. But that chyme is still mostly large molecules — starch, proteins and fat droplets — and it's acidic. The small intestine's three-part sequence finishes the breakdown and pours the result into your blood.

The secret is section-by-section handoff. The duodenum receives chyme, adds pancreatic enzymes and bile, and neutralises the acid. The jejunum's brush border strips the last chemical bonds off carbs and proteins. The ileum picks up what the jejunum missed — especially vitamin B₁₂ and recycled bile salts. Each section builds on the work of the one before, and doing them out of order blocks the entire operation.

The three sections of the small intestine work sequentially: each stage depends on the one before.

Steps
0/7

Follow a mouthful of food as it crosses the pyloric sphincter and moves through the small intestine. At each step, one specific thing must happen — or digestion stalls.

  1. Chyme enters the duodenum

    The pyloric sphincter opens to release a small amount of acidic chyme into the duodenum, the first 25 cm of the small intestine. The duodenum's walls stretch to receive it and begin releasing its own hormones (secretin and CCK) to control what comes next.

    If the sphincter opens too wide, a flood of acid overwhelms the duodenal lining and can damage it.

    The duodenum is slightly distended; pH of the content remains ~2 until bicarbonate arrives.

  2. Pancreatic enzymes and bicarbonate are added

    The pancreas secretes amylase (starch → sugars), lipase (fats → fatty acids + monoglycerides), proteases (proteins → peptides) and bicarbonate directly into the duodenal lumen through the pancreatic duct. Bicarbonate neutralises the stomach acid, raising the pH to about 6–7.

    Without bicarbonate, the acidic environment denatures the pancreatic enzymes and they stop working.

    The pH of the chyme rises to 6.0–7.0; you can see the bubbly mix of enzymes.

  3. Bile emulsifies fats

    The gallbladder releases bile through the common bile duct. Bile salts act like detergent: they break large fat globules into microscopic droplets — a process called emulsification — which gives lipase a huge surface area to attack.

    If the gallbladder has been removed, bile drips continuously at a low rate, so fatty meals are poorly emulsified and can cause steatorrhea (fatty stool).

    Fat droplets are now ≤1 μm in diameter, creating a milky suspension instead of visible oil slicks.

  4. Brush border enzymes finish digestion

    The enterocytes (lining cells) of the duodenum and jejunum have a brush border — microvilli studded with digestive enzymes. Lactase, sucrase, maltase and peptidases cleave the last bonds: disaccharides → monosaccharides, oligopeptides → amino acids and dipeptides.

    A deficiency of any brush border enzyme (e.g., lactase deficiency) leaves the disaccharide undigested; it ferments in the colon, causing gas and diarrhea.

    The chyme now contains monomers (simple sugars, amino acids, free fatty acids) ready for transport.

  5. Villi and microvilli absorb nutrients

    The inner wall of the jejunum is covered with villi (finger-like projections), each coated in microvilli. The enormous surface area allows monosaccharides and amino acids to diffuse into capillaries that carry them to the liver. Fatty acids and monoglycerides reform into triglycerides, are wrapped into chylomicrons, and enter lacteals (lymph vessels).

    Damage to villi (e.g., in celiac disease) shrinks the absorptive surface, causing malnutrition even if digestion is normal.

    Blood glucose rises about 20–30 minutes after a meal; visible fat turns the lymph milky.

  6. Jejunum absorbs water and vitamins

    The jejunum (the middle 2.5 m) absorbs most of the remaining water, plus water-soluble vitamins (B vitamins and vitamin C), calcium, iron and magnesium.

    If chyme moves through too fast (e.g., in dumping syndrome), water and vitamins are not absorbed, leading to dehydration and deficiencies.

    The contents become progressively thicker and less liquid as water is extracted.

  7. Ileum salvages bile salts and B₁₂

    The ileum (final 3.5 m) reabsorbs the bile salts (so the liver can reuse them) and absorbs vitamin B₁₂ bound to intrinsic factor (secreted by the stomach). The residue — mostly fibre, dead cells, and water — passes into the large intestine.

    Surgical removal or disease of the ileum leads to B₁₂ deficiency (pernicious anaemia) and loss of bile salts, which worsens fat malabsorption.

    Bile salt concentration in portal blood rises; B₁₂ is stored in the liver.

Checklist
0/6

Verification checklist: Small-intestine processing

Tick each item after you can explain it to yourself in one sentence. If you hesitate, review the walkthrough step.

Check yourself

Check that you can apply the sequential logic of small-intestine digestion.

1Put in orderChecked instantly

A meal's journey through the small intestine depends on a precise sequence. Place these events in the order they actually occur, from first to last.

  • ABile emulsifies fat droplets
  • BPancreatic enzymes and bicarbonate enter the duodenum
  • CBrush border enzymes split disaccharides into monosaccharides
  • DChyle enters the duodenum through the pyloric sphincter
  • EVilli absorb monomers into blood and lymph
  • FIleum reabsorbs bile salts and absorbs vitamin B₁₂
2Short answerMarked by AI

A 45-year-old woman had her gallbladder removed last year. She now experiences loose, foul‑smelling, greasy stools whenever she eats a meal high in fat. Using what you know about the sequential processing in the small intestine, explain why this happens. What specific step is disrupted, and how would you expect her jejunum and ileum to compensate – or fail to – over the long term? (2–4 sentences)

Graded on Identifies the disrupted step (bile emulsification in the duodenum) and links it to lipase action · Describes the long‑term consequences for the jejunum and ileum

3Multiple choiceChecked instantly

In which section of the small intestine does the brush border complete the digestion of carbohydrates and proteins?

  • ADuodenum only
  • BJejunum (and to a lesser extent the duodenum)
  • CIleum only
  • DAll three sections equally
Go deeper

Read the Wikipedia article on the small intestine for additional detail on histology and regional variation in absorption.

Lesson 15

The hepatic portal vein

Pathway of absorbed nutrients from small intestine to liver. Liver's role in processing, storing, and regulating blood nutrients before they reach general circulation.

10 min3 assessments

You've learned how food is broken down and absorbed in the small intestine. But where do those freshly absorbed nutrients go next? Not straight to the heart. They first travel through a special blood vessel called the hepatic portal vein to the liver.

This vein collects blood rich in glucose, amino acids, vitamins, and other digestion products from the stomach, intestines, spleen, and pancreas. It delivers them to the liver, which acts as the body's chemical processing plant. The liver can:

  • Convert glucose to glycogen for storage
  • Remove toxins like alcohol
  • Store iron and certain vitamins
  • Regulate blood sugar levels before the blood reaches the rest of your body

This arrangement is called a portal system – a vein that connects two capillary beds (one in the digestive organs, one in the liver) without passing through the heart. It ensures the liver gets first pick of everything you absorb.

  • The hepatic portal vein carries nutrient-rich blood from the digestive tract to the liver.
  • It is formed by the union of the superior mesenteric vein and the splenic vein.
  • The liver processes, stores, and regulates nutrients before they enter systemic circulation.
  • The liver converts excess glucose to glycogen and stores it.
  • The liver detoxifies harmful substances such as alcohol and drugs.
  • The hepatic portal system is a portal system: a vein between two capillary beds.
Practice
0/8 known
1 / 8
Reference

Key vessels in the hepatic portal system

Hepatic portal vein

Origin
Union of superior mesenteric and splenic veins
Destination
Liver
Function
Carries nutrient-rich blood to the liver

Superior mesenteric vein

Origin
Small intestine, colon
Destination
Hepatic portal vein
Function
Drains blood from most of the digestive tract

Splenic vein

Origin
Spleen, stomach, pancreas
Destination
Hepatic portal vein
Function
Drains blood from spleen and associated organs

Hepatic artery

Origin
Aorta
Destination
Liver
Function
Supplies oxygenated blood to the liver

Hepatic veins

Origin
Liver
Destination
Inferior vena cava
Function
Carry processed blood away from the liver to the heart

The hepatic portal vein is the main route for absorbed nutrients to reach the liver.

Go deeper

For more detail on the anatomy and clinical significance of the hepatic portal system.

Check yourself

Check your understanding of the hepatic portal vein.

1Multiple choiceChecked instantly

After a meal, glucose absorbed from the small intestine travels first to which organ before reaching the rest of the body?

  • AHeart
  • BLiver
  • CKidneys
  • DLungs
2Select all that applyChecked instantly

Which of the following are functions of the liver in processing absorbed nutrients? (Select all that apply)

  • AConverting glucose to glycogen
  • BProducing digestive enzymes
  • CStoring vitamins
  • DDetoxifying alcohol
  • EAbsorbing fatty acids
3Fill the blanksChecked instantly

Lesson 16

Macronutrient digestion differences

How carbohydrate, protein, and fat are digested and absorbed differently. Carbohydrates start in mouth, protein in stomach, fat primarily in small intestine with bile.

15 min3 assessments

Eat a meal and three different digestive systems switch on. The rice in a burrito begins breaking down while you chew. The egg waits for acid in your stomach. The butter holds out until it reaches bile in your small intestine. Same gut, three different starting lines.

That matters beyond trivia. It decides which food raises your blood glucose fast, which one helps rebuild muscle after a workout, and which one keeps you full for hours. You can already trace a meal through the organs from How food becomes fuel: digestion and absorption. The next step is knowing which macronutrient takes which path, so you can predict what a meal will do before you eat it.

The table below is the reference you will return to; the example after it shows all three paths running at once in one breakfast.

Three macronutrients, three paths. These are the axes that decide what actually happens after you swallow, plus the situation where each path wins.

Carbohydrate

Digestion starts
Mouth: salivary amylase
Main workers
Salivary amylase → pancreatic amylase → brush-border enzymes
Absorbable units
Monosaccharides: glucose, fructose, galactose
Route into the body
Portal vein → liver
Pace
Fast: glucose can reach blood within about an hour

Best for Pre-exercise snacks or low-blood-sugar moments, when you want glucose in the bloodstream within the hour.

Protein

Digestion starts
Stomach: pepsin in acid
Main workers
Pepsin → trypsin and chymotrypsin → brush-border peptidases
Absorbable units
Amino acids, dipeptides, tripeptides
Route into the body
Portal vein → liver
Pace
Medium: absorption continues over several hours

Best for Recovery after resistance training, when muscles need amino acids delivered steadily over the next few hours.

Fat

Digestion starts
Small intestine: only after bile emulsifies it
Main workers
Bile (emulsifier) + pancreatic lipase
Absorbable units
Monoglycerides, free fatty acids, glycerol
Route into the body
Lymphatic lacteals → thoracic duct → blood
Pace
Slowest: leaves the stomach slowly and is absorbed over hours

Best for Long, steady situations — a hike or a busy day with no chance to snack — when you want a meal to release energy slowly and keep you full.

One breakfast, three timetables

Breakfast on the table: one flour tortilla (about 25 g carbohydrate), two scrambled eggs (about 12 g protein, 10 g fat), and a pat of butter (4 g fat) on the tortilla.

0 minutes — mouth. Chewing grinds the tortilla, and salivary amylase starts snipping starch into shorter chains. The eggs and butter are only mixed and swallowed; protein and fat have no significant digestion here.

20–60 minutes — the tortilla arrives first. The partly broken-down starch meets pancreatic amylase in the duodenum, then brush-border enzymes turn the fragments into glucose. Glucose crosses the gut wall into the portal vein and reaches the liver. This is the first macronutrient to arrive.

1–3 hours — the eggs arrive next. Stomach acid denatures the egg proteins, and pepsin cuts them into peptides. In the small intestine, trypsin and chymotrypsin continue, and brush-border peptidases finish the job. Amino acids and small peptides enter the portal vein — same road as glucose, but later.

2–6 hours — the butter arrives last. The butter's triglycerides are still mostly intact. Bile from the gallbladder emulsifies them into droplets, and pancreatic lipase splits them into monoglycerides and free fatty acids. These are bundled into chylomicrons, enter the lymph through lacteals, and reach the blood through the thoracic duct. Meanwhile, the fat in the duodenum has been slowing stomach emptying, which is why this breakfast keeps you full past lunch.

Result: carb glucose first, protein amino acids next, fat last — and only fat detours through the lymph instead of the portal vein.

Common misconception

“Fat is digested in the stomach — that's why a fatty meal sits heavy.”

Fatty meals genuinely make you feel full, and the stomach is where food churns and slowly empties, so the heavy feeling feels like digestion happening there.

What is actually true

A little lipase from the mouth and stomach touches the fat, but it is minor. True fat digestion starts in the small intestine, where bile emulsifies large fat droplets and pancreatic lipase breaks them down. The fullness comes from fat slowing stomach emptying, not from the stomach digesting fat. That is why a high-fat meal will not raise blood glucose quickly, but it will keep you satisfied longer.

  • If you need blood glucose up within the hour, choose a carbohydrate food: its digestion starts in the mouth and its glucose enters the portal vein quickly.
  • If you are recovering from resistance training, protein fits better: its amino acids arrive steadily over several hours rather than as a spike.
  • Fat is the only macronutrient whose absorbed products enter the lymph first, so they bypass the liver on the way to the blood.
  • A fatty meal feels filling because fat slows stomach emptying, not because the stomach digests fat.
  • Fiber is a carbohydrate that human enzymes cannot digest; it reaches the colon intact and feeds gut bacteria.
Check yourself

Check yourself: can you predict which path a meal takes?

1Multiple choiceChecked instantly

A chylomicron is a package of digested fat about to leave the gut. Which pathway does it take, and why?

  • AInto the portal vein, because the liver must process every absorbed nutrient first
  • BInto the lymphatic lacteals, because chylomicrons are too large for the blood capillaries in the villus
  • CBack into the stomach, because undigested fat is stored there until the next meal
  • DInto the colon, because fat is fermented by bacteria just like fiber
2Select all that applyChecked instantly

A meal has rice (carbohydrate), chicken (protein), and olive oil (fat). Which statements are true? Select all that apply — more than one is correct.

  • AThe rice begins being digested in your mouth before it reaches your stomach.
  • BThe chicken's proteins are first broken down in your stomach.
  • CThe olive oil is digested mainly in your stomach by bile.
  • DThe rice's glucose and the chicken's amino acids both reach the liver through the portal vein.
  • EThe olive oil's fatty acids are absorbed directly into the portal vein, like glucose.
3Short answerMarked by AI

A friend says, "Fat is digested in the stomach — that's why a fatty meal sits heavy." In 2–4 sentences, correct the site of fat digestion, explain why a fatty meal actually makes you feel full, and describe what bile does.

Graded on Corrects the digestion site · Explains the fullness mechanism · Describes bile's role

Lesson 17

Blood sugar and the insulin response

You will be able to describe how the body handles a rise in blood glucose and why insulin is released. Covers the role of the pancreas, GLUT4 transporters, and glycogen storage in liver and muscle. Prevents the belief that insulin is inherently fattening outside the context of energy balance.

30 min4 assessments

You've seen how digestion breaks down carbohydrates into glucose, which then enters your bloodstream. But that glucose can't just stay there — blood sugar must stay within a narrow range for your brain and other organs to work properly. So your body has a rapid, precise system to move that glucose out of the blood and into cells where it can be used or stored.

When blood glucose rises after a meal, special cells in your pancreas — the beta cells — sense the increase and release insulin. Insulin is a hormone that travels through the blood and acts like a signal: it tells cells in your liver, muscles, and fat tissue to take up glucose. In muscle and fat cells, insulin triggers GLUT4 transporters to move to the cell surface, creating a doorway for glucose to enter. Once inside, glucose can be used for energy immediately or stored for later. The liver and muscles store it as glycogen — a compact, ready-to-use fuel reserve. Fat cells store excess glucose as triglycerides.

Importantly, insulin itself doesn't make you gain fat. It's a storage hormone: it stores whatever energy is available. If you're in energy balance, that storage is mostly glycogen; if you're in a calorie surplus, some of it ends up as fat. Blaming insulin for fat gain is like blaming the mail carrier for delivering a package you ordered. The real driver is energy balance.

The insulin response: from meal to storage.

Analogy

Think of insulin as a master key that unlocks the doors to your body's energy warehouses. After a meal, glucose is like delivery trucks full of fuel waiting outside. Without insulin, the doors stay locked and the trucks pile up in the blood (high blood sugar). Insulin turns the key, the doors open, and the fuel is unloaded into cells — especially muscle and liver — where it's stacked as glycogen or, if the shelves are full, converted to fat for longer-term storage.

Where the analogy breaks down

This analogy suggests that without insulin, cells are completely sealed, but that's not true. Some glucose can enter cells through other transporters (like GLUT1) even without insulin — just enough for basic needs. Also, insulin doesn't just unlock doors; it also activates enzymes inside the cell that promote glycogen and fat synthesis. The key doesn't tell the warehouse workers what to do with the cargo — insulin does.

Common misconception

“"Insulin makes you fat, so eating carbs causes weight gain."”

Insulin does promote fat storage, and it spikes after carb-rich meals. Many diet books and influencers blame insulin for weight gain, so it feels logical: more insulin → more fat.

What is actually true

Insulin is a storage hormone, but what it stores depends on energy balance. In a calorie surplus, excess glucose gets stored as fat; in a deficit, insulin still helps store glucose as glycogen, not fat. The real cause of fat gain is consuming more calories than you burn over time, not insulin itself. People on low-carb diets often lose weight because they eat fewer calories overall, not because insulin is low.

  • After a meal, rising blood glucose triggers the pancreas to release insulin.
  • Insulin binds to receptors on liver, muscle, and fat cells, signaling them to take up glucose.
  • In muscle and fat cells, insulin causes GLUT4 transporters to move to the cell surface, allowing glucose entry.
  • The liver and muscles store glucose as glycogen; fat cells store it as triglycerides.
  • Insulin secretion decreases as blood glucose returns to normal (~70-100 mg/dL fasting).
  • Insulin is not inherently fattening; fat storage depends on overall energy balance, not insulin alone.
Check yourself
1Multiple choiceChecked instantly

Which of the following best describes the primary role of insulin after a carbohydrate-containing meal?

  • AIt breaks down glycogen into glucose to raise blood sugar.
  • BIt helps glucose enter cells and promotes its storage as glycogen or fat.
  • CIt stimulates the pancreas to release glucagon.
  • DIt converts fatty acids into glucose for the brain.
2Short answerMarked by AI

A person eats a meal containing 50g of carbohydrates. Describe the sequence of events from the rise in blood glucose to the storage of glucose as glycogen in the liver and muscle. Include the role of the pancreas and insulin.

Graded on Correct sequence and inclusion of pancreas and insulin · Mentions both liver and muscle glycogen storage and the return to normal

3Short answerMarked by AI

A friend claims that eating carbohydrates is unhealthy because it spikes insulin, which causes fat storage. Using your understanding of insulin's function and energy balance, explain why this claim is misleading.

Graded on Identifies that storage type depends on energy balance · Explains that insulin is necessary for glucose regulation and not inherently fattening

4EssayMarked by AI

Compare the body's blood glucose and insulin response to a sugary drink (high glycemic index) versus a whole-grain meal (lower glycemic index). Which leads to a more stable blood glucose and why? What are the implications for energy balance and long-term health?

Graded on Describes the difference in glucose and insulin response between the two foods · Explains which leads to more stable blood glucose and why · Discusses implications for energy balance and long-term health

Lesson 18

Blood glucose regulation

Normal blood glucose range (~70-100 mg/dL fasting). Sources: dietary carbs, glycogen breakdown, gluconeogenesis. Why stable glucose is important for brain function.

10 min2 assessments

Your blood doesn't swing wildly between a sugar crash and a sugar spike because your body runs a tight feedback loop. A fasting value between 70 and 100 mg/dL is normal. After a meal it may rise to 120–140 mg/dL, but it returns to baseline within two hours. Three sources keep that supply steady:

  • Dietary carbohydrate – broken down into glucose in the gut, absorbed into the bloodstream.
  • Glycogen breakdown – the liver stores about 100 g of glycogen; muscle stores more but keeps it for itself. Between meals the liver releases glucose from glycogen.
  • Gluconeogenesis – when glycogen runs low (after 12–18 hours of fasting), the liver makes new glucose from lactate, amino acids and glycerol.

Why the fuss? Your brain guzzles about 120 g of glucose per day and has almost no storage. A drop below 70 mg/dL starves the brain, causing dizziness, confusion, and eventually unconsciousness. Persistently high glucose (above 126 mg/dL fasting) damages blood vessels. The pancreas keeps this balance by releasing insulin when glucose is high and glucagon when it's low — the hormones you met in the previous lesson.

The glucose homeostatic loop. Insulin lowers blood glucose; glucagon raises it.

Analogy

Think of your blood glucose as the temperature inside a house. A thermostat (the pancreas) senses the temperature and sends a signal: too hot → turn on air conditioning (insulin) to cool down; too cold → turn on heating (glucagon) to warm up. The target temperature is the set point – about 37°C, just as your glucose set point is about 90 mg/dL.

Where the analogy breaks down

A house thermostat has a single fixed set point and a simple on/off switch. Your body adjusts the set point based on need – during exercise, muscles soak up extra glucose without a large insulin spike, and during illness or stress, cortisol can raise the set point. The body also has multiple parallel control systems (thyroid hormone, adrenaline, growth hormone) that fine-tune the response, whereas a thermostat has only one.

  • Normal fasting blood glucose is 70–100 mg/dL; below 70 is hypoglycaemic, above 126 is diabetic.
  • Glucose comes from three sources: dietary carbs, glycogen breakdown, and gluconeogenesis.
  • The brain consumes roughly 120 g of glucose daily and stores none, making a steady supply vital.
  • Insulin lowers blood glucose; glucagon raises it – these hormones form a negative feedback loop.
  • Hypoglycaemia (<70 mg/dL) impairs brain function; chronic hyperglycaemia damages blood vessels.
Common misconception

“Lower blood sugar is always better – it means I'm burning fat and being healthy.”

Weight‑loss culture often celebrates low insulin and 'fat‑burning mode'. A low blood sugar reading on a glucometer is sometimes associated with successful fasting or keto diets.

What is actually true

Blood sugar below 70 mg/dL (hypoglycaemia) is dangerous, not desirable. The brain depends on glucose; when levels fall too low, you lose coordination, become confused, and can lose consciousness. The body treats low glucose as an emergency and releases stress hormones (adrenaline, cortisol) to raise it – symptoms include shaking, sweating, and rapid heart rate. Chronic mild hypoglycaemia can also blunt cognitive performance. The goal is stable glucose, not low glucose.

Check yourself

Check your understanding of blood glucose sources and regulation.

1Multiple choiceChecked instantly

Which of the following is a source of blood glucose when you haven't eaten for 18 hours?

  • AGlycogen breakdown in muscle (directly released into blood)
  • BGluconeogenesis in the liver from lactate and amino acids
  • CDirect conversion of dietary fat into glucose
  • DGlucose stored in the brain
2Short answerMarked by AI

Explain why blood glucose remains stable during a 2‑hour endurance workout, even if the athlete has not eaten during the session. Name and describe the two main mechanisms that keep blood glucose from dropping too low.

Graded on Identifies both mechanisms by name · Explains how each mechanism raises blood glucose · Connects mechanisms to the exercise scenario

Lesson 19

Insulin's mechanism

Insulin released from beta cells in pancreas. Binds to receptors on muscle, fat, liver cells. Promotes GLUT4 translocation for glucose uptake. Also promotes glycogen and fat storage.

15 min3 assessments

After a meal, your blood glucose level rises. That glucose needs to get inside your cells to be used for energy or stored. But glucose cannot just drift through the cell membrane on its own – it needs a special door. The pancreas releases the hormone insulin to open those doors. This lesson walks you through the exact sequence of events, from the moment glucose rises to the moment it is safely stored.

Steps
0/6

Follow the steps insulin takes to get glucose into your cells. Each step must happen in order – skipping or breaking one leaves glucose stuck in the blood.

  1. Beta cells sense the rise

    The beta cells in your pancreas continuously monitor blood glucose. When glucose rises above the normal range (roughly 70–100 mg/dL fasting), they detect the increase and prepare to release insulin.

    If beta cells are damaged or destroyed (as in type 1 diabetes), this step never triggers and no insulin is released.

    Blood glucose is confirmed to be above the normal range.

  2. Insulin is released into the bloodstream

    Beta cells secrete insulin directly into the blood. Insulin is a small protein hormone that travels quickly throughout the body.

    Insufficient insulin release (type 2 diabetes early stage) means less insulin reaches target cells.

    Insulin levels in the blood rise.

  3. Insulin binds to receptors on target cells

    Insulin reaches the surface of muscle, fat, and liver cells and binds to insulin receptors. This binding is like a key in a lock – it changes the receptor's shape, starting a signalling cascade inside the cell.

    If the receptors are resistant (common in type 2 diabetes), the signal is weak even with normal insulin levels.

    The receptor changes shape, activating intracellular signals.

  4. GLUT4 vesicles move to the cell membrane

    Inside the cell, GLUT4 glucose transporters are stored in small vesicles. The insulin signal causes these vesicles to travel to the cell membrane and fuse with it, placing GLUT4 proteins into the membrane.

    Failure of translocation – the vesicles may not move or fuse – leaves the cell without glucose entry points.

    GLUT4 appears on the cell surface (can be measured by glucose uptake assays).

  5. Glucose enters the cell

    With GLUT4 now in the membrane, glucose can diffuse down its concentration gradient into the cell. The more GLUT4 present, the faster glucose enters.

    Without GLUT4 on the surface, glucose remains outside the cell, causing hyperglycemia.

    Blood glucose concentration begins to drop.

  6. Glucose is stored as glycogen or fat

    Inside the cell, glucose is quickly converted. In the liver and muscle, it is stored as glycogen. In fat cells (adipose tissue), it is converted to triglycerides and stored as fat. This lowers blood glucose back to normal.

    When storage capacity is reached (e.g., after a very large meal), excess glucose remains in the blood or is converted to fat beyond normal stores.

    Blood glucose returns to baseline (70–100 mg/dL).

Checklist
0/6

Insulin mechanism checklist

Check each item after studying the walkthrough. If any item is unclear, review the corresponding step.

A typical meal response

You eat a sandwich containing 50 g of carbohydrates. Your blood glucose rises from 90 mg/dL to 150 mg/dL. The beta cells in your pancreas sense this increase and release insulin. Insulin travels to your muscle cells, binds to receptors on their surface, and triggers GLUT4 vesicles to fuse with the cell membrane. Glucose enters the muscle cells, where it is rapidly converted to glycogen. Within two hours, your blood glucose returns to 90 mg/dL. If your insulin receptors were resistant, the same meal would keep your blood glucose above 140 mg/dL for hours, because glucose would not be cleared efficiently.

The step-by-step insulin mechanism from glucose rise to storage.

  • Insulin is released by pancreatic beta cells when blood glucose rises above the normal range.
  • Insulin binds to specific receptors on the surface of muscle, fat, and liver cells.
  • Receptor binding triggers a signalling cascade that moves GLUT4 storage vesicles to the cell membrane.
  • GLUT4 transporters allow glucose to enter the cell by facilitated diffusion.
  • Inside the cell, glucose is converted to glycogen (liver and muscle) or triglycerides (fat tissue).
  • This process is a negative feedback loop: high glucose triggers insulin, which lowers glucose, which then reduces insulin release.
  • Failure at any step (e.g., beta cell damage, receptor resistance, defective GLUT4 translocation) leads to hyperglycemia and diabetes.
Check yourself

Test your understanding of the insulin mechanism.

1Put in orderChecked instantly

Put the steps of insulin's mechanism in the correct order from the initial rise in blood glucose to glucose storage.

  • ABlood glucose rises after a meal.
  • BBeta cells detect high glucose and release insulin.
  • CInsulin binds to receptors on target cells.
  • DGLUT4 vesicles translocate to the cell membrane.
  • EGlucose enters the cell via GLUT4 transporters.
  • FGlucose is stored as glycogen or fat.
2Short answerMarked by AI

Explain why GLUT4 translocation is necessary for glucose uptake in muscle cells after a meal. What would happen if this process failed?

Graded on Explanation of why GLUT4 translocation is needed · Discussion of consequences of failure

3ProjectMarked by AI

Create a simple flowchart or written description that outlines the key steps of insulin's mechanism from the rise in blood glucose to the storage of glucose. Include the roles of the pancreas, insulin, receptors, GLUT4, and target tissues. Your deliverable should be a one-page document (text or diagram) that a peer could use to study the mechanism.

Graded on Completeness of steps · Accuracy of roles · Clarity and presentation

Lesson 20

Glycogen storage

Liver glycogen: maintains blood glucose. Muscle glycogen: fuel for exercise. Limits on storage capacity. How glycogen is replenished.

10 min4 assessments

In 'Blood sugar and the insulin response' you saw insulin push glucose into cells. Glycogen is what liver and muscle do with the surplus: they link the glucose molecules into a branched chain and park it for later. Two depots, two different jobs.

Liver glycogen — the blood-glucose buffer. The liver stores about 100 g of glycogen, up to 10% of its own weight. Your whole bloodstream carries only about 4 g of glucose — less than a teaspoon — so a steady release is what keeps you alive between meals. When blood glucose falls, the pancreas sends glucagon; the liver cleaves glycogen back into free glucose and releases it. Liver cells can do this because they carry the enzyme glucose-6-phosphatase. That enzyme is why you wake up with normal blood sugar after eight hours without food.

Muscle glycogen — private fuel. A typical adult stores 300-500 g in muscle, several times more than the liver — but it never reaches the blood. Muscle lacks glucose-6-phosphatase, so the glycogen stays locked inside as fuel for that same muscle, released by epinephrine and by the contraction itself. When your legs die at the end of a long run, the tank is dry.

Capped capacity. Each gram of glycogen is stored with about three grams of water, so every calorie of storage costs weight. Total stores, liver plus muscle, come to roughly 500 g — about 2,000 kcal, or 90-150 minutes of sustained hard exercise. Past that: the wall.

Refilling. Insulin rebuilds the liver store within hours of a meal. Muscle is hungriest for glucose in the first hour or two after exercise, and a full reload takes 24-48 hours of eating carbohydrates — about 5-7 g per kg of body weight per day.

Reference

Liver glycogen vs muscle glycogen — the two storage depots

Main job

Liver glycogen
Keeps blood glucose steady between meals and overnight
Muscle glycogen
Fuels the same muscle that stores it, during exercise

Typical amount

Liver glycogen
~100 g (up to ~10% of liver weight)
Muscle glycogen
~300-500 g (1-2% of muscle weight)

Breakdown signal

Liver glycogen
Glucagon (low blood glucose) and epinephrine
Muscle glycogen
Epinephrine and the muscle contraction itself

Can it feed the blood?

Liver glycogen
Yes — has glucose-6-phosphatase, exports free glucose
Muscle glycogen
No — lacks that enzyme; glucose stays trapped in the muscle

Runs out when

Liver glycogen
Overnight fast; fully emptied after ~24 h without food
Muscle glycogen
~90-150 min of sustained moderate-to-hard exercise

Refilled by

Liver glycogen
Carbohydrate meals (insulin); gluconeogenesis as backup
Muscle glycogen
Carbohydrate after exercise — fastest early, full reload in ~24-48 h

Each gram of glycogen is stored with about 3 g of water, so a full 500-g store adds roughly 2 kg of body weight.

The wall, in numbers

A 70 kg cyclist starts a hard ride with about 500 g of glycogen: 100 g in the liver, 400 g in muscle. At 4 kcal per gram, that is roughly 2,000 kcal of stored carbohydrate.

At race effort she burns about 120 g of carbohydrate per hour, mostly from muscle glycogen:

  • 1 hour → ~380 g left; fine.
  • 2 hours → ~260 g left; pace holds.
  • 3 hours → ~140 g left; muscle is nearly empty and the liver has spent its share defending blood glucose. Pace collapses — the wall.

Refilling works on the same numbers. In the first hour or two after exercise, a 70 kg athlete can rebuild glycogen at roughly 80-100 g per hour, so a post-ride meal with 50-100 g of carbohydrate (a banana plus a rice bowl) restarts the process at full speed. Full reload: 24-48 hours, about 400-500 g of total carbohydrate.

The catch: each gram of glycogen brings ~3 g of water. A fully reloaded athlete is carrying about 2 kg of extra water — visible on the scale the morning of a race.

Practice
0/10 known
1 / 10
Check yourself

Quick checks on how the two glycogen depots are built, spent and refilled.

1Fill the blanksChecked instantly
2Multiple choiceChecked instantly

You wake after an overnight fast; your last meal was ten hours ago, yet your blood glucose is normal. What is directly keeping it there?

  • AMuscle glycogen breaking down and releasing glucose into the blood
  • BLiver glycogen breaking down and releasing glucose into the blood
  • CFat tissue converting stored fat into glucose for the blood
  • DThe large reserve of glucose that circulates freely in the blood
3Select all that applyChecked instantly

An athlete just finished a hard two-hour ride and wants to refill muscle glycogen as quickly as possible. Which actions genuinely help? Select all that apply.

  • AEating 50-100 g of carbohydrate within the first hour or two after the ride
  • BEating high-carbohydrate meals spread across the next 24-48 hours
  • CSkipping carbohydrates until the next morning so the muscle 'soaks up' more later
  • DEating only protein and fat for the first day after the ride
  • EDoing another hard session before eating, to open up the stores further
4Fill the blanksChecked instantly

Lesson 21

Glucagon and fasting response

When blood sugar drops, alpha cells release glucagon. Promotes glycogen breakdown and gluconeogenesis. Opposes insulin action. Part of the counter-regulatory response.

10 min3 assessments

You already know how insulin lowers blood glucose after a meal. But what happens when you haven't eaten for hours? Your blood sugar starts to drop, and if it falls too low, your brain — which relies almost entirely on glucose — would starve.

The body's answer is glucagon. When blood glucose falls below about 4 mmol/L, the alpha cells of the pancreas (different cells from the beta cells that make insulin) release glucagon into the bloodstream. Glucagon tells the liver to do two things:

  1. 1.Break down stored glycogen into glucose (glycogenolysis) and release it into the blood.
  2. 2.Make new glucose from amino acids and other non-carbohydrate sources (gluconeogenesis).

At the same time, glucagon suppresses insulin release and reduces glucose uptake by most tissues, so the glucose that is produced stays in the blood for the brain and other essential organs. This whole system is called the counter-regulatory response — it opposes insulin and prevents hypoglycemia.

The glucagon response during fasting: how the liver restores blood glucose.

Analogy

Think of your body as a house with a heating system. When the temperature (blood glucose) drops below the thermostat setting, the furnace (glucagon) turns on and burns stored fuel (glycogen) to warm the house back up. That's glycogenolysis — using what's already in the fuel tank.

But glucagon also does something a furnace cannot: it builds new fuel from scratch. During a prolonged fast, the liver converts amino acids and other molecules into glucose, a process called gluconeogenesis. This is like the furnace being able to construct new logs from old furniture when the woodpile runs out.

Where the analogy breaks down

A furnace only burns stored fuel; it cannot create new fuel from non-fuel materials. Glucagon's ability to perform gluconeogenesis — creating glucose from protein and fat metabolites — goes beyond the analogy. Also, the thermostat analogy suggests a simple on/off switch, whereas glucagon secretion is graded and influenced by other hormones.

  • Glucagon is released by the alpha cells of the pancreas when blood glucose falls below normal.
  • Glucagon stimulates glycogenolysis — the breakdown of liver glycogen into glucose.
  • Glucagon stimulates gluconeogenesis — the creation of new glucose from amino acids and other substrates.
  • Glucagon inhibits insulin secretion and reduces glucose uptake by non-essential tissues.
  • The glucagon response is part of the counter-regulatory system that prevents hypoglycemia.
Go deeper

Read the Wikipedia article on glucagon for a deeper look at its molecular mechanism and clinical significance.

Check yourself

Check your understanding of glucagon and the fasting response.

1Multiple choiceChecked instantly

Which of the following is NOT an effect of glucagon?

  • AStimulates glycogenolysis in the liver
  • BStimulates gluconeogenesis
  • CStimulates insulin secretion
  • DRaises blood glucose levels
2Short answerMarked by AI

You have not eaten for 14 hours. Describe the sequence of hormonal events that maintain your blood glucose level. Be specific about which cells release which hormone and what processes are activated.

Graded on Identifies glucagon as the primary hormone and its source · Describes the metabolic processes activated · Explains the overall effect on blood glucose

3Short answerMarked by AI

A patient is diagnosed with a glucagon-secreting tumor (glucagonoma). Predict the likely effects on their blood glucose levels and on their insulin secretion. Explain the mechanisms behind your predictions.

Graded on Predicts blood glucose levels · Predicts insulin secretion · Explains the counter-regulatory nature

Lesson 22

Fat storage and fat burning

You will be able to explain how dietary fat is stored and how stored body fat is released and burned for energy. Covers adipose tissue, lipoprotein lipase, hormone-sensitive lipase, and beta-oxidation. Prevents the belief that eating fat directly causes body fat gain.

30 min3 assessments

You already know insulin as the hormone that clears sugar from your blood — it pushes glucose into cells and packs the surplus into glycogen. This node is the second act of that story: where dietary fat goes after a meal, and where the fat on your body comes from when insulin drops and your body needs fuel.

Start with a number that surprises most people. A typical adult carries about 100,000 kcal of energy as body fat — enough to run about 30 marathons back to back. That fat is not a passive lump; it is a fuel depot that your body deposits into and withdraws from continuously. The whole game is controlled by two enzymes and one hormone switch.

An enzyme called lipoprotein lipase (LPL) sits on the inside of the capillary walls in fat tissue, muscle, and heart. When you eat fat, it travels in the blood inside chylomicrons — tiny particles that act as delivery trucks. When a chylomicron passes a capillary in fat tissue, LPL reaches in and clips the triglycerides into free fatty acids and glycerol. The fatty acids slip through the capillary wall, into the fat cell, and get reassembled back into triglycerides for storage. LPL is strongly activated by insulin. So after a meal — exactly when insulin is high — fat tissue shifts into receive mode and pulls fat out of the blood.

That is the crucial point for the misconception this node exists to kill: eating fat does not directly make body fat. Dietary fat has to be captured by LPL and stored as triglyceride. The same enzyme is what stores carbohydrate-derived fat too — when you eat more carbs than your glycogen can hold, the liver converts the surplus into fat, ships it out as VLDL particles, and LPL stores it in the same fat cells. The fat on your body is a mix of the fat you ate and the fat your liver built. The gatekeeper in both cases is LPL.

Now for the other direction: fat burning. Stored triglyceride sits inside the fat cell as a droplet. It cannot leave until another enzyme, hormone-sensitive lipase (HSL), breaks it down into free fatty acids and glycerol. HSL is activated by epinephrine, glucagon, and growth hormone — the signals of fasting, stress, and exercise. It is inhibited by insulin. So the same hormone that throws the LPL switch to "store" also throws the HSL switch to "stop releasing." You cannot store and release fat at the same time; that is why you do not burn fat while insulin is high.

When HSL releases fatty acids into the blood, they travel bound to albumin to tissues that need fuel. Muscle, liver, and heart pull them in and run beta-oxidation: a mitochondrial assembly line that chops the fatty acid two carbons at a time into acetyl-CoA, which feeds the Krebs cycle and produces ATP. That is what "fat burning" actually means — not fat disappearing in a puff of heat, but fatty acids being oxidized for energy, mostly at low-to-moderate intensity when oxygen is available.

The diagram below tracks one fatty acid through both phases. Read it as a loop: meal → insulin high → LPL stores → fast/exercise → glucagon high → HSL releases → beta-oxidation → energy.

The fat cycle: LPL stores after a meal, HSL releases during fasting or exercise, beta-oxidation burns.

Analogy

Think of your body as a house with two doors and one manager. The manager is insulin. One door is labeled IN — the door used by a delivery service called LPL. When the manager is around (after a meal), the delivery service is active: packages of fat arrive and get shelved in the pantry, the fat cell. The pantry is huge — it can hold tens of thousands of calories with no complaint.

The other door is labeled OUT, and its key is held by a different worker, HSL. HSL is only allowed to work when the manager is away or distracted — that is, when insulin is low. Then boxed fats are taken off the pantry shelves, opened, and sent out to rooms that need fuel (muscles burning them in mitochondria).

The shift change is the key: when the manager is present, the delivery door is open and the out door is locked. At any moment, the house is either receiving or sending, never both at full rate.

Where the analogy breaks down

A house pantry never decides to send its own shelves out to be burned - HSL breaks down what is already stored, while the pantry metaphor suggests only incoming goods move. Also, the manager does not personally open and close doors; insulin works by changing enzyme activity inside cells, and the doors are not perfectly one-way: some fatty acids enter muscles directly from chylomicrons without being stored first.

Common misconception

“Eating fat makes you fat, directly — the fat you eat goes straight onto your hips.”

Fat is calorie-dense, fat in food is chemically similar to body fat, and people who eat fatty diets often do gain weight, so the cause seems obvious: fat in equals fat on.

What is actually true

Dietary fat cannot enter fat cells by itself. It must be broken down by LPL and reassembled as triglyceride inside the fat cell, and LPL is activated by insulin — so the amount of fat stored depends as much on your insulin levels and energy balance as on how much fat you ate. Excess carbohydrate also becomes body fat through the same LPL pathway. What predicts fat gain is total energy surplus, not dietary fat per se.

Two meals, one fat cell: what actually gets stored

You eat a meal with 30 g of fat and 80 g of carbohydrate. The fat enters the blood in chylomicrons. Because the meal raises blood glucose, the pancreas releases insulin, and insulin activates LPL in your fat tissue. The LPL clips the chylomicrons' triglycerides, and most of those 30 g of fatty acids enter fat cells and are re-esterified into stored triglyceride. At the same time, insulin tells the liver to take up glucose; about 15–20 g fills glycogen, and anything beyond that is converted to fatty acids, packaged into VLDL, and delivered by the same LPL to the same fat cells. Net effect: the fat cell grows, and its new content is a mixture of the fat you ate and fat the liver built from the carbs you ate.

Now skip dinner. Eight hours later, blood glucose is low, insulin is low, and glucagon is up. HSL is no longer inhibited, so it breaks down the stored triglyceride in the fat cell. Free fatty acids leave the fat cell, bind to albumin in the blood, and travel to muscle. In the muscle mitochondria, beta-oxidation removes two-carbon units from each fatty acid, converting them into acetyl-CoA; each acetyl-CoA then enters the Krebs cycle and drives ATP production. The net result of the fast is that some stored fat was oxidized for energy.

The arithmetic shows why the panic about fat is misplaced: it is not the fat itself that decides whether the fat cell grows or shrinks, but which enzyme is active — LPL when insulin is high, HSL when insulin is low. Both meals and fasts end with the fat cell's state reflecting your overall energy balance, not the fat content of your last meal.

  • Lipoprotein lipase (LPL) is the enzyme that stores fat: it clips triglycerides from chylomicrons and VLDL at the capillary wall so fatty acids can enter fat cells.
  • Insulin activates LPL in fat tissue, so the fed state is when fat storage happens – both from dietary fat and from surplus carbohydrate converted to fat by the liver.
  • Hormone-sensitive lipase (HSL) releases stored fat: it breaks down the triglyceride droplet into free fatty acids and glycerol, and it is activated by glucagon, epinephrine, and growth hormone.
  • Insulin inhibits HSL, which is why fat release is low after a meal and rises during fasting, low-intensity exercise, or any state with low insulin.
  • Beta-oxidation is the mitochondrial process that chops fatty acids into acetyl-CoA, feeding the Krebs cycle to produce ATP – this is what 'fat burning' literally means.
  • Stored body fat is one shared pool: it receives fatty acids from dietary fat and from liver-made fat, so total energy balance, not fat intake alone, determines whether the pool grows.
Check yourself

Check whether the mechanism stuck.

1Multiple choiceChecked instantly

After a large meal, insulin levels rise. Which enzyme becomes more active in fat tissue, pulling fatty acids into fat cells for storage?

  • ALipoprotein lipase (LPL)
  • BHormone-sensitive lipase (HSL)
  • CBeta-oxidation
  • DGlycogen synthase
2Short answerMarked by AI

You eat a large pasta meal, so insulin is high. Three hours later you skip a snack and go for a 45-minute easy jog. Describe what happens to (1) lipoprotein lipase activity and (2) hormone-sensitive lipase activity as you go from the meal to the jog, and (3) where the energy for the jog comes from. Use the terms 'store' and 'release' in your answer.

Graded on Identifies the fed-state storage pathway with LPL and insulin · Describes the switch to HSL during the jog · Names the fuel source for the jog

3EssayMarked by AI

A friend tells you they are removing all fat from their diet because 'eating fat makes you fat.' Evaluate that claim using what you now know about LPL, HSL, and energy balance. In your response, (1) explain why dietary fat does not automatically become body fat, (2) give one situation where eating fat does not cause fat gain, and (3) give one situation where eating very little fat could still lead to fat gain.

Graded on States a clear verdict and the LPL mechanism · Provides a condition where fat intake does not cause fat gain · Provides a condition where low-fat intake still causes fat gain

Lesson 23

Adipose tissue and fat storage

White vs brown adipose tissue. Fat cells (adipocytes) store triglycerides. How dietary fat is packaged into chylomicrons and delivered to adipose tissue via lipoprotein lipase.

12 min4 assessments

When you eat a meal containing fat, that fat doesn't just float through your body. It's packaged, shipped, and stored in specialized cells called adipocytes, which make up adipose tissue. Adipose tissue comes in two main types: white adipose tissue (WAT) and brown adipose tissue (BAT). White adipose tissue is what you probably think of as body fat—it stores energy as a single large droplet of triglyceride per cell, provides insulation, and cushions organs. Brown adipose tissue, in contrast, contains many small lipid droplets and dense mitochondria. Its job isn't storage—it's heat production, through a process called non-shivering thermogenesis.

But how does dietary fat actually reach these cells? After digestion, fat is reassembled into triglycerides and packed into chylomicrons in the cells of your small intestine. Chylomicrons enter your lymphatic system, then your bloodstream. In the capillaries of adipose tissue, an enzyme called lipoprotein lipase (LPL) sits on the inner wall of the vessel. LPL breaks the triglycerides in chylomicrons into free fatty acids and monoglycerides. The free fatty acids slip across the capillary wall into the adipocyte, where they are rejoined into triglycerides and stored in the lipid droplet. This process is triggered by insulin after a meal.

You've already seen how stored fat is released and burned—now you know the place it comes from and how it gets there.

Reference

White vs Brown Adipose Tissue

Main function

White Adipose Tissue
Store energy as triglycerides, insulation, cushioning
Brown Adipose Tissue
Generate heat via uncoupled respiration (thermogenesis)

Location

White Adipose Tissue
Subcutaneous (under skin), visceral (around organs)
Brown Adipose Tissue
Neck, shoulders, along spine (in adults); more abundant in infants

Lipid droplets per cell

White Adipose Tissue
One large droplet (unilocular)
Brown Adipose Tissue
Many small droplets (multilocular)

Mitochondria content

White Adipose Tissue
Low
Brown Adipose Tissue
High

Color

White Adipose Tissue
White or yellowish (due to stored fat)
Brown Adipose Tissue
Brown (due to dense mitochondria and blood supply)

Thermogenic protein

White Adipose Tissue
Low or absent UCP1
Brown Adipose Tissue
High UCP1 (uncoupling protein 1)

Primary stimulus for storage

White Adipose Tissue
Insulin after a meal
Brown Adipose Tissue
Cold exposure (via sympathetic nervous system)

Primary stimulus for release

White Adipose Tissue
Fasting, exercise (hormone-sensitive lipase)
Brown Adipose Tissue
Cold (UCP1 activation)

Brown adipose tissue is much less abundant in adults than in infants, but it remains metabolically active and can be recruited with habitual cold exposure.

Practice
0/7 known
1 / 7

From butter to belly fat: one triglyceride's journey

You eat a slice of toast with butter. Here's where that butterfat goes:

  1. 1.Digestion: In your small intestine, the butter's triglycerides are broken down into free fatty acids and monoglycerides, then absorbed by intestinal cells.
  2. 2.Reassembly: Inside those cells, the pieces are reassembled into triglycerides again and packed into chylomicrons.
  3. 3.Exit: Chylomicrons enter lymphatic vessels in the villi, then empty into your bloodstream via the thoracic duct.
  4. 4.Arrival: The chylomicrons travel through your arteries. When they reach capillaries in adipose tissue (say, around your hips or belly), they slow down.
  5. 5.Unloading: There, lipoprotein lipase (LPL) anchored to the capillary wall clips the triglycerides inside the chylomicron into free fatty acids and monoglycerides.
  6. 6.Entry: Free fatty acids diffuse out of the capillary and into the nearest adipocyte.
  7. 7.Storing: Inside the adipocyte, enzymes reattach the fatty acids to a glycerol backbone, recreating triglycerides. These are packed into the cell's giant lipid droplet.

After this meal, insulin levels rise, which tells LPL to become more active in adipose tissue. That's why eating carbs alongside fat can encourage more fat storage — insulin primes the machinery.

Go deeper

For more detail on the cellular structure of white and brown adipose tissue, and the molecular details of thermogenesis.

Check yourself

Check your understanding of adipose tissue and fat storage.

1Multiple choiceChecked instantly

Which type of adipose tissue is specialized for heat generation through uncoupled respiration?

  • AWhite adipose tissue
  • BBrown adipose tissue
  • CChylomicrons
  • DLipoprotein lipase
2Select all that applyChecked instantly

After a meal, which of the following must be present for dietary fat to be stored in an adipocyte? (Select all that apply.)

  • AChylomicrons
  • BLipoprotein lipase
  • CGlucagon
  • DFree fatty acids already in the blood
3Fill the blanksChecked instantly
4Select all that applyChecked instantly

Consider a person with a genetic deficiency that prevents lipoprotein lipase from functioning. Which of the following would you expect to observe? (Select all that apply.)

  • AReduced ability to store dietary fat in adipose tissue
  • BElevated levels of chylomicrons in the blood after a fatty meal
  • CIncreased body heat production due to brown fat activation
  • DLower blood triglyceride levels immediately after eating

Lesson 24

Lipoprotein lipase

Enzyme on capillary walls that breaks down triglycerides from chylomicrons and VLDL into free fatty acids for uptake into cells. Higher LPL activity in fat cells promotes fat storage.

12 min3 assessments

You've just eaten a meal with fat in it. That fat, mostly triglycerides, travels from your gut through your bloodstream wrapped in a chylomicron — a delivery capsule. The chylomicron is too big to enter your cells directly. So your body stations an enzyme on the inner walls of your capillaries — lipoprotein lipase (LPL) — that reaches out, grabs the chylomicron, and clips the triglycerides apart into free fatty acids and glycerol. The free fatty acids then slip through the capillary wall into the nearby cell, where they are either burned for energy or re-assembled into triglycerides and stored.

LPL is not everywhere at once. It sits on the capillary walls of muscle, heart, and adipose (fat) tissue. Where it is most active decides where the fat ends up. After a meal, insulin rises and tells LPL in fat tissue to get busy — that meal's fat goes into storage. During exercise, muscle cells make their own LPL more active, so circulating fat is pulled into muscle to be burned instead. You have the same enzyme doing opposite things depending on which tissue turned it on.

Steps
0/5

Follow what happens to a single chylomicron carrying triglycerides from a fatty meal to a fat cell. Each step is a real event in your body.

  1. Chylomicron enters the capillary

    A chylomicron, about 0.5 micrometers across, floats through the bloodstream and reaches a capillary in adipose tissue. It is too large to pass through the capillary wall.

    If the capillary is damaged or inflamed, LPL may not be present on the endothelium. The chylomicron sails past without unloading.

    The chylomicron is still intact and full of triglycerides.

  2. LPL binds to the chylomicron

    Lipoprotein lipase, anchored to the capillary wall by heparan sulfate proteoglycans, binds to the chylomicron. This binding is reversible — the chylomicron can detach if LPL is not active.

    Low insulin levels (fasting state) reduce LPL activity in adipose tissue. The binding happens but the enzyme does not work efficiently.

    LPL is physically attached to the chylomicron.

  3. LPL hydrolyzes triglycerides

    LPL cleaves the triglyceride molecule into one molecule of glycerol and three molecules of free fatty acids. This happens at the surface of the chylomicron, one triglyceride at a time.

    If the chylomicron has a mutation in apoC-II (a cofactor), LPL cannot hydrolyze. This causes familial chylomicronemia — triglycerides stay in the blood.

    Free fatty acids appear in the space between the capillary and the fat cell.

  4. Free fatty acids enter the fat cell

    The free fatty acids diffuse across the capillary wall and through the interstitial fluid, then cross the fat cell membrane. They do not need a transporter — they are small and lipid-soluble.

    If the fat cell is already full (obesity), it may resist taking up more fatty acids. They remain in the blood and are taken up by other tissues or the liver.

    Fatty acid concentration inside the fat cell rises.

  5. Fat cell re-esterifies fatty acids into triglycerides

    Inside the fat cell, the free fatty acids are combined with glycerol-3-phosphate to form new triglycerides. These triglycerides are stored in a single large lipid droplet that fills most of the cell.

    If the cell cannot produce enough glycerol-3-phosphate (rare, but happens in starvation), the fatty acids cannot be stored and may be released back out.

    The lipid droplet grows slightly. The chylomicron is now smaller and is now called a chylomicron remnant.

Checklist
0/5

LPL activity checklist

Keep this open while you work through the scenario. Each item is a condition that must be true for fat storage via LPL to proceed.

Decide

You are a clinical researcher reviewing a patient's blood work. The patient, a 45-year-old woman, has fasting triglycerides of 1,200 mg/dL (normal is <150). She has no diabetes, no kidney disease, and her liver enzymes are normal. Her blood plasma looks milky after a meal. You suspect a problem with lipoprotein lipase.

You order a test: after a fatty meal, you measure LPL activity in a sample of adipose tissue. The result comes back: LPL activity is 10% of normal. What is the most likely cause?

Check yourself

Check your understanding of what LPL does and what happens when it fails.

1Put in orderChecked instantly

Arrange these events in the order they happen when a chylomicron carrying triglycerides arrives at a capillary in adipose tissue. Start with the first event.

  • AFree fatty acids diffuse into the fat cell
  • BLPL anchors to the chylomicron via apoC-II
  • CLPL hydrolyzes triglycerides into free fatty acids and glycerol
  • DChylomicron enters the capillary
  • EFat cell re-esterifies free fatty acids into triglycerides for storage
2Short answerMarked by AI

A patient has a mutation that prevents LPL from binding to chylomicrons. Explain why their blood triglycerides would be elevated after a fatty meal, and why their fat cells would not grow larger despite eating a high-fat diet.

Graded on Identifies the binding failure as the cause of elevated triglycerides · Explains why fat cells do not grow · Uses correct terminology

3Short answerMarked by AI

During exercise, muscle cells increase their own LPL activity. Explain how this shifts the destination of circulating triglycerides compared to the fed state, and why this is beneficial for the athlete.

Graded on Compares fed state vs exercise state for LPL activity · Explains the benefit to the athlete

Lesson 25

Hormone-sensitive lipase

Enzyme that breaks down stored triglycerides in fat cells into free fatty acids and glycerol for release into bloodstream. Activated by epinephrine, glucagon, and growth hormone. Inhibited by insulin.

12 min3 assessments

Hormone-sensitive lipase (HSL) is the enzyme in fat cells that breaks down stored triglycerides into free fatty acids and glycerol. It is the gatekeeper of lipolysis—the release of fat for energy. HSL is activated when your body needs fuel: during exercise, fasting, or stress. The activation cascade is a strict sequence: a hormone (epinephrine, glucagon, or growth hormone) binds to a receptor on the fat cell surface, triggering a rise in cyclic AMP (cAMP) inside the cell. cAMP activates protein kinase A (PKA), which then phosphorylates HSL at specific serine residues. Once phosphorylated, HSL moves to the lipid droplet and hydrolyzes triglycerides. Insulin, released after eating, stops this cascade at multiple points—most importantly by lowering cAMP through phosphodiesterase activation. Without HSL's activation, fat stays stored.

HSL activation cascade

Steps
0/6

To determine whether HSL is actively breaking down fat, you need to verify each step of the activation cascade in order. Missing one link means lipolysis is not happening. Follow these steps to assess HSL activation in a fat cell preparation.

  1. Check for the hormonal signal

    Look for the presence of epinephrine, glucagon, or growth hormone in the blood or medium. These hormones bind to G-protein-coupled receptors (β-adrenergic or similar) on the fat cell surface. If only insulin is present, stop: the cascade is inhibited from the start.

    After a meal, insulin dominates and blocks the cascade. Even if epinephrine is present, insulin will blunt the response.

    Hormone levels confirmed by ELISA or bioassay.

  2. Verify adenylyl cyclase activation

    When the hormone binds, adenylyl cyclase is activated and converts ATP to cyclic AMP. Measure intracellular cAMP using a competitive ELISA or a fluorescent sensor.

    Insulin activates phosphodiesterase 3B (PDE3B), which degrades cAMP. High insulin can prevent cAMP from rising even if AC is active.

    cAMP concentration is at least 2× the resting level.

  3. Confirm PKA activation

    cAMP binds to the regulatory subunits of protein kinase A (PKA), causing the catalytic subunits to be released and become active. Assay PKA activity by adding a synthetic substrate (e.g., kemptide) and measuring phosphate transfer.

    If cAMP is low (due to PDE3B activity), PKA remains bound and inactive.

    PKA activity is significantly higher than control.

  4. Check HSL phosphorylation

    Active PKA phosphorylates HSL at serine 563, 659, and 660 (human numbering is species-dependent). Use a phospho-specific antibody (e.g., anti-phospho-HSL Ser660) on a Western blot of fat cell lysates.

    If PKA is inactive, the band will be absent or faint.

    A clear phospho-HSL band at ~84 kDa.

  5. Assess triglyceride hydrolysis

    Phosphorylated HSL translocates from the cytosol to the lipid droplet surface. There it interacts with lipid droplet proteins to access triglycerides. Measure free fatty acid release into the medium using a colorimetric assay.

    If perilipin is not also phosphorylated, HSL may not get full access. But for this node, focus on HSL.

    Free fatty acid concentration in the medium increases detectably.

  6. Measure fatty acid release into the bloodstream

    Free fatty acids are exported via transporters and bind to albumin in the bloodstream. Collect a plasma sample and assay non-esterified fatty acids (NEFA) using an enzymatic kit.

    Re-esterification inside the cell can reduce release. Ensure glycerol is available for triglyceride resynthesis if needed.

    Plasma NEFA level rises within minutes of stimulation.

Checklist
0/6

HSL Activation Field Checklist

Use this checklist when troubleshooting a lipolysis experiment.

HSL activation during fasted exercise

A 70 kg athlete runs 10 km after an overnight fast (12–16 hours). Her blood glucose is ~4.5 mmol/L and insulin is low (∼3 μU/mL). Glucagon and epinephrine rise as exercise begins.

  • Step 1–2: Epinephrine binds to β-adrenergic receptors on fat cells; adenylyl cyclase produces cAMP; intracellular cAMP levels triple.
  • Step 3–4: cAMP activates PKA, which phosphorylates HSL at Ser660.
  • Step 5–6: HSL hydrolyzes stored triglycerides. Free fatty acids (mainly oleic and palmitic) are released into the bloodstream, peaking at ∼0.8 mmol/L after 30 minutes.

These fatty acids are taken up by muscle and other tissues for beta-oxidation. The released glycerol goes to the liver for gluconeogenesis, helping maintain blood glucose during the run.

If the athlete had eaten a carbohydrate-rich meal 1 hour before, insulin would have been high, HSL would remain largely inactive, and fat oxidation would be suppressed—she would rely more on muscle glycogen instead.

Check yourself

Test your understanding of HSL activation.

1Put in orderChecked instantly

Place the following steps of HSL activation in the correct order, starting from the hormonal signal to the final release of fatty acids.

  • AHormone (epinephrine/glucagon) binds to receptor
  • BAdenylyl cyclase converts ATP to cAMP
  • CcAMP activates protein kinase A (PKA)
  • DPKA phosphorylates hormone-sensitive lipase (HSL)
  • EHSL hydrolyzes triglycerides into free fatty acids and glycerol
  • FFree fatty acids are released into the bloodstream
2Short answerMarked by AI

Explain why HSL remains inactive after a large meal even if epinephrine levels are normal.

Graded on Identifies the primary inhibitor (insulin) · Explains the mechanism of inhibition (cAMP reduction via PDE3B) · Connects to the outcome (HSL remains inactive)

3Short answerMarked by AI

A person has been fasting for 16 hours. Their insulin is low and glucagon is elevated. Predict the activity of hormone-sensitive lipase in their fat cells and the expected change in blood free fatty acid levels. Then explain how this helps maintain blood glucose levels.

Graded on Predicts HSL activity and FFA levels correctly · Explains the signal cascade (reduced insulin, increased glucagon → cAMP → PKA → HSL phosphorylation) · Connects glycerol release to gluconeogenesis for blood glucose maintenance

Lesson 26

Beta-oxidation and fat burning

Process by which fatty acids are broken down in mitochondria to generate acetyl-CoA for the Krebs cycle. Yields ATP. Key to endurance exercise and fasting metabolism.

15 min3 assessments

You've already seen how stored fat is released from adipose tissue and enters the bloodstream. But for that fat to actually produce energy, it must be broken down inside your mitochondria. That process is beta-oxidation — a cycle that chops fatty acids into two-carbon pieces you can burn.

Beta-oxidation happens step-by-step inside the mitochondrial matrix. Each cycle removes two carbons from the carboxyl end of the fatty acid, producing one molecule of acetyl-CoA (which enters the Krebs cycle), plus one FADH₂ and one NADH (which feed the electron transport chain). The cycle repeats until the entire chain is cleaved into acetyl-CoA molecules.

The word "beta" refers to the beta carbon — the second carbon from the carboxyl group. The oxidation event happens precisely at that position. Each turn of the cycle requires four enzymatic steps:

StepReactionCofactorProduct
1Oxidation of acyl-CoA to enoyl-CoAFAD → FADH₂trans-Δ²-enoyl-CoA
2Hydration to hydroxyacyl-CoAH₂OL-3-hydroxyacyl-CoA
3Second oxidation to ketoacyl-CoANAD⁺ → NADH3-ketoacyl-CoA
4Thiolysis cleaves two-carbon unitCoA-SHshorter acyl-CoA + acetyl-CoA

A 16-carbon palmitic acid goes through 7 cycles, producing 8 acetyl-CoA, 7 FADH₂, and 7 NADH. When those are fully oxidised via the Krebs cycle and electron transport chain, the net ATP yield is about 106 molecules (minus 2 ATP used to activate the fatty acid in the cytoplasm). That's far more energy than glucose provides per gram — which is why fat is your body's long-term fuel reserve.

One cycle of beta-oxidation. The four steps remove two carbons and produce one acetyl-CoA, one FADH₂, and one NADH. The shortened chain re-enters the cycle.

Analogy

Think of beta-oxidation like cutting a chain of paper clips. Each time you cut at the second link, you remove one paper clip (acetyl-CoA) and slide the rest of the chain back into the cutter. The cutter only works at the second link from the end — that's why it's called beta-oxidation (the second carbon). Each cut also generates a little energy the machine can use (FADH₂, NADH).

Where the analogy breaks down

Paper clips are identical units cut independently; in beta-oxidation, the chain is a molecule with a specific orientation, and the removed two-carbon piece is not pre-formed but produced by the reaction. Also, the 'energy' from the cut (FADH₂, NADH) is not used by the cutting machine itself but by other cellular processes.

Common misconception

“Beta-oxidation only happens when you are starving or in ketosis.”

People associate fat burning with low-carb diets or fasting, and media often says 'your body burns fat for fuel' only during starvation.

What is actually true

Beta-oxidation operates at a low baseline rate all the time, even after a meal. It is regulated by the concentration of malonyl-CoA, which rises when glucose is abundant (inhibiting the carnitine shuttle) and falls during fasting (allowing more fat entry into mitochondria). The switch is not on/off — it's gradual, like a dimmer.

  • Beta-oxidation occurs in the mitochondrial matrix, not in the cytoplasm.
  • Each cycle shortens the fatty acid by two carbons and produces one acetyl-CoA, one FADH₂, and one NADH.
  • The four steps are: oxidation, hydration, oxidation, thiolysis — in that order.
  • Palmitic acid (16 carbons) yields 7 cycles, 8 acetyl-CoA, and roughly 106 net ATP.
  • The carnitine shuttle controls entry of fatty acids into the mitochondria and is inhibited by malonyl-CoA.
  • Beta-oxidation runs continuously at a low level and accelerates when insulin drops and glucagon rises.
Check yourself

Test your understanding of beta-oxidation.

1Multiple choiceChecked instantly

What molecule directly inhibits the carnitine shuttle, thus regulating the entry of fatty acids into the mitochondria and the rate of beta-oxidation?

  • AInsulin
  • BMalonyl-CoA
  • CGlucagon
  • DAMP
2Short answerMarked by AI

Calculate the approximate net ATP yield from a 12-carbon saturated fatty acid (lauric acid). Show your work step by step, including the number of beta-oxidation cycles, the total acetyl-CoA produced, the ATP from each cycle (FADH₂ and NADH), the ATP from each acetyl-CoA in the Krebs cycle, and the activation cost. Use the standard approximations: each FADH₂ → 1.5 ATP, each NADH → 2.5 ATP, each GTP → 1 ATP, activation costs 2 ATP.

Graded on Calculates number of cycles correctly · Correctly accounts for ATP from redox per cycle · Correctly calculates ATP from acetyl-CoA in Krebs cycle · Includes activation cost and final net ATP

3Short answerMarked by AI

A sports supplement company advertises a product that 'directly enters beta-oxidation to boost fat burning.' Considering the regulation of beta-oxidation, explain why this claim may be misleading. What is the primary rate-limiting step for beta-oxidation, and how does the cell control it?

Graded on Identifies rate-limiting step · Explains regulation via malonyl-CoA · Evaluates the supplement claim critically

Lesson 27

Protein turnover and muscle maintenance

You will be able to describe how dietary protein is used to repair and build body tissues. Covers amino acid pools, muscle protein synthesis versus breakdown, and the concept of a complete protein. Prevents the belief that eating more protein automatically builds more muscle.

25 min3 assessments

Your body is constantly breaking down and rebuilding its proteins — a process called protein turnover. Every day, about 250–300 grams of protein are broken down in an average adult, mostly from muscle. That sounds like a lot, but you only need to eat about 50–80 grams of protein daily. How is that possible? Because your body recycles amino acids.

When you eat protein, it's digested into amino acids that enter the amino acid pool — a mixture of free amino acids in your blood and tissues. From there, cells can grab what they need to build new proteins (muscle, enzymes, hormones) or burn amino acids for energy. Meanwhile, old proteins are constantly being dismantled, releasing their amino acids back into the pool. The net result is that you only need to replace the amino acids that are lost (about 10–15% of the pool each day) through diet or that are used for energy.

Muscle maintenance depends on the balance between muscle protein synthesis (MPS) and muscle protein breakdown (MPB). When MPS exceeds MPB, you gain muscle; when MPB exceeds MPS, you lose muscle. Eating protein stimulates MPS, especially when it contains the amino acid leucine. But there's a ceiling: after about 20–30 grams of high-quality protein in a meal, MPS plateaus. Extra protein beyond that is mostly oxidized or stored as fat, not turned into more muscle.

Protein turnover: dietary protein enters the amino acid pool, which supplies muscle synthesis and other processes. Muscle proteins are constantly broken down and rebuilt.

Analogy

Think of your body's proteins as a brick building that's constantly being renovated. The amino acid pool is the pile of bricks and mortar available on site. Every day, workers (enzymes) take down some old bricks (protein breakdown) and use the recycled bricks plus new ones from deliveries (dietary protein) to build new walls (protein synthesis). As long as the number of bricks going in equals the number coming out, the building stays the same size. If deliveries increase, you can build more — but only up to the capacity of the work crew. If deliveries stop, the crew keeps taking bricks from the building to use elsewhere, and the building shrinks.

Where the analogy breaks down

In a real building, you can stockpile bricks indefinitely. In your body, excess amino acids cannot be stored long-term; they are quickly converted to glucose or fat or burned for energy. Also, the building has a fixed blueprint; your body's protein turnover is dynamic and adjusts to exercise, illness, and feeding.

  • Protein turnover is the continuous cycle of breaking down and rebuilding body proteins, with about 250–300 g recycled daily.
  • The amino acid pool is a temporary reservoir of free amino acids that supplies all protein synthesis needs.
  • Muscle protein synthesis (MPS) and muscle protein breakdown (MPB) determine net muscle gain or loss.
  • Dietary protein stimulates MPS, but the effect plateaus after about 20–30 g of high-quality protein per meal.
  • Excess dietary protein beyond what is needed for synthesis is oxidized for energy or converted to fat, not stored as amino acids.
  • Leucine, an essential amino acid, is a key trigger for MPS.
Common misconception

“Eating more protein always builds more muscle.”

Protein is made of amino acids, which are the building blocks of muscle. So it's logical that more building blocks means more muscle.

What is actually true

Muscle protein synthesis has a ceiling: after about 20–30 g of protein (especially with enough leucine), MPS plateaus. Any extra protein is either oxidized for energy or stored as fat. Building muscle also requires a calorie surplus and resistance exercise, not just protein.

Check yourself

Check your understanding of protein turnover and muscle maintenance.

1Multiple choiceChecked instantly

Which of the following best describes what happens to most of the dietary protein you eat in a single meal, assuming you already ate a protein-rich meal a few hours ago?

  • AIt is stored in the amino acid pool for later use.
  • BIt is used to build new muscle protein at the same rate regardless of how much you eat.
  • CIt is broken down into amino acids, some used for protein synthesis, but the excess is oxidized or converted to fat.
  • DIt is all used to replace the 250–300 g of protein that is broken down each day.
2Short answerMarked by AI

A 70 kg adult consumes 100 g of protein in a day. Explain why this does not result in a net gain of 100 g of body protein. Refer to protein turnover and the amino acid pool in your answer.

Graded on References protein turnover and amino acid pool · Explains why net gain is not 100 g · Uses quantitative reasoning (e.g., 250–300 g turnover, 10–15% net use)

3EssayMarked by AI

A friend who lifts weights tells you they eat 200 g of protein per day because 'more protein means more muscle.' Based on what you've learned about protein turnover, MPS, and MPB, evaluate their claim. In your essay, explain the role of the amino acid pool, the ceiling effect of MPS, and what happens to excess dietary protein. Then suggest a more evidence-based approach to protein intake for muscle gain.

Graded on Explains the ceiling effect of MPS · Describes fate of excess dietary protein · Provides evidence-based alternative approach · Clarity and coherence of argument

Lesson 28

Amino acid pools

The body's reservoir of free amino acids derived from diet and tissue breakdown. Essential vs non-essential amino acids. Why protein intake must replenish lost amino acids.

10 min4 assessments

When you eat protein, your body doesn't use every amino acid the moment it arrives. Instead, it keeps a floating reserve — the free amino acid pool. This pool sits in your blood and inside your cells, holding about 100–130 grams of amino acids at any time. Every minute, your cells withdraw from this pool to build new proteins, and they also deposit amino acids back into it when old proteins are broken down. The pool is fed from two sources: the protein you eat (digested and absorbed) and the recycling of your own tissues (protein turnover). If you stop eating protein, the pool quickly shrinks, especially for the essential amino acids — the nine your body cannot make on its own. When the pool lacks just one essential amino acid, your cells cannot finish building any protein that needs that type, so protein synthesis slows or stops. That is why you must replenish the pool regularly through diet.

Reference

Amino acids: classification and dietary need

Histidine

Classification
Essential
Why it matters
Needed for hemoglobin and histamine synthesis

Isoleucine

Classification
Essential
Why it matters
Supports muscle metabolism and energy

Leucine

Classification
Essential
Why it matters
Key trigger for muscle protein synthesis

Lysine

Classification
Essential
Why it matters
Required for collagen and calcium absorption

Methionine

Classification
Essential
Why it matters
Source of sulfur; also gives cysteine

Phenylalanine

Classification
Essential
Why it matters
Precursor for tyrosine, dopamine, and thyroid hormones

Threonine

Classification
Essential
Why it matters
Part of collagen and elastin

Tryptophan

Classification
Essential
Why it matters
Precursor for serotonin and melatonin

Valine

Classification
Essential
Why it matters
Stimulates muscle growth and tissue repair

Arginine

Classification
Conditionally essential
Why it matters
Needed for infants and during illness; otherwise made in kidneys

Alanine

Classification
Non-essential
Why it matters
Synthesized from pyruvate; used in glucose–alanine cycle

Glutamic acid

Classification
Non-essential
Why it matters
Key neurotransmitter and precursor for glutamine

Conditionally essential means the body can usually make enough, but production may fall short during stress, growth, or disease.

Practice
0/8 known
1 / 8

Complementary proteins fill the pool

Suppose you eat 200 g of cooked kidney beans (about 16 g protein, 1.2 g lysine, 0.3 g methionine). After digestion, lysine enters the pool abundantly, but methionine — an essential amino acid — is scarce. The pool has enough lysine but not enough methionine to build most new proteins, so protein synthesis stalls. Now imagine you eat 200 g of cooked rice instead (about 5.4 g protein, 0.2 g lysine, 0.15 g methionine). Now lysine is the limiting amino acid. But if you combine beans and rice in one meal, the pool receives both lysine (1.2 g) and methionine (0.45 g) together. Neither is limiting, so protein synthesis can run at full speed. This is why traditional diets across the world pair legumes with grains — they complement each other's limiting amino acids and keep the pool complete.

  • The free amino acid pool contains all 20 proteinogenic amino acids in blood and cells.
  • Nine amino acids are essential: histidine, isoleucine, leucine, lysine, methionine, phenylalanine, threonine, tryptophan, and valine.
  • Non-essential amino acids can be synthesized from metabolic intermediates, so dietary intake is not strictly needed.
  • If the pool lacks even one essential amino acid, protein synthesis for any protein requiring that acid is limited.
  • Complementary plant proteins (e.g., legumes + grains) can together supply a complete set of essential amino acids.
  • The pool is constantly exchanged: diet and tissue breakdown replenish it; protein synthesis and catabolism drain it.
Check yourself

Check your understanding of the amino acid pool.

1Multiple choiceChecked instantly

Which of the following best describes the amino acid pool?

  • AThe total protein stored in skeletal muscles
  • BThe free amino acids circulating in blood and within cells
  • CThe set of genes that code for amino acid sequences
  • DThe digestive enzymes that break dietary protein into amino acids
2Select all that applyChecked instantly

A person eating only white rice as their protein source will be deficient in which essential amino acid? (Select all that apply.)

  • ALysine
  • BMethionine
  • CTryptophan
  • DLeucine
  • EGlycine
3Select all that applyChecked instantly

Which of the following are essential amino acids? (Select all that apply.)

  • AHistidine
  • BAlanine
  • CLeucine
  • DSerine
  • ETryptophan
4Fill the blanksChecked instantly

Lesson 29

Muscle protein synthesis

Process of building new muscle proteins using amino acids. Stimulated by feeding (especially leucine), resistance exercise, and growth factors. MPS vs MPB balance determines net muscle gain or loss.

15 min3 assessments

Your muscles are not static. Every day, your body breaks down old or damaged muscle proteins and builds new ones to replace them. The building side is called muscle protein synthesis (MPS). The breaking-down side is muscle protein breakdown (MPB). The difference between the two — net balance — decides whether a muscle grows, shrinks, or stays the same.

MPS is not automatic. It needs two signals working together:

  1. 1.Amino acid availability — especially the amino acid leucine, which acts as a trigger. When you eat protein, blood leucine rises, and that rise tells your cells to start building.
  2. 2.Mechanical tension — from resistance exercise. Lifting a weight or doing bodyweight squats stretches and loads muscle fibres, which activates a pathway (mTOR) that ramps up MPS for the next 24–48 hours.

Without leucine, the exercise signal fades without much building. Without exercise, the leucine signal produces a small, short-lived MPS bump. Together, they multiply the effect far beyond either alone.

MPS peaks about 1–2 hours after a meal and stays elevated for a few hours, then drops back to baseline. That is why protein timing matters less than total daily intake — but also why spacing protein across meals (rather than eating it all at dinner) keeps MPS elevated more of the day.

The two triggers for MPS — exercise and leucine — converge on the same pathway. Net muscle change is the difference between synthesis and breakdown.

Analogy

Think of your muscle as a brick wall. Every day, a few bricks crumble (MPB). To keep the wall standing, you need to add new bricks (MPS).

  • Eating protein is like delivering bricks to the site. Leucine is the foreman who shouts "start laying!" — without him, the bricks just sit in a pile.
  • Resistance exercise is like the architect drawing up plans and clearing space. It tells the crew where to build and makes room for new bricks.
  • If you deliver bricks but no plans, you get a small, messy patch. If you have plans but no bricks, nothing gets built. Together, you get a solid new section of wall.

Where the analogy breaks down

A wall does not decide to tear itself down faster when you lift heavy things. In muscle, intense exercise temporarily raises MPB alongside MPS — the wall gets a little more crumbly before it gets stronger. The analogy hides that brief breakdown spike.

Common misconception

“Eating more protein automatically builds more muscle.”

Protein is the raw material for muscle, so more raw material should mean more building. Food labels and supplement ads reinforce the idea that extra protein equals extra muscle.

What is actually true

MPS has a ceiling. Once leucine and other amino acids saturate the signal (roughly 20–40 g of high-quality protein per meal), additional protein does not raise MPS further — the excess is oxidised for energy or stored as fat. The real lever is combining protein with resistance exercise, which raises the ceiling temporarily.

Check yourself

Check your understanding of MPS.

1Short answerMarked by AI

Explain in 2–4 sentences why eating 80 g of protein in one meal does not double the muscle-building effect of eating 40 g. Name the specific amino acid that limits the response.

Graded on Identifies the limiting factor (leucine saturation) and the consequence · Connects the limit to real-world protein dosing · Clarity and specificity

2Multiple choiceChecked instantly

A person eats a protein-rich meal but has not exercised in a week. Compared to someone who both eats the same meal and just finished a resistance workout, what happens to their MPS response?

  • AMPS is identical because the meal alone provides all the signal needed.
  • BMPS is lower and returns to baseline sooner because the exercise signal that amplifies mTOR activation is absent.
  • CMPS is higher because the body is resting and can divert more energy to building.
  • DMPS is zero because muscle building only happens after exercise.
3Short answerMarked by AI

Which of the following best describes the role of leucine in muscle protein synthesis?

Go deeper

Read these for the long-term outcomes of MPS and MPB balance: muscle growth (hypertrophy) and muscle loss (atrophy).

Lesson 30

Muscle protein breakdown

Process of breaking down muscle proteins to release amino acids for energy or other tissues. Increases in fasting, illness, and inactivity. Inhibited by insulin and feeding.

10 min3 assessments

Your body is always tearing down old muscle proteins and building new ones. That tearing-down half is muscle protein breakdown (MPB). It sounds destructive, but it's how your body recycles amino acids—the building blocks of protein—to use elsewhere when you're not eating, or to remove damaged proteins so new ones can replace them.

MPB rises when insulin is low (fasting, between meals), when stress hormones like cortisol are high (illness, injury), or when your muscles are doing little (bed rest, sitting all day). It falls when you eat protein or carbs, because insulin signals your cells to stop the breakdown and start building again.

Without this process, you'd have no way to free amino acids for energy during a long gap between meals, or to repair a muscle fibre after a workout. The problem isn't MPB itself—it's when it outruns muscle protein synthesis (MPS) for too long, and you lose more muscle than you rebuild.

Signals that push MPB up or down. MPB and MPS compete for the same amino acid pool.

Analogy

Think of your muscle proteins as the bricks of a house. Normally the house is well-maintained: you replace worn bricks (synthesis) and remove cracked ones (breakdown). When you run out of food (fasting), you borrow bricks from the garage wall to patch the main house's roof, because keeping the roof intact is more urgent. That borrowing is muscle protein breakdown—redirecting amino acids to vital organs or energy.

The problem comes when you borrow bricks every day without replacing them. The garage wall thins, then collapses, and you lose strength and function.

Where the analogy breaks down

Muscle protein breakdown isn't always about 'borrowing'—it also removes damaged proteins that would otherwise clog the cell and cause harm. And unlike a house, your body can temporarily burn amino acids for energy, which no brick wall can do.

Common misconception

“"Muscle protein breakdown only happens when you're starving or sick."”

We only notice muscle loss during illness or fasting, so it seems like MPB is turned off the rest of the time.

What is actually true

MPB happens constantly, even when you're healthy and well-fed. It's part of normal turnover—old proteins get replaced every few days. What changes is the balance: in health, synthesis matches breakdown; during stress, breakdown exceeds it.

Decide

You're a dietitian explaining muscle protein changes to a client. Match each situation with what happens to MPB and whether net muscle loss occurs. The client asks: 'Why does my muscle waste away when I'm sick, but not when I skip breakfast?'

What happens to MPB and net muscle balance during a 16-hour overnight fast?

Check yourself

Check your understanding of muscle protein breakdown.

1Multiple choiceChecked instantly

Which of the following conditions reliably DECREASES muscle protein breakdown?

  • AFasting for 12 hours
  • BA high-cortisol state from illness
  • CAn insulin spike after a protein-containing meal
  • DA long period of bed rest
2Short answerMarked by AI

Explain in 2-3 sentences why muscle protein breakdown is not automatically harmful, and give one situation where it becomes harmful.

Graded on Identifies the normal role of MPB · Describes a harmful condition where breakdown exceeds synthesis · Clarity and conciseness

3Short answerMarked by AI

A friend says, 'I'm skipping breakfast to lose weight; isn't that good for my muscles since I'm giving them a break?' Identify the flaw in their reasoning based on what you know about muscle protein breakdown and the effect of fasting.

Graded on Recognises that fasting increases MPB · Explains the consequence of repeated fasting on muscle mass · Addresses the friend's reasoning directly

Go deeper

For deeper reading on clinical muscle wasting, this Wikipedia article covers causes and mechanisms.

Lesson 31

Complete vs incomplete proteins

Distinction based on amino acid profile. Animal sources typically complete, plant sources often deficient in one or more essential amino acids. Complementary proteins concept.

10 min3 assessments

You already know that protein is broken down into amino acids and used to repair tissues. But here's the catch: your body can make some amino acids on its own, while nine of them — called essential amino acids — must come from food. A protein source that contains all nine in the right amounts is called complete. One that is missing or low in any of them is incomplete.

If you eat only incomplete proteins, your body cannot build new protein at full speed. That's why the concept of complementary proteins exists: combining two incomplete plant foods that together cover all nine essential amino acids. This is critical for anyone who eats little or no animal products.

Not all protein sources deliver the same amino acid mix. The table below shows which ones give you all nine essential amino acids and when you need to combine foods.

Animal sources

Amino acid profile
Contains all nine essential amino acids in adequate amounts
Completeness
Complete
Typical examples
Meat, poultry, fish, eggs, dairy
Best for
Building muscle or recovering from injury — one serving provides all you need

Plant sources

Amino acid profile
Often low in one or more essential amino acids (e.g., lysine in grains, methionine in legumes)
Completeness
Incomplete
Typical examples
Beans, lentils, nuts, seeds, grains, vegetables
Best for
General health, fibre, and lower saturated fat — but must be combined to cover all amino acids

Complementary combinations

Amino acid profile
Two or more incomplete plant sources that together supply all nine essential amino acids
Completeness
Complete when combined
Typical examples
Rice + beans, hummus + pita, peanut butter + whole wheat bread
Best for
Vegan or vegetarian diets — achieves completeness without animal products

Rice and beans: a classic complementary pair

What you eat: 1 cup of cooked brown rice (about 5 g protein) and 1 cup of cooked black beans (about 15 g protein).

Why it works: Rice is low in lysine but adequate in methionine. Beans are low in methionine but rich in lysine. Together they provide all nine essential amino acids in amounts your body can use.

What happens if you eat only rice: Your body cannot build new protein because lysine is missing. The other amino acids are deaminated and used for energy or stored as fat.

What happens if you eat only beans: Methionine is limiting, so protein synthesis slows.

Result: The combination acts like a complete protein — similar to eating a piece of chicken.

Common misconception

“You have to eat complementary proteins at every meal, or your body won't get the amino acids it needs.”

If a single meal is incomplete, it seems logical that you'd miss out. Nutrition labels and diet advice often emphasise 'complete' sources.

What is actually true

Your body pools amino acids from meals eaten over the day. As long as you eat a variety of protein sources across the day, your liver and muscle cells can mix and match. The complementary meal is a useful concept, but not a per-meal requirement.

  • A complete protein contains all nine essential amino acids in sufficient amounts.
  • Animal proteins are complete; most plant proteins are incomplete because they lack one or more essential amino acids.
  • Complementary proteins are two or more plant foods that together provide all essential amino acids.
  • You do not need to combine complementary proteins at the same meal — your body's amino acid pool works over the whole day.
  • Soy and quinoa are exceptions: they are plant-based complete proteins.
Check yourself

Check your understanding of complete and incomplete proteins.

1Multiple choiceChecked instantly

Which of the following statements about complementary proteins is correct?

  • AComplementary proteins must be eaten at the same meal to be effective.
  • BComplementary proteins combine two or more incomplete plant sources to provide all essential amino acids.
  • CAll plant proteins are incomplete and cannot be combined to form a complete protein.
  • DComplementary proteins are only needed by athletes.
2Select all that applyChecked instantly

Select all of the following that are complete protein sources (or combinations that provide a complete amino acid profile). Choose 2 or 3.

  • AA chicken breast
  • BA bowl of rice alone
  • CHummus and whole wheat pita
  • DA handful of almonds
  • EA glass of milk
3Short answerMarked by AI

A friend says they are going vegan but are worried they won't get enough protein. They plan to eat only oatmeal for breakfast, a peanut butter sandwich on white bread for lunch, and a lentil soup for dinner. Evaluate this day's meals for protein completeness. What adjustments would you recommend, and why?

Graded on Identifies which meals are incomplete and why · Suggests specific adjustments to achieve completeness · Explains the concept of the amino acid pool

Lesson 32

Vitamins: the cofactors your body cannot make

You will be able to distinguish fat-soluble from water-soluble vitamins and name a key function and deficiency symptom for each. Covers vitamins A, D, E, K, C, and the B-complex. Prevents the assumption that a multivitamin fixes a poor diet.

40 min4 assessments

Vitamins are organic compounds your body needs in small amounts but cannot synthesize in sufficient quantities — you must get them from food. They act as cofactors, helping enzymes carry out chemical reactions: building proteins, repairing DNA, producing energy, and maintaining vision. Vitamins fall into two groups based on how they move through your body.

Fat-soluble vitamins (A, D, E, K) dissolve in fat and are stored in your liver and fatty tissues. You don’t need them every day, but they can build up to toxic levels if you overconsume them. Water-soluble vitamins (the B-complex and vitamin C) dissolve in water and are not stored in significant amounts — excess is excreted in urine, so you need them regularly.

This fundamental difference dictates how you get them, how often you need them, and what happens when you run low. A single vitamin deficiency can cause a specific disease (e.g., scurvy from lack of vitamin C, rickets from lack of vitamin D). The best way to get all vitamins is a balanced diet with a variety of whole foods; supplements are not a substitute for poor eating habits.

Practice
0/8 known
1 / 8
Reference

Vitamin Quick Reference: Functions, Deficiency, and Sources

A (retinol)

Solubility
Fat-soluble
Major Functions
Vision, immune function, skin integrity
Deficiency Symptoms
Night blindness, dry skin, impaired immunity
Key Food Sources
Liver, carrots, sweet potatoes, spinach

D (calciferol)

Solubility
Fat-soluble
Major Functions
Calcium absorption, bone mineralization
Deficiency Symptoms
Rickets, osteomalacia, bone pain
Key Food Sources
Sunlight, fatty fish, fortified milk

E (tocopherol)

Solubility
Fat-soluble
Major Functions
Antioxidant, protects cell membranes
Deficiency Symptoms
Rare; nerve damage, hemolytic anemia
Key Food Sources
Nuts, seeds, vegetable oils, spinach

K (phylloquinone)

Solubility
Fat-soluble
Major Functions
Blood clotting, bone metabolism
Deficiency Symptoms
Bleeding, easy bruising
Key Food Sources
Green leafy vegetables, broccoli, soybeans

C (ascorbic acid)

Solubility
Water-soluble
Major Functions
Collagen synthesis, antioxidant, boosts iron absorption
Deficiency Symptoms
Scurvy: gum bleeding, fatigue, poor wound healing
Key Food Sources
Citrus fruits, strawberries, bell peppers, broccoli

B1 (thiamine)

Solubility
Water-soluble
Major Functions
Carbohydrate metabolism, nerve function
Deficiency Symptoms
Beriberi: weakness, nerve damage, cardiovascular issues
Key Food Sources
Whole grains, pork, legumes, nuts

B2 (riboflavin)

Solubility
Water-soluble
Major Functions
Energy production, skin health
Deficiency Symptoms
Ariboflavinosis: sore throat, cracks at mouth corners, dermatitis
Key Food Sources
Dairy, eggs, green vegetables, almonds

B3 (niacin)

Solubility
Water-soluble
Major Functions
Energy metabolism, DNA repair
Deficiency Symptoms
Pellagra: dermatitis, diarrhea, dementia
Key Food Sources
Chicken, tuna, peanuts, whole grains

B5 (pantothenic acid)

Solubility
Water-soluble
Major Functions
Synthesis of coenzyme A, fatty acid metabolism
Deficiency Symptoms
Rare; fatigue, numbness, burning feet
Key Food Sources
Avocado, yogurt, chicken, potatoes

B6 (pyridoxine)

Solubility
Water-soluble
Major Functions
Amino acid metabolism, neurotransmitter synthesis
Deficiency Symptoms
Anemia, dermatitis, depression, confusion
Key Food Sources
Chickpeas, poultry, bananas, potatoes

B7 (biotin)

Solubility
Water-soluble
Major Functions
Fatty acid synthesis, glucose metabolism
Deficiency Symptoms
Rare; hair thinning, rash, neurological symptoms
Key Food Sources
Eggs, nuts, seeds, sweet potatoes

B9 (folate)

Solubility
Water-soluble
Major Functions
DNA synthesis, red blood cell formation
Deficiency Symptoms
Megaloblastic anemia, neural tube defects in pregnancy
Key Food Sources
Leafy greens, legumes, asparagus, fortified grains

B12 (cobalamin)

Solubility
Water-soluble
Major Functions
Nerve function, red blood cell formation, DNA synthesis
Deficiency Symptoms
Pernicious anemia, neurological symptoms, fatigue
Key Food Sources
Meat, fish, dairy, eggs; not in plants

Fat-soluble vitamins are stored in the liver and adipose tissue; water-soluble vitamins need regular intake. Many B vitamins are also coenzymes in energy metabolism.

  • Vitamins are organic cofactors that enable enzyme reactions; your body cannot make them in sufficient amounts.
  • Fat-soluble vitamins (A, D, E, K) are stored in tissues and can accumulate to toxic levels if overconsumed.
  • Water-soluble vitamins (B-complex and C) are not stored and must be consumed regularly; excess is excreted in urine.
  • Each vitamin has a specific primary function and a well-defined deficiency syndrome (e.g., scurvy from lack of vitamin C, rickets from lack of vitamin D).
  • A balanced diet with a variety of whole foods provides all essential vitamins; supplements are not a substitute for a poor diet.
  • Cooking methods (e.g., boiling) can reduce water-soluble vitamin content; steaming and microwaving better preserve them.
Check yourself

Test your knowledge with these questions.

1Multiple choiceChecked instantly

Which of the following is a fat-soluble vitamin?

  • AVitamin C
  • BVitamin B12
  • CVitamin D
  • DVitamin B6
2Fill the blanksChecked instantly
3Select all that applyChecked instantly

Select all vitamins that are water-soluble. (Select all that apply.)

  • AVitamin A
  • BVitamin C
  • CVitamin K
  • DFolate (B9)
  • EVitamin E
  • FVitamin B12
4Short answerMarked by AI

A friend tells you they take a daily multivitamin to 'cover their bases' and then eat mostly fast food. Based on what you learned about vitamins, explain why this approach is flawed. In your answer, mention the difference between fat-soluble and water-soluble vitamins and why a multivitamin cannot replace a healthy diet.

Graded on Identifies the limitation of multivitamins as a substitute for a healthy diet · Distinguishes fat-soluble and water-soluble vitamins and explains storage implications · Provides a concrete example or implication

Lesson 33

Fat-soluble vitamins

Covers vitamins A, D, E, K: storage in body, functions, deficiency risks, and toxicity from megadosing.

15 min3 assessments

Fat-soluble vitamins—A, D, E, and K—are stored in your body's fatty tissues and liver. Unlike water-soluble vitamins, they do not need to be consumed every day; reserves can last weeks or months. But that storage also means they can build up to toxic levels if you take high-dose supplements without a medical reason.

Each of the four has a distinct job:

  • Vitamin A (retinoids, beta-carotene) supports vision, immune function, and skin health. Deficiency causes night blindness; toxicity leads to liver damage and birth defects.
  • Vitamin D (calciferol) regulates calcium absorption and bone health. Deficiency results in rickets (children) or osteomalacia (adults); toxicity (rare from sun) causes hypercalcemia and kidney damage.
  • Vitamin E (tocopherols) acts as an antioxidant, protecting cell membranes. Deficiency is very rare but can cause nerve damage; toxicity is uncommon but may interfere with blood clotting.
  • Vitamin K (phylloquinone, menaquinones) is essential for blood clotting proteins and bone metabolism. Deficiency leads to bleeding disorders; toxicity is almost unknown from food, but synthetic forms can interfere with anticoagulants.
Reference

Fat-Soluble Vitamins at a Glance

A (retinol/carotenoids)

Key Functions
Vision, immune function, skin integrity
Food Sources
Liver, fish oils, eggs, orange/red vegetables, dark leafy greens
Deficiency Signs
Night blindness, dry skin, increased infections
Toxicity Concerns
Liver damage, birth defects, bone pain (hypervitaminosis A)

D (calciferol)

Key Functions
Calcium absorption, bone health, immune modulation
Food Sources
Sunlight exposure, fatty fish, fortified milk, egg yolk
Deficiency Signs
Rickets (children), osteomalacia (adults), muscle weakness
Toxicity Concerns
Hypercalcemia, kidney damage, nausea (rare from sun)

E (tocopherols)

Key Functions
Antioxidant, protects cell membranes, immune function
Food Sources
Nuts, seeds, vegetable oils, spinach, broccoli
Deficiency Signs
Hemolytic anemia (premature infants), nerve damage
Toxicity Concerns
May increase bleeding risk (especially with anticoagulants)

K (phylloquinone/menaquinones)

Key Functions
Blood clotting (activation of clotting factors), bone metabolism
Food Sources
Dark leafy greens (kale, spinach), broccoli, fermented foods (natto)
Deficiency Signs
Easy bruising, bleeding (nose, gums, heavy periods)
Toxicity Concerns
Synthetic K3 can cause toxicity; natural forms safe

RDA values vary by age, sex, and life stage. Toxicity from food alone is extremely rare; supplements are the main risk.

Practice
0/8 known
1 / 8
Check yourself

Check your understanding of fat-soluble vitamins.

1Select all that applyChecked instantly

Which of the following are fat-soluble vitamins? (Select all that apply.)

  • AVitamin A
  • BVitamin C
  • CVitamin D
  • DVitamin B12
  • EVitamin E
  • FVitamin K
2Multiple choiceChecked instantly

A patient has been taking a high-dose vitamin A supplement (10,000 IU daily) for several months without medical supervision. She now reports headaches, blurred vision, and joint pain. Which vitamin toxicity is most likely responsible?

  • AVitamin D toxicity
  • BVitamin A toxicity
  • CVitamin E toxicity
  • DVitamin K toxicity
3Fill the blanksChecked instantly
  • Fat-soluble vitamins (A, D, E, K) are stored in body fat and liver, allowing longer reserves but also posing toxicity risk with excessive supplement intake.
  • Vitamin A supports vision and immunity; early deficiency sign is night blindness.
  • Vitamin D is synthesized in the skin from sunlight and is crucial for calcium absorption and bone health.
  • Vitamin E is a membrane antioxidant; deficiency is rare but can cause nerve damage.
  • Vitamin K is necessary for blood clotting factor activation; leafy greens are a primary source.
  • Toxicity from food sources alone is extremely unlikely; supplements and high-dose synthetic forms carry the most risk.

Lesson 34

Water-soluble vitamins

Covers B-complex and vitamin C: daily requirements, cooking losses, deficiency signs, and food sources.

15 min4 assessments

Water-soluble vitamins — the B-complex (eight of them) and vitamin C — share a critical property: your body doesn't store them in any significant amount. Unlike fat-soluble vitamins (A, D, E, K) that hide in your liver and fat tissue, water-soluble vitamins circulate in your blood and are excreted in urine when levels get high. That means you need a fresh supply every day.

Cooking also takes a toll. These vitamins dissolve in water and are sensitive to heat, light, and air. Boiling vegetables can flush away up to 50% of the vitamin C and thiamin (B1) into the cooking water. Steaming, microwaving, or stir-frying with minimal water preserves more.

The B-complex acts as a team of coenzymes — they help your body extract energy from food, build red blood cells, and maintain your nervous system. Vitamin C is the antioxidant and collagen builder, essential for wound healing and immune function.

Deficiencies show up quickly because stores are low. Scurvy (vitamin C deficiency) is rare today but still appears in people who eat almost no fruits or vegetables. Beriberi (thiamin deficiency) was common when polished rice was the only staple. Pellagra (niacin deficiency) is linked to diets heavy in corn that isn't nixtamalized. Knowing these names helps you spot the pattern: each vitamin has a specific job, and when it's missing, a specific symptom emerges.

Reference

Water-Soluble Vitamins at a Glance

B1 (Thiamin)

Key Functions
Energy metabolism, nerve function
RDA (Adult)
1.1–1.2 mg
Rich Food Sources
Pork, whole grains, legumes, sunflower seeds
Deficiency Signs
Beriberi (numbness, confusion, heart failure)
Cooking Loss Susceptibility
High – boiling strips 50%

B2 (Riboflavin)

Key Functions
Energy metabolism, skin health
RDA (Adult)
1.1–1.3 mg
Rich Food Sources
Milk, eggs, almonds, mushrooms
Deficiency Signs
Angular stomatitis, sore throat
Cooking Loss Susceptibility
Moderate – light sensitive

B3 (Niacin)

Key Functions
Energy metabolism, DNA repair
RDA (Adult)
14–16 mg NE
Rich Food Sources
Meat, poultry, fish, peanuts, fortified grains
Deficiency Signs
Pellagra (dermatitis, diarrhea, dementia)
Cooking Loss Susceptibility
Low – heat stable

B5 (Pantothenic acid)

Key Functions
Coenzyme A synthesis
RDA (Adult)
5 mg (AI)
Rich Food Sources
Avocado, yogurt, eggs, chicken
Deficiency Signs
Rare, but fatigue, numbness
Cooking Loss Susceptibility
Moderate – mild heat loss

B6 (Pyridoxine)

Key Functions
Amino acid metabolism, hemoglobin synthesis
RDA (Adult)
1.3–2.0 mg
Rich Food Sources
Chicken, fish, potatoes, bananas, chickpeas
Deficiency Signs
Anemia, dermatitis, confusion
Cooking Loss Susceptibility
Moderate – heat & light sensitive

B7 (Biotin)

Key Functions
Fat, carbohydrate, protein metabolism
RDA (Adult)
30 µg (AI)
Rich Food Sources
Eggs (cooked), nuts, sweet potatoes
Deficiency Signs
Hair loss, scaly rash, depression
Cooking Loss Susceptibility
Low – heat stable enough

B9 (Folate)

Key Functions
DNA synthesis, cell division
RDA (Adult)
400 µg DFE
Rich Food Sources
Leafy greens, legumes, asparagus, fortified grains
Deficiency Signs
Megaloblastic anemia, neural tube defects
Cooking Loss Susceptibility
High – heat, light, oxygen

B12 (Cobalamin)

Key Functions
Nerve function, red blood cell formation
RDA (Adult)
2.4 µg
Rich Food Sources
Meat, fish, dairy, eggs, fortified foods
Deficiency Signs
Pernicious anemia, neuropathy
Cooking Loss Susceptibility
Low – heat stable

C (Ascorbic acid)

Key Functions
Antioxidant, collagen synthesis, iron absorption
RDA (Adult)
75–90 mg (smokers +35 mg)
Rich Food Sources
Citrus, bell peppers, strawberries, broccoli, kiwi
Deficiency Signs
Scurvy (bleeding gums, poor wound healing, fatigue)
Cooking Loss Susceptibility
Very high – heat, light, oxygen, water

RDA = Recommended Dietary Allowance; AI = Adequate Intake; DFE = Dietary Folate Equivalents; NE = Niacin Equivalents. Values are for adults 19–50 years.

Practice
0/8 known
1 / 8
  • Water-soluble vitamins (B-complex and C) are not stored; daily intake is required.
  • Cooking losses are significant: boiling can remove up to 50% of vitamin C and thiamin; steaming preserves more.
  • B-complex vitamins act as coenzymes in energy metabolism, red blood cell production, and nerve function.
  • Vitamin C is essential for collagen synthesis, antioxidant protection, and iron absorption.
  • Deficiency symptoms are specific: beriberi (B1), pellagra (B3), scurvy (C), pernicious anemia (B12), neural tube defects (B9).

A Day's Worth of Water-Soluble Vitamins: Sample Meal Plan

This meal plan provides a generous spread of water-soluble vitamins. Approximate contributions to adult RDAs are noted.

Breakfast

  • 1 cup fortified oatmeal (B1: 50% DV, B2: 25%, B3: 20%, B9: 30%)
  • 1 cup orange juice (C: 100% DV)

Lunch

  • Grilled chicken breast (3 oz) (B3: 60% DV, B6: 30%, B12: 20%)
  • Spinach salad with bell peppers (C: 80% DV, B9: 40%, B2: 15%)

Snack

  • 1 cup plain yogurt (B2: 30% DV, B12: 25%)
  • 1 oz almonds (B2: 15% DV)

Dinner

  • Salmon (3 oz) (B6: 40% DV, B12: 100%, B3: 50%)
  • Sweet potato (medium) (C: 30% DV, B6: 20%)
  • Steamed broccoli (1 cup) (C: 100% DV, B9: 20%, B2: 15%)

Note: DV = Daily Value on nutrition labels. Actual RDA varies by age and gender. This plan meets or exceeds the RDA for C, B1, B3, B6, B12, and B9, and provides substantial amounts of B2 and B5.

Check yourself

Check your understanding of water-soluble vitamins.

1Multiple choiceChecked instantly

Which water-soluble vitamin is most sensitive to heat and light, and is easily lost during boiling?

  • ANiacin (B3)
  • BRiboflavin (B2)
  • CVitamin C (ascorbic acid)
  • DBiotin (B7)
2Select all that applyChecked instantly

Which of the following are B-complex vitamins? (Select all that apply.)

  • AThiamin
  • BAscorbic acid
  • CRiboflavin
  • DRetinol
  • EFolate
  • FCalciferol
3Fill the blanksChecked instantly
4Fill the blanksChecked instantly

Lesson 35

Deficiency and toxicity

Recognizing common vitamin deficiency symptoms and risks of excessive intake, especially fat-soluble vitamins.

10 min4 assessments
Decide

You're a dietitian consulting with a 45-year-old patient who complains of chronic fatigue, muscle weakness, and bone pain in her legs. She also mentions that she bruises easily and her gums bleed when she brushes. She has a history of weight-loss surgery two years ago and takes no supplements. Which step do you take first?

What should you check first?

Decision tree for diagnosing vitamin deficiencies from common symptoms

Common misconception

“If a little bit of a vitamin is good, a lot must be better.”

Many vitamins have no obvious side effects in moderate excess, and supplement marketing often implies that higher doses are more effective. Anecdotes about 'megadosing' curing colds or boosting energy reinforce this.

What is actually true

Fat-soluble vitamins (A, D, E, K) accumulate in body tissues and can reach toxic levels (hypervitaminosis). For example, too much vitamin A causes liver damage, bone pain, and intracranial pressure. Excess vitamin D leads to hypercalcemia and kidney stones. Even some water-soluble vitamins like B6 can be toxic in very high doses. The therapeutic window is real.

Vitamin A toxicity from supplementation

Case: A 35-year-old man takes 50,000 IU of vitamin A daily for six months (10x the RDA) to improve his skin. He develops headache, nausea, blurred vision, and joint pain. Blood tests show serum retinol > 1.0 µg/mL (normal 0.3–0.7). Liver enzymes are elevated.

Diagnosis: Chronic hypervitaminosis A.

Mechanism: Vitamin A is stored in the liver. Excess accumulates in hepatocytes and stellate cells, causing fibrosis over time. The early symptoms (headache, nausea) are from increased intracranial pressure.

Treatment: Stop supplementation; symptoms resolve over weeks. Liver enzymes may take months to normalize.

Key point: Fat-soluble vitamins have no rapid excretion route. Toxicity is a real risk with high-dose supplements.

Check yourself

Check your understanding of vitamin deficiency and toxicity.

1Select all that applyChecked instantly

Which of the following are symptoms of vitamin K deficiency? Select all that apply.

  • AEasy bruising
  • BProlonged bleeding from cuts
  • CNight blindness
  • DBone pain
  • EGum bleeding
  • FDiarrhea
2Put in orderChecked instantly

Arrange the steps for diagnosing a suspected fat-soluble vitamin deficiency in chronological order from first action to final diagnosis.

  • ACheck serum levels of vitamins A, D, E, K
  • BIdentify patient symptoms (fatigue, bruising, bone pain)
  • CAssess dietary fat intake and malabsorption risk
  • DReview supplement use and medication history
  • EDiagnose specific deficiencies based on lab results and symptoms
3Short answerMarked by AI

Explain why fat-soluble vitamins are more likely than water-soluble vitamins to cause toxicity if taken in excess. Provide one specific example of a toxicity symptom for a named fat-soluble vitamin.

Graded on Distinguishes storage vs excretion of fat- vs water-soluble vitamins · Gives a correct specific example of a fat-soluble vitamin toxicity symptom

4Short answerMarked by AI

A 60-year-old woman on warfarin (a blood thinner) has been eating large amounts of kale and spinach daily. Her INR (blood clotting time) has dropped dangerously low. Explain which vitamin is involved, how it interacts with warfarin, and what she should do.

Graded on Identifies vitamin K and explains its role in clotting · Explains warfarin-vitamin K interaction · Advises appropriate action

Lesson 36

Bioavailability and sources

How cooking, food pairing, and processing affect vitamin absorption; best dietary sources for each vitamin.

10 min3 assessments

Next to the cereal box stands its label: "100% vitamin C." That is a claim about what is in the box, not what is in you. The fraction of a nutrient that crosses from food into your bloodstream, in a form your body can use, is its bioavailability — and it is rarely 100%.

Two rules sort most of the cases. Solubility. Fat-soluble vitamins (A, D, E, K) ride dietary fat into the gut, so a fat-free meal leaves most of them unabsorbed; they are also stored, so they do not need daily refills. Water-soluble vitamins (C and the B-complex) dissolve in water, are lost in urine when in excess, and are fragile — heat, light, air and boiling water destroy or carry them away. Form. Some foods hold the vitamin ready to use (retinol in liver and dairy); plants usually hold a provitamin that must be converted. 12 µg of beta-carotene becomes about 1 µg of retinol, which is why targets use "retinol activity equivalents" (RAE).

Preparation decides the rest. Cooking breaks plant cell walls and releases trapped provitamins; frozen vegetables, frozen at peak, can hold more vitamin C than "fresh" produce that aged in a warehouse. The skill isn't eating vitamins — it's getting them from plate to bloodstream, in that order.

  • Fat-soluble vitamins (A, D, E, K) are absorbed with dietary fat and stored; the fat has to be in the same meal, not just in your diet.
  • Water-soluble vitamins (C and B-complex) dissolve in water, leach into cooking liquid, and are excreted in urine when in excess — they need a frequent supply.
  • Provitamins must be converted: 12 µg of beta-carotene from food counts as 1 µg RAE, while preformed retinol counts 1:1.
  • Heat and cutting raise beta-carotene absorption by breaking plant cell walls: raw carrots deliver roughly 3–5% of their beta-carotene; cooked with oil, roughly 15–20%.
  • Milling strips B vitamins from grain; "enriched" on the label means they were added back.
  • Folic acid in fortified foods is absorbed roughly twice as well as natural food folate, which is why it has a 1,000 µg/day upper limit.
Steps
0/7

Run this sequence in order — each step sets up the next, and skipping ahead reproduces the classic failures: the fat-free kale salad, the overboiled greens, the carrot-a-day vitamin A plan that never adds up.

  1. Classify the vitamin

    Name the vitamin and decide its class: A, D, E, K ride with fat; C and the B-complex ride with water. Every rule below follows from this one call.

    Guess the class and the whole plan is wrong — fat never rescues vitamin C, and water never moves vitamin K.

    You can state the class from memory.

  2. Identify the form

    Preformed vitamins are already active — retinol in liver, dairy, and eggs. Provitamins need conversion — beta-carotene in orange and dark-green plants becomes retinol, and niacin in corn is bound so tightly that alkaline treatment (nixtamalization) is needed to free it.

    Counting a provitamin as if it were preformed overestimates your intake by an order of magnitude.

    You know whether your source is active or needs conversion.

  3. Choose the preparation

    For provitamin A and for D, E, K: chop and apply heat — it softens the plant cell walls that trap the pigment, and the fat comes in the next step. For C and B1/B9: keep heat short and water contact minimal — steam, stir-fry, or eat raw.

    Overcooking leaves the food looking fine while the water-soluble vitamins have leached out or been destroyed.

    The cooking method matches the vitamin class.

  4. Add the accomplice in the same meal

    5–10 g of fat — a teaspoon of oil, an egg, a handful of nuts — carries the fat-soluble vitamins across the gut. One cross-pairing (not a vitamin, but the classic): vitamin C multiplies non-heme iron absorption, so squeeze lemon over lentils.

    Fat at the next meal doesn't help — absorption happens in the same passage through the gut.

    Every fat-soluble source shares a plate with a fat source.

  5. Account for processing and storage

    Milling strips most B vitamins from grain — pick "whole grain" or "enriched" (enriched flour has B1, B2, B3, iron, and folic acid added back). Frozen vegetables, frozen soon after picking, often keep more vitamin C than "fresh" produce that sat in a warehouse.

    "Fresh" on the label is not a bioavailability claim — age, light, and reheating keep destroying C and folate.

    You can say which process removed a vitamin and which one put it back.

  6. Apply the same rules to supplements

    A, D, E, K pills need a meal with fat; on an empty stomach most of the dose is wasted. Folic acid in fortified food or a pill is absorbed roughly twice as well as natural food folate, so the 1,000 µg/day upper limit can be reached fast.

    A fat-soluble pill swallowed with coffee instead of food quietly fails — and since nothing seems to happen, people take more.

    You take fat-soluble supplements with food, and your folic acid stays at or under 1,000 µg/day.

  7. Estimate what actually lands

    Convert to RAE, apply a realistic absorption fraction, then compare with the target. 100 g raw carrot: 8.3 mg beta-carotene × 4% absorption ÷ 12 ≈ 28 µg RAE. The same carrot cooked in oil at ~20% absorption ≈ 138 µg RAE. Target: 700–900 µg RAE/day.

    Defaulting to the label's numbers overestimates several-fold: labels count the vitamin in the food, not the vitamin in you.

    Your estimate is a number — and it's smaller than the label's number.

Same carrot, five times the vitamin A

You want a reliable vitamin A source that isn't liver. A 100 g carrot carries about 8.3 mg of beta-carotene, and the food label has already converted that to RAE. What the label can't show is absorption — the part you control. Run the numbers for two ways of eating it.

Raw, as sticks, no fat — about 4% absorption:

  • 8,300 µg × 0.04 = 332 µg beta-carotene absorbed
  • 332 ÷ 12 = 27.7 µg RAE

Cooked and tossed with 1 teaspoon of oil — about 20% absorption:

  • 8,300 µg × 0.20 = 1,660 µg beta-carotene absorbed
  • 1,660 ÷ 12 = 138.3 µg RAE

Against a 700–900 µg RAE daily target, the raw sticks deliver under 4% of the day's need; the cooked carrot with oil delivers about 17%. Same food, same label, five times the delivery — preparation changed bioavailability. The lesson isn't "carrots are useless"; it's that a vitamin source only counts once it's cooked, chopped, and paired with fat.

Checklist
0/8

While you plan one day's meals

Tick an item only when you can point at the plate you're actually eating, not the one you intended.

Check yourself

Practice the walkthrough's order and arithmetic before you rely on it.

1Put in orderChecked instantly

You are planning a sweet-potato meal to get real vitamin A from beta-carotene. Arrange the steps in the order you would run them, following the walkthrough.

  • AIdentify the form: sweet potato holds beta-carotene, a provitamin.
  • BEstimate the RAE that actually reaches you, not the label's claim.
  • CClassify the vitamin: A is fat-soluble.
  • DCook or mash the sweet potato to break its cell walls.
  • EAdd a fat source to the same meal.
2Numeric answerChecked instantly

A dish contains 6 mg of beta-carotene and you absorb 15% of it. How many µg RAE reach your bloodstream? Enter only the number.

3Short answerMarked by AI

A friend says: "I eat a huge bowl of raw carrot sticks every day, no oil, and my palms are turning orange — that proves I'm getting all the vitamin A I need." In 2–4 sentences, untangle this. Identify what the orange palms actually indicate, name the two reasons raw carrot sticks without fat deliver little vitamin A, and state what would make the meal work.

Graded on Explains what the orange palms indicate · Identifies both bioavailability barriers · Prescribes a fix grounded in the walkthrough

Go deeper

Reach for this when a headline or article claims a nutrient is "poorly absorbed" or "highly bioavailable" — it gives the general definition of bioavailability and the full list of factors (food matrix, solubility, inhibitors, individual state) behind it.

Lesson 37

Minerals and electrolytes

You will be able to name the major minerals and trace minerals, and explain why sodium, potassium and calcium are critical for nerve and muscle function. Covers electrolyte balance, bone mineral density, and iron transport. Prevents the error of only tracking macros while ignoring mineral intake.

35 min4 assessments

You already know that the body needs vitamins to unlock the energy inside food. But a vitamin is a fragile molecule — break it with heat, or lose it in urine, and the reaction stops. Minerals are different. They are elements, single atoms like sodium, potassium, calcium, and iron. You cannot burn them, you cannot dissolve them away. What you can do is run out of them, and when you do, the body's electrical system — the nerves that fire, the muscles that contract, the heart that beats — shuts down.

Minerals are split into two groups by how much you need each day. The major minerals (calcium, phosphorus, magnesium, sodium, potassium, chloride, sulfur) are needed in amounts greater than 100 mg per day. The trace minerals (iron, zinc, iodine, selenium, copper, manganese, fluoride, chromium, molybdenum) are needed in tiny amounts, but they are just as essential. Of all of them, three — sodium, potassium, and calcium — are the ones that control the electrical signals that make you move, think, and live.

This node is not a list to memorise. It is a map of which minerals do what, where you get them, and how much you really need — so that when you read a label or a study headline, you know which numbers matter.

Reference

Major and trace minerals at a glance

Calcium

Group
Major
Key function
Bone density, muscle contraction, nerve signalling
Adult RDA / AI
1000–1200 mg
Top food sources
Dairy, fortified plant milk, sardines, kale

Chloride

Group
Major
Key function
Fluid balance, stomach acid (HCl)
Adult RDA / AI
2300 mg (as NaCl)
Top food sources
Table salt, seaweed, olives

Magnesium

Group
Major
Key function
Muscle relaxation, ATP production, bone structure
Adult RDA / AI
310–420 mg
Top food sources
Almonds, spinach, black beans, pumpkin seeds

Phosphorus

Group
Major
Key function
Bone mineral, ATP, DNA backbone
Adult RDA / AI
700 mg
Top food sources
Meat, dairy, whole grains, nuts

Potassium

Group
Major
Key function
Nerve impulse, muscle contraction, blood pressure regulation
Adult RDA / AI
2600–3400 mg
Top food sources
Bananas, potatoes, avocados, tomatoes, beans

Sodium

Group
Major
Key function
Nerve impulse, fluid balance, muscle contraction
Adult RDA / AI
1500 mg (max 2300)
Top food sources
Table salt, processed foods, cheese, bread

Sulfur

Group
Major
Key function
Amino acids (cysteine, methionine), detoxification
Adult RDA / AI
None set (from protein)
Top food sources
Eggs, meat, fish, garlic, onion

Iron

Group
Trace
Key function
Oxygen transport (hemoglobin), energy metabolism
Adult RDA / AI
8–18 mg
Top food sources
Red meat, spinach, lentils, fortified cereals

Zinc

Group
Trace
Key function
Immune function, wound healing, DNA synthesis
Adult RDA / AI
8–11 mg
Top food sources
Oysters, beef, pumpkin seeds, chickpeas

Iodine

Group
Trace
Key function
Thyroid hormone (T3/T4) production
Adult RDA / AI
150 µg
Top food sources
Iodised salt, seafood, seaweed, dairy

Selenium

Group
Trace
Key function
Antioxidant (selenoproteins), thyroid function
Adult RDA / AI
55 µg
Top food sources
Brazil nuts, tuna, sardines, eggs

Copper

Group
Trace
Key function
Iron metabolism, collagen formation, nerve function
Adult RDA / AI
900 µg
Top food sources
Liver, shellfish, nuts, seeds, dark chocolate

Manganese

Group
Trace
Key function
Bone formation, antioxidant enzyme (SOD)
Adult RDA / AI
1.8–2.3 mg
Top food sources
Pineapple, whole grains, nuts, tea

Fluoride

Group
Trace
Key function
Dental enamel strength, bone mineralisation
Adult RDA / AI
3–4 mg
Top food sources
Fluoridated water, tea, fish with bones

Chromium

Group
Trace
Key function
Insulin action, glucose metabolism
Adult RDA / AI
20–35 µg
Top food sources
Broccoli, whole grains, meat, brewer's yeast

Molybdenum

Group
Trace
Key function
Enzyme cofactor (sulfite oxidase, xanthine oxidase)
Adult RDA / AI
45 µg
Top food sources
Legumes, grains, leafy vegetables

RDAs vary by age, sex, and pregnancy. The values shown are for adults aged 19–50. AI (Adequate Intake) is used when no RDA is established.

Practice
0/12 known
1 / 12
Check yourself

Check your understanding of mineral roles and sources.

1Multiple choiceChecked instantly

A 45-year-old woman has been taking a diuretic for hypertension and now complains of muscle weakness and occasional heart palpitations. Which mineral imbalance is most likely the cause?

  • AExcess sodium because diuretics often cause salt retention
  • BLow potassium because loop/thiazide diuretics increase potassium excretion
  • CHigh calcium because diuretics reduce calcium excretion
  • DLow magnesium because diuretics only affect sodium and potassium
2Fill the blanksChecked instantly
3Select all that applyChecked instantly

Which of the following are trace minerals? (Select all that apply.)

  • AIron
  • BCalcium
  • CZinc
  • DPotassium
  • EIodine
  • FMagnesium
4Short answerMarked by AI

A person consumes 500 mg of calcium per day through diet. The DRI for calcium is 1000 mg. What is the most accurate statement about this intake?

Lesson 38

Major minerals

Calcium, magnesium, potassium, sodium: roles in bone health, muscle contraction, nerve function, and fluid balance.

15 min4 assessments

Your body needs four major minerals in larger amounts than any other mineral: calcium, magnesium, potassium, and sodium. Each one has a specific job:

  • Calcium builds bones and teeth, and helps muscles contract and nerves send signals.
  • Magnesium helps muscles relax after contraction, supports nerve function, and is part of over 300 enzyme reactions.
  • Potassium balances fluids inside your cells and helps nerves fire and muscles contract.
  • Sodium balances fluids outside your cells and is essential for nerve impulses.

You already know from the previous node that these are electrolytes—they carry an electric charge when dissolved in water. That charge is what makes them work in nerve and muscle function. The difference between them is where they act and what happens when you get too little or too much.

You get these minerals from food. A balanced diet with vegetables, dairy, legumes, and whole grains usually covers your needs. The table below shows the amounts adults need each day and the best sources.

Reference

Major Minerals at a Glance

Calcium

Key Functions
Bone structure, muscle contraction, nerve signaling, blood clotting
Adult RDA (mg/day)
1000–1300
Top Food Sources
Dairy (milk, yogurt, cheese), fortified plant milks, sardines, kale, broccoli
Deficiency Signs
Weak bones (osteoporosis), muscle cramps, numbness

Magnesium

Key Functions
Muscle relaxation, nerve transmission, energy production, protein synthesis
Adult RDA (mg/day)
310–420
Top Food Sources
Spinach, almonds, black beans, pumpkin seeds, whole wheat bread
Deficiency Signs
Muscle twitches, fatigue, irregular heartbeat

Potassium

Key Functions
Fluid balance inside cells, nerve impulses, muscle contraction (especially heart)
Adult RDA (mg/day)
2600–3400
Top Food Sources
Bananas, potatoes (with skin), avocados, spinach, beans, orange juice
Deficiency Signs
Weakness, constipation, heart palpitations

Sodium

Key Functions
Fluid balance outside cells, nerve impulses, muscle contraction
Adult RDA (mg/day)
<2300 (upper limit)
Top Food Sources
Table salt, processed foods (canned soups, chips, deli meats), soy sauce
Deficiency Signs
Rare in excess intake; low sodium causes dizziness, confusion

RDAs vary by age, pregnancy, and health conditions. The sodium value is an upper limit, not a minimum—most people get enough from food without adding salt.

Practice
0/10 known
1 / 10
  • The four major minerals—calcium, magnesium, potassium, and sodium—each have distinct roles in bone health, muscle function, nerve signaling, and fluid balance.
  • Calcium and magnesium work together: calcium triggers contraction, magnesium triggers relaxation.
  • Potassium and sodium work as a pair: potassium inside cells, sodium outside cells, maintaining the electrical gradient that nerves and muscles need.
  • RDAs for calcium, magnesium, and potassium are minimums; the sodium value is a maximum because excess is common in processed foods.
  • Deficiency signs are specific to each mineral—knowing them helps you spot potential problems in your own diet.

A Day's Meals and Their Major Minerals

Here is one day of eating that meets the RDA for all four major minerals:

Breakfast: 1 cup oatmeal (made with milk) + 1 banana

  • Calcium: ~300 mg (from milk)
  • Magnesium: ~60 mg (from oats)
  • Potassium: ~420 mg (from banana)
  • Sodium: ~5 mg (natural)

Lunch: Spinach salad with chickpeas, avocado, and a sprinkle of almonds

  • Calcium: ~100 mg (from spinach)
  • Magnesium: ~120 mg (from spinach + almonds + chickpeas)
  • Potassium: ~700 mg (from avocado + spinach)
  • Sodium: ~30 mg (from dressing)

Dinner: Grilled salmon with baked potato (skin on) and steamed broccoli

  • Calcium: ~100 mg (from broccoli)
  • Magnesium: ~80 mg (from potato + salmon)
  • Potassium: ~900 mg (from potato + salmon + broccoli)
  • Sodium: ~80 mg (natural)

Snack: Greek yogurt with a handful of pumpkin seeds

  • Calcium: ~200 mg (from yogurt)
  • Magnesium: ~70 mg (from seeds)
  • Potassium: ~250 mg (from yogurt)
  • Sodium: ~80 mg (from yogurt)

Totals: Calcium ~700 mg (still need more—add cheese or fortified milk); Magnesium ~330 mg (meets RDA for women); Potassium ~2270 mg (close to RDA); Sodium ~195 mg (well below limit). This example shows that a whole-foods diet naturally provides potassium and magnesium but calcium often needs a dairy or fortified source.

Check yourself

Test your understanding of major minerals.

1Multiple choiceChecked instantly

Which mineral is primarily responsible for triggering muscle contraction, while another mineral is needed for relaxation?

  • ACalcium triggers contraction; magnesium triggers relaxation.
  • BSodium triggers contraction; potassium triggers relaxation.
  • CPotassium triggers contraction; calcium triggers relaxation.
  • DMagnesium triggers contraction; sodium triggers relaxation.
2Select all that applyChecked instantly

Which of the following are good food sources of potassium? (Select all that apply.)

  • ABananas
  • BPotatoes with skin
  • CCheese
  • DAvocados
  • EWhite bread
3Fill the blanksChecked instantly
4Short answerMarked by AI

A person experiences muscle twitches and fatigue. Which mineral deficiency is most likely?

Lesson 39

Trace minerals

Iron, zinc, iodine, selenium: key functions, deficiency risks, and dietary sources.

15 min3 assessments

After learning about the major minerals—sodium, potassium, calcium—you now meet the trace minerals: elements your body needs in tiny amounts (less than 100 mg per day) but cannot function without. The four you'll deal with most often are iron, zinc, iodine, and selenium.

Each has a specific role: iron carries oxygen in your blood, zinc helps enzymes work and immunity, iodine is the backbone of thyroid hormones, and selenium protects cells from damage. Deficiencies show up in predictable ways—fatigue, poor wound healing, goiter, muscle weakness—and are surprisingly common even in well-fed populations. The good news: one well-chosen meal can cover your daily need for all four.

Reference

Trace Minerals at a Glance

Iodine

Key Functions
Production of thyroid hormones (T3, T4) that regulate metabolism
Deficiency Symptoms
Goiter, fatigue, weight gain, cognitive impairment
Rich Food Sources
Iodized salt, seaweed, fish, dairy, eggs

Iron

Key Functions
Oxygen transport in hemoglobin, energy production in cells
Deficiency Symptoms
Anemia (fatigue, pale skin, shortness of breath), weakened immunity
Rich Food Sources
Red meat, poultry, fish, beans, spinach, fortified cereals (pair with vitamin C for better absorption)

Selenium

Key Functions
Antioxidant enzyme function, thyroid hormone metabolism
Deficiency Symptoms
Keshan disease (heart muscle damage), Kashin-Beck disease (joints), muscle weakness
Rich Food Sources
Brazil nuts, seafood, eggs, sunflower seeds, whole grains (soil-dependent)

Zinc

Key Functions
Immune function, wound healing, DNA synthesis, growth
Deficiency Symptoms
Stunted growth, hair loss, diarrhea, frequent infections, poor wound healing
Rich Food Sources
Oysters, red meat, poultry, beans, nuts, whole grains

Deficiency risks are highest in regions with poor soil content, restrictive diets, or conditions that increase absorption needs (e.g., pregnancy, heavy menstruation).

Practice
0/8 known
1 / 8
  • Iron deficiency is the most common nutritional deficiency worldwide, causing anemia and fatigue.
  • Zinc deficiency impairs immune function and wound healing; it's a major cause of stunted growth in children.
  • Iodine deficiency is the leading preventable cause of intellectual disability globally; iodized salt eliminates the risk.
  • Selenium acts as an antioxidant; a single Brazil nut provides more than the daily requirement.
  • Trace mineral absorption can be boosted (vitamin C with iron) or blocked (tannins in tea with iron).
Check yourself

Test your understanding of trace minerals.

1Multiple choiceChecked instantly

A child presents with stunted growth, poor wound healing, and frequent infections. Which trace mineral deficiency is most likely?

  • AIron
  • BZinc
  • CIodine
  • DSelenium
2Fill the blanksChecked instantly
3Select all that applyChecked instantly

A dietitian is advising a client who wants to increase iron absorption from plant-based sources. Which of the following strategies would help? (Select two.)

  • AEat legumes with a side of vitamin C-rich foods like bell peppers or citrus fruit.
  • BDrink coffee or tea with meals to provide antioxidants.
  • CInclude a small amount of meat or fish in the same meal.
  • DAvoid cooking in cast iron pans because iron is toxic.
  • ETake calcium supplements with meals to strengthen bones.

Lesson 40

Electrolyte balance

Sodium-potassium pump, hydration, muscle contraction, and signs of electrolyte imbalance.

10 min3 assessments

Your cells are tiny bags of salty water surrounded by slightly different salty water. The difference between the salt concentration inside and outside each cell is what keeps your nerves firing, your muscles contracting, and your heart beating in rhythm. That difference is electrolyte balance — and when it tips, everything starts to misfire.

Sodium (Na⁺) and potassium (K⁺) are the main players. Your cells pump sodium out and pull potassium in, using the sodium‑potassium pump (Na⁺/K⁺‑ATPase). This creates an electrical gradient — a tiny battery — that your nerves and muscles use to send signals. Calcium (Ca²⁺) and magnesium (Mg²⁺) also play supporting roles in contraction and relaxation.

Balance matters because water follows salt. If blood sodium drops too low (hyponatremia), water moves into cells, swelling them — brain cells swell, causing confusion and headache. If sodium rises too high (hypernatremia), water leaves cells, shrinking them — brain cells shrink, causing thirst and agitation. Potassium imbalances hit the heart: too little (hypokalemia) causes weakness and cramps; too much (hyperkalemia) can stop the heart.

The body regulates this through the kidneys, hormones (aldosterone, ADH), and thirst. But heavy sweating, vomiting, diarrhoea, or drinking only water after exercise can overwhelm the system.

The sodium‑potassium pump maintains the gradient that powers nerve and muscle function. When the gradient fails, symptoms follow.

Analogy

Think of your cells as rechargeable batteries. The sodium‑potassium pump is the charger that keeps the positive and negative sides separate. Sodium is the positive terminal outside, potassium is the negative terminal inside. The voltage between them is what powers your nerves and muscles — just like a battery powers a phone.

When you sweat heavily, you lose sodium and potassium — that's like draining the battery. Drinking plain water without electrolytes is like pouring distilled water into a battery: it dilutes the remaining charge and the voltage drops further.

Where the analogy breaks down

Real batteries are passive; your body actively pumps ions using ATP. You can't 'recharge' electrolytes instantly — the kidneys and hormones take hours to restore balance. Also, a dead battery is useless; a mild electrolyte imbalance can still be corrected with food and rest.

Common misconception

“"If I'm thirsty after exercise, plain water is all I need."”

Thirst is the body's signal for water, and water is essential for rehydration. Many people have been told to 'drink plenty of water' and never had a problem.

What is actually true

After heavy sweating (running, cycling, hot weather), you lose both water AND electrolytes. Drinking only water dilutes the remaining sodium in your blood, which can cause hyponatremia — confusion, headache, and in severe cases, seizures. Rehydration should include electrolytes (sodium, potassium) from food or a sports drink, especially if you sweat a lot.

An electrolyte analyzer, a medical device with a screen showing test results for sodium, potassium, chloride, and calcium levels, with normal ranges indicated.
CC BY-SA 4.0· Ajay Kumar Chaurasiya source
Check yourself

Check your understanding of electrolyte balance.

1Select all that applyChecked instantly

Which of the following are common signs of electrolyte imbalance? (Select all that apply.)

  • AMuscle cramps
  • BDry, flaky skin
  • CConfusion or disorientation
  • DIncreased appetite
2Short answerMarked by AI

A marathon runner drinks only plain water after the race and begins to feel dizzy, confused, and nauseous. Explain why this happens in terms of electrolyte balance, and describe what the runner should do instead.

Graded on Identifies the mechanism (dilution of sodium / hyponatremia) · Links symptoms to the mechanism · Recommends appropriate corrective action

3Multiple choiceChecked instantly

The sodium‑potassium pump moves sodium __ and potassium __ across the cell membrane.

  • Ain, in
  • Bout, in
  • Cin, out
  • Dout, out

Lesson 41

Iron transport and anemia

Heme vs non-heme iron, absorption enhancers and inhibitors, and iron deficiency anemia diagnosis.

10 min4 assessments
Decide

You’ve been feeling unusually tired for weeks, your skin looks paler than normal, and you keep finding yourself craving ice cubes. A friend says you might be anemic. You decide to investigate.

What’s your first move to figure out what’s going on?

Decision tree for diagnosing iron deficiency anemia based on initial symptoms and lab results.

Go deeper

Use these articles to explore the full list of symptoms, causes, and diagnostic criteria for anemia and iron deficiency.

  • Heme iron (from animal sources) is absorbed 2-3 times more efficiently than non-heme iron (from plants).
  • Vitamin C enhances non-heme iron absorption; calcium, tannins (tea), and phytates (whole grains) inhibit it.
  • Iron deficiency anemia shows low hemoglobin (Hb) and low mean corpuscular volume (MCV) – a microcytic hypochromic anemia.
  • Ferritin is the best single test for iron stores: <30 ng/mL indicates depleted stores; <12 ng/mL confirms deficiency.
  • Serum iron + TIBC identifies the problem: low iron + high TIBC = iron deficiency; low iron + low TIBC = anemia of chronic disease.
  • Pica (craving ice, dirt, or starch) is a classic symptom of severe iron deficiency.
Check yourself

Now apply what you’ve learned about diagnosing iron deficiency anemia.

1Put in orderChecked instantly

Arrange the following diagnostic steps for iron deficiency anemia in the correct order from initial presentation to confirmation.

  • AOrder CBC and ferritin
  • BAssess symptoms (fatigue, pallor, pica)
  • CConfirm with serum iron and TIBC
  • DInterpret low Hb, low MCV, low ferritin as iron deficiency
2Short answerMarked by AI

A patient has hemoglobin 11 g/dL, MCV 80 fL, and ferritin 15 ng/mL. What type of anemia do these values suggest, and which two lab tests would you order to strengthen the diagnosis? (2-3 sentences)

Graded on Identifies the anemia type correctly from the given values. · Recommends the correct confirmatory tests. · Explains the expected pattern.

3Short answerMarked by AI

Ferritin is often called an 'acute phase reactant' – it rises with inflammation. Why might a ferritin level of 50 ng/mL in a person with low Hb and low MCV still be consistent with iron deficiency? (2-3 sentences)

Graded on Recognizes ferritin’s limitation in inflammation. · Proposes a strategy to resolve the ambiguity. · Correctly interprets the hypothetical '50 ng/mL' value.

4Select all that applyChecked instantly

Which of the following are known enhancers or inhibitors of iron absorption? Select all that apply. (More than one is correct.)

  • AVitamin C (enhances non-heme iron absorption)
  • BCalcium from dairy (inhibits both heme and non-heme iron absorption)
  • CTannins in tea (inhibit non-heme iron absorption)
  • DMeat protein (enhances heme iron absorption only)
  • EPhytates in whole grains (inhibit non-heme iron absorption)

Lesson 42

Reading a nutrition facts label in 60 seconds

You will be able to scan a nutrition label and extract serving size, total energy, macronutrient breakdown, and added sugars. Covers the order of ingredients, percent daily values, and how manufacturers hide serving sizes. Prevents being misled by '0g trans fat' claims on foods that contain partially hydrogenated oils.

25 min3 assessments

You can read a nutrition label in about 60 seconds once you know where to look and what to ignore. The trick is a fixed sequence: serving size first, then calories, then the macronutrients that matter, then the fine print. Jumping to calories first is the most common mistake — the number means nothing until you know how many servings you're actually eating.

This walkthrough gives you a step‑by‑step routine. Use it every time you pick up a packaged food. After a few repetitions you'll do it automatically.

Steps
0/6

Grab any packaged food. Open the Nutrition Facts panel. Follow these steps in order. Each step tells you what to look for, what can go wrong, and how to know you got it right.

  1. Find the serving size and servings per container

    The first line under "Nutrition Facts" is Serving Size (e.g., 1 cup, 28 g). Right below it is Servings Per Container (e.g., 4). Write both down or memorize them.

    Manufacturers sometimes set an unrealistically small serving size so the numbers look low. A 200‑calorie cookie that says "serving size: ½ cookie" is really 400 calories if you eat the whole thing.

    You see two numbers: the amount (e.g., 1 cup) and the count of servings in the whole package.

  2. Read the calories per serving

    Calories are the second line, in bold. This is the energy in one serving. Multiply by servings per container to get the total package calories.

    Some packages have multiple servings but look like a single‑serve item (e.g., a small bag of chips with 2 servings).

    You have a number (e.g., 250) and you know it's per serving, not per package.

  3. Check total fat, saturated fat, and trans fat

    Look at Total Fat, then Saturated Fat, then Trans Fat. The % Daily Value (%DV) is on the right. For saturated fat, aim for less than 5 %DV per serving.

    Trans fat may say 0 g even if the product contains partially hydrogenated oils — the law allows rounding down below 0.5 g. Always check the ingredients list for "partially hydrogenated" to be sure.

    You see numbers for each fat type. If trans fat is 0 g, glance at the ingredients list for hidden oils.

  4. Look at carbohydrates: total, fiber, and added sugars

    Total Carbohydrate includes fiber, sugars, and added sugars. Focus on Dietary Fiber (aim for 20‑25 g per day) and Added Sugars (the 2020‑2025 Dietary Guidelines recommend less than 10 % of total calories from added sugars).

    Some labels list "Sugars" without separating added sugars. If you see only "Sugars", assume they are mostly added unless the food is fruit or dairy.

    You see a line for Added Sugars (or just Sugars). Compare it to the daily limit of ~50 g for a 2000‑calorie diet.

  5. Read the ingredients list (below the nutrition facts panel)

    Ingredients are listed in descending order by weight. The first three ingredients are the majority of the product. If sugar is the first or second ingredient, the item is mostly sugar.

    Manufacturers split sugar into multiple names (high fructose corn syrup, cane syrup, honey, maltose) to push each further down the list.

    You can name the top three ingredients and identify whether added sugars appear more than once.

  6. Apply the 5/20 rule to %DV

    Quick rule: 5 %DV or less is low; 20 %DV or more is high. Use it for nutrients you want more of (fiber, vitamins) and those you want less of (saturated fat, sodium, added sugars).

    The %DV is based on a 2000‑calorie diet. If your needs differ, the %DV is still a useful relative guide but not a personal target.

    You can point to a nutrient and say whether it's low or high in 5 seconds.

Checklist
0/8

60‑Second Label Scan Checklist

Keep this checklist open while you shop. Ticking all eight items takes under a minute.

Check yourself

Now apply what you've learned. These questions test your ability to scan a label and spot misleading numbers.

1Put in orderChecked instantly

Arrange the following steps in the correct order for scanning a nutrition label in 60 seconds. (Drag each step to the correct position.)

  • ARead serving size and servings per container
  • BCheck total fat, saturated fat, and trans fat
  • CLook at calories per serving
  • DExamine carbohydrates, fiber, and added sugars
  • ERead the ingredients list
  • FApply the 5/20 rule to %DV
2Short answerMarked by AI

A cereal box says '0g trans fat' on the front. The Nutrition Facts panel also shows 0g trans fat. However, the ingredients list includes 'partially hydrogenated soybean oil'. Explain how this is possible and what it means for the consumer. (2–4 sentences)

Graded on Identifies the rounding rule (≤0.5 g per serving can be rounded to 0 g) · Explains the consumer implication · Uses correct terminology (partially hydrogenated oils)

3Short answerMarked by AI

A bag of trail mix has a serving size of 1/4 cup (30 g) and 4 servings per container. The label lists 160 calories per serving, 10 g total fat, 2 g saturated fat, 5 g protein, 18 g carbohydrates, 2 g fiber, and 9 g added sugars. The ingredients list begins with 'chocolate chips, peanuts, raisins, coconut oil'.

Calculate the total calories in the whole bag. Then, based on the 5/20 rule, say whether the saturated fat is low or high per serving, and justify your answer using the %DV (you'll need to recall that the daily value for saturated fat is 20 g; assume the label shows %DV of 10% for saturated fat). Is the added sugar content per serving a concern? (2–4 sentences)

Graded on Correctly calculates total calories for the whole bag · Applies 5/20 rule to saturated fat %DV correctly · Evaluates added sugar concern with reasoning

Lesson 43

Common label tricks and marketing claims

You will be able to spot and decode six common front-of-package claims that mislead consumers. Covers 'natural', 'made with whole grains', 'gluten-free' on inherently gluten-free foods, and health halos. Prevents paying more for a product because the packaging looks healthy.

20 min3 assessments

You already know how to read a Nutrition Facts panel in 60 seconds. Now turn your attention to the front of the package — the part designed to sell, not to inform. Front-of-package claims like 'Natural', 'Made with whole grains', and 'Gluten-free' are not regulated as strictly as the label on the back. They are legal, but they are often misleading. The skill you need is not to take them at face value, but to use them as a starting point — then flip the package over and check the ingredients and the Nutrition Facts. This lesson gives you the decoder ring for six common tricks.

Common misconception

“If a product says 'Natural', it means it's healthy and minimally processed.”

The word 'natural' conjures images of unprocessed, wholesome food. Many shoppers assume that a 'natural' label means the product is free of additives, preservatives, and artificial ingredients.

What is actually true

The FDA has no formal definition for 'natural' except for meat and poultry products (where it prohibits artificial flavors and colors). For most packaged foods, the term is essentially meaningless. A 'natural' cookie can still be loaded with sugar, refined flour, and saturated fat. Always check the ingredients list and Nutrition Facts panel instead of trusting the word 'natural'.

Each of these six claims appears on thousands of products. The chart below shows what each claim really means, how to verify it, and when to trust it.

Natural

Legal definition (FDA)
No official definition (except for meat/poultry)
What the ingredients list typically reveals
May still contain artificial flavors, preservatives, or high-fructose corn syrup
Best way to verify
Check ingredients for artificial additives; ignore the word 'natural'

Best for Only trust on meat products with a USDA label; otherwise, treat as a marketing term.

Made with whole grains

Legal definition (FDA)
No standard; can be used even if whole grains are not the main ingredient
What the ingredients list typically reveals
Often the first ingredient is refined flour; whole grains appear much later
Best way to verify
Look at the ingredients list: the first ingredient should be a whole grain (e.g., 'whole wheat flour')

Best for Trust only if the first ingredient is a whole grain AND the product is also low in added sugar.

Gluten-free

Legal definition (FDA)
FDA defines: ≤20 ppm gluten; voluntary claim
What the ingredients list typically reveals
Often used on inherently gluten-free foods (e.g., rice, water, soda) to create a health halo
Best way to verify
Check the product's food category: if it's already gluten-free (like fruit), the claim is just marketing

Best for Trust on products that could contain gluten (bread, pasta, granola); ignore on inherently gluten-free items.

Low-fat

Legal definition (FDA)
FDA defines: ≤3 g fat per serving; also 'reduced fat' has specific rules
What the ingredients list typically reveals
Often high in added sugar to compensate for the missing fat
Best way to verify
Compare the total sugar and calories to the full-fat version; also check serving size

Best for Rarely trust; if you choose, also check that sugar is not the first ingredient.

No added sugar

Legal definition (FDA)
FDA defines: no added sugars during processing; does not account for natural sugars
What the ingredients list typically reveals
Product may still be very high in natural sugars (e.g., dried fruit, yogurt)
Best way to verify
Check the total sugar on the label; compare to the product's serving size

Best for Trust only if the product is low in total sugar (e.g., unsweetened almond milk).

A 'Made with whole grains' cereal: what's really inside?

Front of the box: 'Made with Whole Grains!', 'Good Source of Fiber'

Ingredients list (excerpt): Corn flour, sugar, whole wheat flour, oat flour, salt, ...

The first ingredient is corn flour (a refined grain), the second is sugar, and only third is whole wheat flour. The claim 'Made with whole grains' is legally true — the product does contain whole wheat flour — but it is misleading because the main ingredient is a refined grain, and the product is high in added sugar.

What to do: Ignore the front-of-package claim. Flip to the Nutrition Facts panel: check the added sugars (likely high) and the fiber (likely low). Then look at the ingredients list: if the first ingredient is not a whole grain, the product is not a whole-grain food.

  • Front-of-package claims are not regulated as strictly as the Nutrition Facts panel.
  • The word 'Natural' has no official meaning for most foods and is often used to distract from unhealthy ingredients.
  • 'Made with whole grains' does not guarantee that whole grains are the main ingredient; check the ingredients list.
  • 'Gluten-free' on inherently gluten-free foods (e.g., water, rice) is a marketing tactic, not a health claim.
  • 'Low-fat', 'No added sugar', and 'Light' all have legal definitions, but the products may still be high in sugar, calories, or other additives.
  • Always verify a front-of-package claim by looking at the ingredients list and the Nutrition Facts panel.
Check yourself

Test your ability to spot misleading claims.

1Multiple choiceChecked instantly

Which of the following is true about the 'Natural' claim on a box of crackers?

  • AIt means the product contains no artificial ingredients.
  • BIt has a strict FDA definition and must be verified.
  • CIt has no official definition (except for meat) and is essentially meaningless.
  • DIt means the product is organic and contains no pesticides.
2Select all that applyChecked instantly

Which of the following front-of-package claims are regulated by the FDA with specific definitions? (Select all that apply.)

  • ANatural
  • BMade with whole grains
  • CGluten-free
  • DLow-fat
  • ELight
3Short answerMarked by AI

A friend buys a box of crackers labeled 'Gluten-free' and says, 'It must be healthy because it's gluten-free.' Write two sentences explaining why that claim can be misleading, referring to what you learned about the Nutrition Facts panel.

Graded on Identifies that gluten-free does not imply healthy · Refers to the Nutrition Facts panel as the authoritative source

Lesson 44

Serving size and servings

Identifying serving size, calculating calories per serving vs whole package, and spotting manipulated sizes.

10 min2 assessments
Steps
0/5

Serving size is the trickiest part of a nutrition label. Here’s how to decode it and calculate what you actually eat.

  1. Find the serving size line

    Look at the top of the Nutrition Facts panel. It says 'Serving Size' and gives a standard amount, e.g. '1 cup (228g)'. This is the reference amount for all the numbers below it.

    Don't assume it's the whole package. Many packages contain multiple servings.

    The serving size is clearly stated with a unit (cups, grams, pieces, etc.)

  2. Read the servings per container

    Directly below the serving size, find 'Servings Per Container' or 'Servings Per Package'. This tells you how many serving-sized portions are in the whole package.

    If the label says 'About 2', it's rounded. Use the exact number if possible, but treat it as an estimate.

    You have noted the number of servings per container (e.g., 4, 8, about 2).

  3. Get the calories per serving

    Under 'Calories', find the number per serving. This is the energy for one serving size only.

    If you eat more or less than the serving size, you need to adjust proportionally.

    Calories per serving is visible (e.g., 150).

  4. Calculate total calories for the whole package

    Multiply the calories per serving by the number of servings per container. Example: 150 calories/serving × 4 servings = 600 calories for the whole bag.

    If the label lists 'Calories' for the whole container separately (some do), you can skip this step. But always verify by multiplying.

    Your calculation matches the 'Calories per container' if listed, or is reasonable.

  5. Adjust for your actual portion

    If you ate half a serving, divide the calories by 2. If you ate two servings, double the calories. Use the serving size as a ruler for your portion.

    People often eat straight from the package without measuring. A handful of chips might be 2–3 servings.

    You can state how many servings you actually ate and the corresponding calories.

Checklist
0/5

Decoding a Nutrition Label – Field Checklist

Keep this checklist beside you when you shop or cook. Tick each item after you find it on the label.

Chip Bag Calculation

Label on a bag of salted chips:

  • Serving Size: 28g (about 11 chips)
  • Servings Per Container: 4
  • Calories: 150 per serving

What you do:

  1. 1.Note the serving size: 28g = 11 chips.
  2. 2.Servings per container: 4.
  3. 3.Calories per serving: 150.
  4. 4.Total package calories: 150 × 4 = 600 calories.
  5. 5.If you eat 2 servings (22 chips), you consume 150 × 2 = 300 calories.

Moral: The bag looks like a snack, but it's 4 meals' worth of chips.

  • Serving size is a standardized reference, not a recommended portion.
  • Servings per container tells you how many such references are in the whole package.
  • Total calories per package = calories per serving × servings per container.
  • Manufacturers may use small serving sizes to make calorie numbers look lower.
  • Always compare your actual portion to the serving size to avoid underestimating energy intake.
Go deeper

Read the Wikipedia article for a deeper look at how serving sizes are set and manipulated across different countries and products.

Check yourself
1Put in orderChecked instantly

Arrange the following steps in the correct order to calculate the total calories in a package of cookies from its nutrition label. (Write the letters in order.)

  • ALook up the calories per serving.
  • BMultiply calories per serving by servings per container.
  • CFind the number of servings per container.
  • DIdentify the serving size in grams or cups.
  • EAdjust for the actual portion you ate (if different).
2Short answerMarked by AI

Why might a food manufacturer list a very small serving size (e.g., 10g for a candy bar that weighs 100g)? Explain the motivation and the consequence for a consumer who eats the whole bar without checking the label.

Graded on Identifies the motivation (makes numbers look smaller) · Describes consumer consequence (underestimating total intake) · Provides a clear, specific example (optional but helpful)

Lesson 45

Macros and % Daily Value

Reading total fat, carbs, protein, fiber, and using %DV to gauge nutrient density.

10 min4 assessments
  • % Daily Value (%DV) is based on a 2,000-calorie diet; your personal needs may differ.
  • A %DV of 5% or less per serving is considered low; 20% or more is high.
  • %DV helps you quickly judge whether a food is high or low in a nutrient without memorizing gram targets.
  • For nutrients you want more of (fiber, protein, vitamins), aim for higher %DV; for saturated fat, sodium, and added sugars, aim for lower %DV.
  • Total fat, carbs, and protein are listed in grams, but %DV tells you their contribution to your daily limit or goal.

Comparing two packaged meals using %DV

Meal A (single serving)

  • Total Fat: 12g — %DV 18%
  • Saturated Fat: 4g — %DV 20%
  • Dietary Fiber: 3g — %DV 11%
  • Protein: 8g — %DV 16%

Meal B (single serving)

  • Total Fat: 3g — %DV 5%
  • Saturated Fat: 1g — %DV 5%
  • Dietary Fiber: 8g — %DV 32%
  • Protein: 5g — %DV 10%

By %DV alone, Meal B is lower in fat (especially saturated fat) and higher in fiber. Meal A is moderate in fat but high in saturated fat (20% is a high %DV). If your goal is to limit saturated fat and increase fiber, Meal B is the better choice.

Steps
0/5

To evaluate a product's macros and nutrient density, work through the label in this order. Use %DV to decide if the food is low or high in each nutrient.

  1. Check the serving size and servings per container

    Find the serving size (e.g., 1 cup, 28 g) and the number of servings. All other numbers on the label apply to one serving, not the whole container.

    If you eat more than one serving, multiply all gram amounts and %DV values by the number of servings you actually consume.

    The serving size is the first line after 'Nutrition Facts'. Confirm you know how many servings you are about to eat.

  2. Read total fat and saturated fat

    Look at the line 'Total Fat' (grams) and its %DV. Then note 'Saturated Fat' (grams) and its %DV. Trans fat has no %DV, so only watch its gram amount.

    Do not mistake 'Total Fat' %DV for just saturated fat. Total fat includes unsaturated fats, which are healthier; only the %DV for saturated fat tells you the limit.

    If Saturated Fat %DV is 20% or more, this food is high in saturated fat.

  3. Check carbohydrates, fiber, and total sugars

    Total Carbohydrate (g) includes starch, fiber, and sugars. Dietary Fiber (g) and its %DV tell you how much toward the daily fiber goal (28 g) you get. Total Sugars includes added sugars; Added Sugars has its own %DV.

    Do not use the %DV for Total Carbohydrates as a guide for fiber. Fiber's %DV is separate and lower is not better – you want high %DV for fiber.

    Dietary Fiber %DV should be 20% or more to be a high-fiber food.

  4. Read protein grams

    Protein is listed in grams. It usually does not have a %DV because daily protein needs vary widely. If it does have a %DV, it is based on 50 g per day.

    Do not rely on %DV for protein if it's missing; use gram amount alone and compare to your personal target (e.g., 0.8 g per kg of body weight).

    The protein gram amount is present. If %DV is shown, note it, but prioritize the gram count.

  5. Use %DV to compare products

    Look at the %DV for saturated fat, sodium, added sugars, fiber, and protein. A quick scan tells you if this food is a nutrient-dense choice. For less healthy nutrients, prefer 5% or less; for beneficial nutrients, prefer 20% or more.

    The %DV thresholds (5% low, 20% high) are general guidelines. If you have specific health conditions, your doctor may give different targets.

    You can now pick the healthier option between two similar products by comparing %DV columns.

Checklist
0/6

Macro & %DV label check

Use this checklist when comparing two products at the grocery store. It takes 30 seconds.

Check yourself

Test your ability to read macros and %DV.

1Put in orderChecked instantly

Arrange these steps in the correct order when evaluating a nutrition facts label.

  • ACheck the %DV for saturated fat and fiber.
  • BIdentify the serving size and number of servings per container.
  • CRead total fat, saturated fat, and trans fat grams.
  • DCheck carbohydrate grams, including fiber and added sugars.
2Short answerMarked by AI

A frozen dinner has 30% DV for saturated fat per serving. According to the %DV guidelines (5% low, 20% high), is this food considered low, moderate, or high in saturated fat? What does this mean for how much of that nutrient you can still eat that day?

Graded on Correct classification and interpretation of %DV threshold · Clear explanation of real-world implication

3Numeric answerChecked instantly

A granola bar contains 6 g of dietary fiber. The daily value for fiber is 28 g. What is the %DV for fiber for this granola bar? (Round to the nearest whole percent and do not include the % sign.)

4Multiple choiceChecked instantly

Which %DV value is considered a LOW source of a nutrient per serving?

  • A5% or less
  • B10%
  • C15%
  • D20% or more

Lesson 46

Added sugars and ingredients

Identifying added sugars under different names, reading ingredient order, and distinguishing added from natural sugars.

10 min3 assessments
  • Added sugars appear under more than 60 different names on ingredient lists.
  • The order of ingredients matters: the first ingredient is the most abundant by weight.
  • Natural sugars (e.g., in fruit, milk) come packaged with fiber, water, or protein, slowing absorption.
  • Added sugars contribute calories without essential nutrients, and high intake is linked to chronic disease.

Reading a label for added sugars

Consider a packaged granola bar. The Nutrition Facts panel shows Added Sugars: 12g. The ingredient list reads:

Ingredients: Whole grain oats, cane sugar, brown rice syrup, almonds, honey, sea salt, soy lecithin, natural flavor.

Here, the added sugars are cane sugar, brown rice syrup, and honey — three different names. The first ingredient is oats (a whole grain), but the very next ingredient is cane sugar. Because the list is ordered by weight, this bar has more cane sugar than any other single ingredient except oats. The brown rice syrup and honey add more sugar further down.

Now check a plain yogurt label: Ingredients: Cultured pasteurized milk, cream, pectin, live active cultures. It has 0g added sugars, and the ingredient list contains no sugar names. The 14g of sugar on the label comes naturally from lactose in milk.

Not all sugars are created equal. Here's how natural sugars and added sugars differ on the factors that matter for your health.

Natural sugars

Source
Found in whole foods (fruit, milk, vegetables)
Accompaniments
Packaged with fiber, water, protein, vitamins
Health impact
Slow absorption, low glycemic load, nutrient-dense
Label names
None — they are not added during processing (e.g., lactose, fructose in fruit)

Best for Everyday energy from whole foods; supports satiety and micronutrient intake.

Added sugars

Source
Added during processing or preparation
Accompaniments
No beneficial accompaniments; just calories
Health impact
Rapid absorption, high glycemic load, contributes to obesity and inflammation
Label names
Over 60 names: cane sugar, high-fructose corn syrup, honey, agave, fruit juice concentrate, etc.

Best for Occasional treats or cooking; should be limited to <10% of daily calories.

Common misconception

“Evaporated cane juice is a natural, less processed sweetener that is better for you than regular sugar.”

The name 'evaporated cane juice' sounds like it comes from a whole plant, and 'juice' suggests it's minimally processed. It's often marketed in health food products.

What is actually true

Evaporated cane juice is chemically identical to table sugar (sucrose) and is just as processed. The body metabolizes it the same way, and it has the same calorie and blood sugar impact. It's simply a marketing term for sugar that has been crystallized from sugarcane juice. The American Heart Association classifies it as an added sugar.

Reference

Common names for added sugars on ingredient lists

Cane sugar

Derived from
Sugarcane
Notes
Plain white sugar, also called sucrose

Brown sugar

Derived from
Sugar cane or beet
Notes
White sugar with molasses

High-fructose corn syrup

Derived from
Corn starch
Notes
Common in soda and processed foods

Honey

Derived from
Bees
Notes
Contains trace nutrients, but still an added sugar

Agave nectar

Derived from
Agave plant
Notes
High in fructose, similar to HFCS

Maple syrup

Derived from
Maple tree sap
Notes
Contains some minerals, but still sugar

Fruit juice concentrate

Derived from
Fruit juice
Notes
Water removed; concentrated sugar

Maltodextrin

Derived from
Corn, rice, potato starch
Notes
Highly processed, mild sweetener

Corn sweetener

Derived from
Corn
Notes
Generic term for corn-based sweeteners

Invert sugar

Derived from
Sugar cane/beet
Notes
Sucrose split into glucose and fructose

If you see any of these in the first three ingredients, the product is likely high in added sugar.

Go deeper

For a deeper dive into the chemistry and health effects of added sugars, read the Wikipedia article.

Check yourself

Test your ability to spot added sugars and understand ingredient lists.

1Multiple choiceChecked instantly

Which of the following is NOT an added sugar?

  • AHigh-fructose corn syrup
  • BLactose
  • CEvaporated cane juice
  • DAgave nectar
2Select all that applyChecked instantly

Select all the names that are added sugars. (There are four correct answers.)

  • ABrown rice syrup
  • BNatural flavor
  • CFruit juice concentrate
  • DMaltodextrin
  • EPectin
  • FInvert sugar
3Short answerMarked by AI

Look at this ingredient list: 'Ingredients: Organic whole wheat flour, honey, palm oil, cocoa powder, natural flavor, baking soda.' Identify which ingredients are added sugars and explain why honey appears second in the list and what that tells you about the product.

Graded on Identifies the added sugar ingredient · Explains the significance of ingredient order · Draws conclusion about the product

Lesson 47

Reading a nutrition study headline without being taken in

You will be able to look at a news headline about a nutrition study and ask the four questions that reveal whether the finding is worth acting on. Covers correlation versus causation, relative versus absolute risk, sample size, and funding sources. Prevents changing your diet every time a new study makes the news.

40 min3 assessments

You've just seen a headline: 'New study finds coffee drinkers live 10 years longer!' Your first instinct might be to buy a bigger mug. But before you change your morning routine, you need to ask four questions that separate a real finding from a misleading one.

Nutrition studies are hard to do. People eat differently every day, remember food poorly, and live for decades — so most studies are observational, not experimental. That means they can show a link, but not prove cause and effect. Headlines, meanwhile, are written to get clicks, not to be accurate.

This lesson gives you a mental checklist. When you see a nutrition headline, you'll work backwards from the claim to the study's real limits — like a mechanic diagnosing why a car won't start. The symptom is the headline. The causes are hidden in the study's design.

Decision tree for evaluating a nutrition study headline

Decide

You're scrolling through news and see this headline: 'Eating chocolate twice a week cuts heart disease risk by 50%, new study finds.' You remember the four questions. Let's work through them.

Your first question: was the study on humans? The article says: 'Researchers surveyed 5,000 adults about their chocolate intake and followed them for 10 years, recording heart attacks.' What do you conclude?

Common misconception

“"If a study found that people who eat X live longer, then eating X will make me live longer."”

Headlines present the finding as a direct cause-and-effect relationship. The study itself often says 'associated with' or 'linked to,' but the news story drops those words. If the data shows a correlation, it's natural to assume one thing causes the other.

What is actually true

Observational studies show correlation, not causation. People who eat X might also exercise more, smoke less, or have higher incomes — any of those could explain the longer life. The only way to prove causation is a randomized controlled trial, which is rare in nutrition because it's hard to control what people eat for years.

  • Observational studies can show association but cannot prove causation — confounding variables are always a possibility.
  • Relative risk reduction (e.g., '50% lower risk') sounds dramatic but may represent a tiny absolute change (e.g., 2% to 1%).
  • Industry-funded studies are more likely to report favorable results; always check the funding source.
  • A single study, no matter how well-done, is not reliable until it has been replicated by independent researchers.
  • The four-question checklist for any headline: was it on humans, what's the effect size (absolute vs. relative), who paid, and is it replicated?
Check yourself

Test your ability to spot misleading nutrition headlines.

1Select all that applyChecked instantly

You see this headline: 'Study finds people who eat breakfast live longer.' Which of the following are valid reasons to be skeptical? (Select all that apply.)

  • APeople who eat breakfast might also have healthier habits overall.
  • BThe study was published in a peer-reviewed journal.
  • CThe study was observational, not a randomized trial.
  • DThe study had a large sample size of 100,000 people.
2Put in orderChecked instantly

When you see a nutrition headline, you should ask questions in a specific order to avoid wasting time. Put these steps in the correct sequence.

  • AIs the finding replicated by independent studies?
  • BWas the study on humans?
  • CWho funded the study?
  • DWhat is the absolute effect size, not just the relative risk?
3Short answerMarked by AI

A headline says: 'New drug cuts heart attack risk by 40%!' The fine print reveals that in the placebo group, 5 out of 1,000 people had a heart attack, while in the drug group, 3 out of 1,000 had one. Explain why the headline is misleading and calculate the absolute risk reduction.

Graded on Identifies relative vs. absolute risk · Calculates absolute risk reduction correctly · Explains why the headline is misleading

Lesson 48

The hierarchy of evidence in nutrition science

You will be able to rank study types from case report to meta-analysis and explain why each has different strengths. Covers observational studies, randomized controlled trials, systematic reviews, and the problem of food frequency questionnaires. Prevents giving equal weight to an Instagram anecdote and a Cochrane review.

25 min3 assessments

A headline says 'Coffee cuts cancer risk by 30%.' Another says 'Butter is back.' Both are based on studies — but the studies are not equal. One might be a single observational study of 50 people who filled out a food questionnaire last year. The other might be a meta-analysis of 20 randomized trials. If you treat them as equally convincing, you will change your diet every Tuesday.

The hierarchy of evidence ranks study designs by how well they eliminate bias and prove cause and effect. It was built over decades because earlier designs kept giving wrong answers — like the idea that hormone replacement therapy prevented heart disease, which a huge RCT later overturned. The hierarchy is not a ladder you must climb; it is a tool for deciding how much to trust a claim.

At the bottom: case reports and expert opinion. One person's story, or one doctor's hunch. Useful for spotting new ideas, useless for proving them.

Above that: observational studies — cohort, case-control, cross-sectional. They watch what people eat and see who gets sick. They can find correlations but cannot prove causation, because people who eat kale also tend to exercise and have higher incomes. The food frequency questionnaire (FFQ) is a notorious weak link: asking what you ate six months ago is asking your memory to lie for you.

Above that: randomized controlled trials (RCTs). You randomly assign people to eat more kale or not. Randomness balances the kale-eaters and the non-kale-eaters on everything except the kale. If the kale group lives longer, you have a strong case that kale caused it.

At the top: systematic reviews and meta-analyses. A systematic review finds every study on a question, judges its quality, and synthesizes the results. A meta-analysis combines the numbers statistically. A Cochrane review is the gold standard — it pre-registers its methods and is updated as new trials appear.

You already know how to read a headline skeptically. Now you know why the study type behind it matters more than the clickbait number in bold.

How it got here
  1. 1940s–1950s

    Case reports and expert opinion dominate

    Nutrition advice came from individual doctors' observations and prominent researchers' beliefs. Problem: one person's experience could be a coincidence, but it shaped national guidelines (e.g., the 'prudent diet' hypothesis based on a handful of patients).

  2. 1950s–1970s

    Large cohort studies arrive

    Studies like the Framingham Heart Study followed thousands of people for decades. Solved the problem of small, cherry-picked samples, but still could not separate diet from lifestyle — people who ate less saturated fat also smoked less.

  3. 1980s

    Randomized controlled trials become standard

    The Women's Health Initiative and other large RCTs tested diet interventions by random assignment. Solved the confounding problem: random allocation balances known and unknown confounders. But RCTs are expensive and hard to run for decades.

  4. 1990s

    Systematic reviews and meta-analyses formalized

    The Cochrane Collaboration was founded in 1993 to systematically gather and appraise all RCTs on a question. Solved the problem of selective citation — cherry-picking the studies that support your view. A meta-analysis can pool data from several small trials to reach a reliable conclusion.

  5. 2000s–present

    Food frequency questionnaires under fire

    Large studies like the EPIC cohort revealed that FFQs produce weak, inconsistent correlations compared to food diaries or biomarkers. Solved nothing — they remain widely used because they are cheap, but the hierarchy now ranks them lower than studies using more precise dietary assessment.

The timeline shows why each design was invented: to fix a flaw in the one before. But the hierarchy is not a strict ladder. A well-conducted cohort study with objective biomarkers can be more trustworthy than a small, poorly randomized trial. The key is to ask: How hard did this study try to eliminate bias?

Here is the practical takeaway for reading nutrition news:

  • Headline based on a case report or expert opinion? Ignore it until better evidence appears.
  • Headline based on one observational study? Treat it as a hint, not a fact. Look for the words 'associated with' — that is the study being honest.
  • Headline based on an RCT? Ask: how many people, how long, and was it double-blind? Nutrition RCTs are rarely double-blind (you know if you are eating kale), so they are still vulnerable to placebo effects.
  • Headline based on a systematic review or meta-analysis? This is the strongest single source. But check if it is a Cochrane review — those are updated. A 2005 meta-analysis on eggs and heart disease is obsolete.

One more trap: the food frequency questionnaire. If a study says 'we asked 100,000 people what they ate last year,' the answer is 'mostly wrong.' FFQs are cheap, so big studies use them, but the measurement error is huge. A study using a week of food diaries or blood biomarkers is more trustworthy even if it is smaller.

Check yourself

Check your understanding of the evidence hierarchy.

1Multiple choiceChecked instantly

A news article reports: 'Study finds people who eat dark chocolate have lower blood pressure.' The study was a cross-sectional survey where participants reported their chocolate intake and had their blood pressure measured once. What is the biggest reason to be skeptical?

  • AThe study did not randomly assign people to eat chocolate or not, so people who eat chocolate may also exercise more or have lower stress.
  • BCross-sectional studies are always wrong.
  • CDark chocolate is expensive, so only rich people eat it.
  • DThe study did not use a food frequency questionnaire.
2Short answerMarked by AI

Why is a meta-analysis of 10 randomized controlled trials considered stronger evidence than a single large RCT? Mention at least one specific advantage of the meta-analysis approach.

Graded on Identifies the advantage of combining multiple trials · Specificity and accuracy

Check yourself
1Put in orderChecked instantly

Arrange these study types from weakest to strongest evidence for proving that a food causes a health outcome.

  • AMeta-analysis of RCTs
  • BCase report
  • CRandomized controlled trial
  • DCohort study using FFQ
  • ESystematic review of cohort studies
  • FCohort study using food diaries

Lesson 49

Correlation vs causation

Why observational studies show association, not cause, and how confounding variables mislead.

10 min3 assessments

Most nutrition studies you see in headlines are observational — researchers watch what people eat and track their health. They find correlations: two things that change together. But a correlation does not mean one causes the other.

A confounding variable is a third factor that influences both the habit and the outcome. For example, a study finds that people who eat more fruit have lower blood pressure. But fruit eaters also tend to exercise more, smoke less, and have higher incomes. Those lifestyle factors — not the fruit — could be driving the lower blood pressure.

Correlation alone can also be reverse causation: maybe lower blood pressure makes people want to eat more fruit, not the other way around. Or it could be pure coincidence. The key question you should ask before acting on any study: What else is different about the people who do this thing?

A confounder (healthy lifestyle) influences both the habit and the outcome, creating a false impression that fruit directly lowers blood pressure.

Analogy

Correlation between an umbrella and rain: seeing someone with an umbrella correlates with rain, but the umbrella does not cause the rain — rain causes the umbrella use. The umbrella is a flag for rain, not the cause.

In nutrition, the confounder is often invisible — like a person's genetics, childhood environment, or overall health mindset — unlike rain, which is plainly visible. The analogy breaks down when the confounder is unmeasured and you mistake the flag for the cause.

Where the analogy breaks down

This analogy breaks down when the confounder is not obvious: in nutrition, the real cause can be hidden (e.g., socioeconomic status affects both supplement use and longevity), whereas rain is directly observable. Also, sometimes the flag itself can be a cause (e.g., folic acid fortification directly reduces birth defects), so correlation *can* be causation in controlled experiments.

Common misconception

“If two things are correlated, one must cause the other.”

We see patterns constantly and our brains are wired to find causal explanations. Many everyday correlations are indeed causal (e.g., turning the key starts the car), so the shortcut often works.

What is actually true

Correlation can be coincidental, due to a third confounding variable, or even reverse causation. For example, ice cream sales and drowning deaths are correlated because both increase in summer — ice cream does not cause drowning. In nutrition, the same trap applies: fruit eaters may live longer, but it's often their overall lifestyle, not the fruit alone.

Decide

You read a headline: 'Eating chocolate linked to lower BMI.' But chocolate is high in calories. How could this be? Work through the steps to find the most likely explanation.

Which of these is the most plausible explanation for the correlation between eating chocolate and lower BMI?

Check yourself

Now test your understanding of correlation vs. causation in nutrition.

1Multiple choiceChecked instantly

A study finds that coffee drinkers have a lower risk of Parkinson's disease. Which statement best interprets this finding?

  • ACoffee prevents Parkinson's disease.
  • BThe correlation could be due to a confounder, like smoking, which is also associated with lower Parkinson's risk.
  • CThe study is worthless because it is observational.
  • DThe finding proves that coffee is beneficial for the brain.
2Short answerMarked by AI

You see a headline: 'People who eat breakfast lose more weight than those who skip breakfast.' List two possible confounders that could explain this correlation, and explain why one of them is plausible.

Graded on Identifies two distinct confounders relevant to weight loss and breakfast. · Explains the plausibility of one confounder with a clear mechanism.

3Short answerMarked by AI

A study shows that taking vitamin C supplements is correlated with shorter cold duration. However, the study was observational. Evaluate whether you would start taking vitamin C based on this evidence. Justify your answer.

Graded on Considers the role of confounding variables in the observational study. · Makes a clear decision and justifies it with reasoning about causation. · Uses the concept of correlation vs causation correctly throughout the answer.

Lesson 50

Relative vs absolute risk

How headlines exaggerate risk by reporting relative instead of absolute numbers; calculating absolute risk.

10 min3 assessments

A headline screams: “New drug cuts heart attack risk by 50%!” That sounds enormous. But what does 50% of what? If the original risk was 2 in 100, a 50% cut brings it to 1 in 100 — an absolute drop of just 1 percentage point. The 50% is the relative risk reduction; the 1% is the absolute risk reduction. Journalists almost always report the relative number because it looks more dramatic. You need the absolute number to know whether the result matters to you.

Relative risk reduction = (risk in control − risk in treatment) ÷ risk in control × 100% Absolute risk reduction = risk in control − risk in treatment

Both use the same two numbers but produce very different impressions.

A study of 10,000 people finds that over 5 years, 2% of the placebo group developed diabetes, while 1.5% of the drug group did. The news says: “Drug reduces diabetes risk by 25%.” Is that claim accurate? What is the absolute risk reduction?

  1. 1

    Risk in control = 2% = 0.02

    The study reports the proportion in the placebo group.

1/4
  • Relative risk reduction compares the change in risk to the original risk; absolute risk reduction is the simple difference.
  • A large relative reduction can hide a tiny absolute reduction when the baseline risk is small.
  • Headlines almost always report relative risk because the number looks bigger.
  • To evaluate a study, always ask: what was the absolute risk in the control group and the treatment group?
  • Absolute risk reduction is measured in percentage points, not percent of the original risk.
Try it

Slide the baseline risk down to 1% and the relative reduction to 50%. The absolute reduction is just 0.5 percentage points. Now slide the baseline up to 10% — the same 50% relative cut now gives 5 percentage points absolute. The headline number stays 50% in both cases, but the real benefit changes dramatically. Discover when a 50% relative reduction is actually a tiny change and when it is substantial.

2.0 %
50 %

Absolute risk reduction

—

This browser cannot run the calculation (Web Workers are unavailable).

Go deeper

Read the Wikipedia entry on relative risk for a deeper mathematical definition and examples from epidemiology.

Check yourself

Check your understanding of relative vs absolute risk.

1Multiple choiceChecked instantly

A study reports: “New supplement reduces the risk of catching a cold by 30%.” In the placebo group, 10% caught a cold; in the supplement group, 7% did. Which statement is true?

  • AThe absolute risk reduction is 30 percentage points.
  • BThe absolute risk reduction is 3 percentage points.
  • CThe relative risk reduction is 3%.
  • DThe supplement reduces your chance of catching a cold from 10% to 3%.
2Numeric answerChecked instantly

In a clinical trial, 4% of the placebo group had a heart attack. The treatment group had 3.2%. What is the absolute risk reduction in percentage points? (Enter a single number, e.g., 0.8)

3Short answerMarked by AI

A headline says: “New drug cuts stroke risk by 40%!” The absolute risk of stroke in the control group was 1% over 5 years. In 2–4 sentences, explain why the headline is misleading and what the absolute risk reduction actually is.

Graded on Identifies the headline as relative risk reduction · Calculates the absolute risk reduction correctly · Explains why the headline is misleading

Lesson 51

Sample size and funding

Why small studies are unreliable, and how industry funding can bias results.

10 min3 assessments

You read a headline: 'New study shows X causes Y!' Before you act on it, two hidden factors decide whether you should trust it: sample size and funding source. A study with 20 participants can show a dramatic effect by pure luck — the odds of a false positive are high. A study funded by the company that sells the product often gets designed, conducted and reported in ways that favour the sponsor. Together, small samples and industry funding make even a statistically significant result unreliable. This node gives you the two quick checks that separate headlines worth ignoring from ones worth reading.

Studies differ in reliability. The table below compares four common study profiles along the axes that matter most for trusting a headline.

Small, industry-funded

Sample size (n)
n < 100
Funding source
Company with a financial stake
Statistical power (ability to detect a true effect)
Very low
Risk of false positive (Type I error)
High (p-values unreliable)
Generalizability to the real world
Very limited; often narrow population

Best for Hypothesis generation, not action

Small, independent

Sample size (n)
n < 100
Funding source
Government / non-profit grant
Statistical power (ability to detect a true effect)
Very low
Risk of false positive (Type I error)
High
Generalizability to the real world
Limited; pilot data

Best for Exploratory research

Large, industry-funded

Sample size (n)
n > 1000
Funding source
Company with a financial stake
Statistical power (ability to detect a true effect)
High
Risk of false positive (Type I error)
Low, but risk of selective reporting or design bias
Generalizability to the real world
Moderate; may still oversell a product

Best for Getting a product approved (be skeptical of claims)

Large, independent

Sample size (n)
n > 1000
Funding source
Government / non-profit grant
Statistical power (ability to detect a true effect)
High
Risk of false positive (Type I error)
Low
Generalizability to the real world
Broad; can apply to general population

Best for Deciding whether to change your diet or habits

Cold remedy study: small and industry-funded vs. large and independent

Small, industry-funded study (n = 30)

  • Participants: 15 treatment (new supplement), 15 placebo.
  • Result: 50% fewer cold symptoms in the treatment group, p = 0.04.
  • Funding: Company that manufactures the supplement.
  • Why it's weak: With only 30 people, a few participants having a mild week can produce a large fake effect. A p = 0.04 means there's still a 4% chance the difference is random. The company may have chosen only the most favourable outcome measure.

Large, independent study (n = 2000)

  • Participants: 1000 treatment, 1000 placebo.
  • Result: No significant difference, p = 0.45.
  • Funding: National Institute of Health.
  • Why it's strong: 2000 participants give stable estimates. The lack of a significant effect is credible. No conflict of interest.

Takeaway: The small study's dramatic headline sells supplements; the large study's boring result tells you the truth.

Common misconception

“If a study reports a p-value less than 0.05, the sample size must have been large enough.”

The p-value threshold (0.05) is widely taught as the mark of a 'significant' result, so a significant p feels like proof of adequate sample size.

What is actually true

A p-value depends on effect size, sample size, and variability. A tiny study of 20 people can easily produce a significant p if the few participants happen to show a large difference (or if the study is biased). A huge study of 10,000 people can produce a significant p for a trivial effect. Sample size must be judged independently — look for the number of participants, not just the p-value.

Decide

You see a headline on your feed: 'New study finds that drinking green tea reduces cancer risk by 40%.' You click through and find the research paper. Your goal: decide whether this headline is worth sharing or ignoring. You have time to check two things: the sample size and the funding source.

First, you look at the sample size. What does the study report?

Go deeper

Effect size is an important concept linked to sample size: a small study can produce a large effect size but with wide confidence intervals, making the estimate unreliable.

Check yourself

Test your ability to evaluate studies based on sample size and funding.

1Multiple choiceChecked instantly

Why is a study with only 20 participants considered unreliable even if it reports a statistically significant result (p = 0.03)?

  • ABecause the researchers probably made a math error.
  • BBecause small samples have high variability; a few extreme participants can produce a large effect by chance.
  • CBecause p-values are meaningless when the sample is small.
  • DBecause a p of 0.03 is actually not significant.
2Select all that applyChecked instantly

Which of the following are signs that a nutrition study's results may be biased by its funding source? (Select all that apply.)

  • AThe study was funded by the company that manufactures the supplement being tested.
  • BThe study was funded by a government health agency.
  • CThe authors are employees of the company that sells the product.
  • DThe authors are professors at a public university.
  • EThe study only reported results for the outcomes that favoured the product, ignoring others.
3Short answerMarked by AI

A headline claims: 'Eating chocolate reduces depression by 30% (study of 30 people, p = 0.04).' Explain in 2–4 sentences why you should not change your diet based on this study. Mention sample size and any other relevant factor.

Graded on Identifies small sample size as a source of unreliability · Considers funding or design issues (can be inferred from context) · Concludes with appropriate skepticism without overstating

Lesson 52

Four questions for headlines

A quick checklist: was it in humans? what was the effect size? who paid? is it replicated?

10 min3 assessments
Steps
0/4

When you see a nutrition headline, run through these four questions in order. Each question catches a different kind of trick. Going out of order lets a misleading claim slip through.

  1. Was it in humans?

    Check the article for the words 'mice', 'rats', 'cells' or 'in vitro'. If the headline says 'coffee reduces heart disease' but the study was on mice, you cannot eat the same way. Animal studies suggest mechanisms; human trials test outcomes.

    News writers often skip the species. If the article doesn't say 'human', assume it wasn't. A headline that seems too specific ('3 cups of coffee lowers risk by 22%') is usually from an animal study.

    You can name the species the study used. If you can't, it's not human.

  2. What was the effect size?

    Look for absolute numbers, not just percentages. 'Reduces risk by 50%' might mean from 2 in 10,000 to 1 in 10,000 — a 0.01% absolute drop. Ask: 'What is the baseline risk, and how many people actually change?'

    Relative risk makes small effects sound huge. If the headline only gives a percentage, it's almost certainly relative risk. The absolute difference is usually hidden in the text.

    You can find the absolute risk difference (e.g., 'from 2% to 1%'). If you can't, the effect is likely trivial.

  3. Who paid for it?

    Scroll to the funding disclosure or conflict-of-interest statement. Studies funded by an industry with a stake in the outcome are more likely to report favourable results. 'Funded by the Almond Board' doesn't mean the study is wrong, but it means you should look harder at the data.

    Funding is often buried in small print at the end of the full paper, not in the news article. If the article doesn't mention funding, search for the original study and check.

    You can state the funding source. If you can't find it, treat the headline with extra caution.

  4. Is it replicated?

    Search for 'meta-analysis' or 'systematic review' on the same topic. One study is a snapshot; dozens of studies pointing the same way is a pattern. Headlines that say 'new study finds' are often about a single paper that hasn't been confirmed.

    A single study can be an outlier or a false positive. Even if it's a well‑done human trial, one result doesn't change established advice. Look for the consensus.

    You can name at least one other study or meta-analysis that supports or contradicts the finding.

Checklist
0/4

Four questions for headlines

Keep this open while you read any nutrition headline. Tick each item when you can answer yes.

Applying the four questions to a headline

Headline: 'Red wine cuts cancer risk by 60%'

1. Was it in humans? The article says 'in mice given the equivalent of two glasses daily'. Answer: No, it was in mice. Stop here — the headline is misleading.

If it had been in humans:

2. Effect size? The article would say 'from 5 in 1,000 to 2 in 1,000' (absolute difference 0.3%). The 60% is relative risk. Answer: The effect is tiny in absolute terms.

3. Who paid? The study was funded by the Wine Institute. Answer: Industry funding — treat with caution.

4. Replicated? A quick search shows no meta‑analysis supports this finding; two other studies found no link. Answer: Not replicated.

Verdict: The headline is based on an animal study, exaggerates the effect, has industry funding, and isn't confirmed. Ignore it.

Go deeper

Betteridge's law of headlines says 'Any headline that ends in a question mark can be answered by the word no.' It's a quick heuristic — if the headline asks a question, the answer is probably no. Use it alongside the four questions.

Check yourself

Test your ability to apply the four questions.

1Put in orderChecked instantly

Put the four questions for evaluating a nutrition headline in the correct order as they should be asked.

  • AWas it in humans?
  • BIs it replicated?
  • CWhat was the effect size?
  • DWho paid for it?
2Short answerMarked by AI

Headline: 'Eating dark chocolate slashes blood pressure by 20%'. The article says: 'The study tested 30 people, funded by a chocolate company, and the reduction was from 140/90 to 138/88 mmHg.' Using the four questions, identify what is misleading about this headline. Write your answer in 2-4 sentences.

Graded on Identifies the exaggeration of effect size (relative vs absolute) · Identifies the funding source as a potential bias · Mentions replication or lack thereof

Project

Evaluate a real nutrition headline

Find a real nutrition headline from a news website (e.g., BBC, CNN, NYT, or a local paper). Apply the four questions to it. Write a short report (200-300 words) that:

  • States the headline and the source.
  • Answers each of the four questions with evidence from the article.
  • Concludes whether the headline is trustworthy or misleading.

Deliverable: A text report that would help a friend decide whether to act on the headline.

Deliverables

  • 01Headline and source quoted.
  • 02Four questions answered with specific evidence (e.g., 'The study was on mice, not humans' or 'Funded by the Dairy Council').
  • 03A clear verdict (trustworthy / misleading / uncertain).
ProjectMarked by AI

Submit your report as described in the project brief.

Graded on Answers the 'was it in humans?' question with evidence · Identifies the effect size and distinguishes relative vs absolute · Identifies the funding source and discusses bias · Assesses replication and gives a verdict

Lesson 53

Dietary patterns: Mediterranean, plant-based, and low-carb

You will be able to compare three major dietary patterns by their macronutrient profiles, food emphases, and the evidence for their health outcomes. Covers the Mediterranean diet, well-formulated plant-based diets, and carbohydrate-restricted diets. Prevents the belief that there is one optimal diet for everyone.

35 min3 assessments

You've learned to spot a misleading nutrition headline. Now you face a harder question: which eating pattern should you actually follow? The answer isn't one-size-fits-all — the best diet for someone with insulin resistance and visceral fat is not the same as the best diet for someone trying to maintain heart health over decades.

This lesson compares three patterns backed by the strongest evidence: the Mediterranean diet, a well-formulated plant-based diet, and a carbohydrate-restricted diet. Each shifts your macronutrient ratios and food choices in a different direction. By the end, you'll be able to match a pattern to a person's goals, constraints, and metabolic context — not because one diet "wins," but because each wins in a specific situation.

The three patterns differ along five axes that determine their effects:

Mediterranean

Carbohydrate (% of energy)
40–50%
Fat (% of energy)
35–40%
Protein (% of energy)
15–20%
Primary fat source
Olive oil, fish, nuts
Typical fibre (g/day)
25–35

Best for A person with elevated LDL, normal triglycerides, and a family history of heart disease who wants a sustainable long-term pattern.

Well-formulated plant-based

Carbohydrate (% of energy)
50–65%
Fat (% of energy)
20–30%
Protein (% of energy)
12–18%
Primary fat source
Nuts, seeds, avocados, plant oils
Typical fibre (g/day)
35–50

Best for Someone who values environmental sustainability, has normal kidney function, and needs to lower LDL without pharmaceutical help.

Carbohydrate-restricted (<50 g/day net)

Carbohydrate (% of energy)
5–15%
Fat (% of energy)
55–70%
Protein (% of energy)
20–30%
Primary fat source
Animal fats, olive oil, coconut oil
Typical fibre (g/day)
20–30

Best for A person with type 2 diabetes, high triglycerides, or metabolic syndrome who needs rapid improvement in glycemic control and triglyceride levels.

Choosing a pattern for three real people

Person A: 55-year-old woman, LDL 4.1 mmol/L, HDL 1.2, triglycerides 1.3. No diabetes. She wants to eat with her family without separate meals. → Mediterranean fits: moderate carbs keep triglycerides low, olive oil and fish lower LDL, and the pattern is easy to cook for others.

Person B: 42-year-old man, HbA1c 8.5%, triglycerides 5.1 mmol/L, BMI 33. Failed metformin monotherapy. → Carbohydrate-restricted fits: dropping net carbs below 50 g/day directly reduces hepatic de novo lipogenesis, which is what drives his high triglycerides. A network meta-analysis of 121 trials showed low-carb diets produce the largest improvements in HbA1c at 6 months.

Person C: 30-year-old endurance athlete, normal lipids, who wants to lower LDL from 3.8 to <3.0 mmol/L without medication, and also wants to align with her environmental values. → Well-formulated plant-based fits: high fibre pulls down LDL through increased bile acid excretion, and she can maintain glycogen stores for performance.

Common misconception

“"Low-carb is the same as keto — you eat mostly meat and butter and no vegetables."”

Popular media and influencers often conflate all low-carb approaches with a very high-fat, very low-protein, bacon-and-butter ketogenic diet. Many beginners on low-carb do initially emphasize fatty meats and reduce vegetables, creating that impression.

What is actually true

A well-formulated carbohydrate-restricted diet (<50 g/day net carbs) emphasizes non-starchy vegetables, adequate protein (20–30% of energy), and fat from sources like olive oil, avocado, and nuts — not unlimited saturated fat. The best long-term outcomes come from carbohydrate restriction combined with high vegetable intake and unsaturated fats. Eliminating vegetables while on low-carb worsens micronutrient status and fibre intake.

Reference

Key nutrients of concern and how each pattern handles them

Vitamin B12

Mediterranean
Adequate from fish/meat
Well-formulated plant-based
Requires supplement or fortified foods
Carbohydrate-restricted
Adequate from animal products

Iron (heme vs non-heme)

Mediterranean
Heme from meat/fish; well absorbed
Well-formulated plant-based
Non-heme only; needs vitamin C co-consumption
Carbohydrate-restricted
Heme from meat; well absorbed

Fibre (g/day)

Mediterranean
25–35 from whole grains, legumes, vegetables
Well-formulated plant-based
35–50 from legumes, whole grains, vegetables
Carbohydrate-restricted
20–30 from non-starchy vegetables, nuts, seeds; may need supplement

Omega-3 (EPA/DHA)

Mediterranean
Adequate from oily fish 2×/week
Well-formulated plant-based
May need algal DHA supplement
Carbohydrate-restricted
Adequate from fish/seafood; but less emphasis on fish may reduce intake

Any pattern can be nutrient-adequate with planning. The risks shown here are the ones that appear most often in practice when the pattern is followed poorly.

Check yourself

Check your understanding of choosing a dietary pattern.

1Select all that applyChecked instantly

A 60-year-old woman has HbA1c 7.2% (type 2 diabetes), triglycerides 4.8 mmol/L, LDL 2.1 mmol/L (acceptable), and BMI 31. She wants to improve her blood sugar without adding medication. Which two dietary patterns are most likely to help her? (Select two.)

  • AMediterranean diet
  • BWell-formulated plant-based diet
  • CCarbohydrate-restricted diet (<50 g/day net)
  • DStandard low-fat diet (30% fat, 55–60% carbs)
2Short answerMarked by AI

A healthy 35-year-old man wants to lower his LDL from 3.9 to below 3.0 mmol/L. He has normal triglycerides (1.2 mmol/L), no diabetes, and enjoys cooking. He also wants to reduce his environmental footprint. Recommend one of the three patterns discussed and justify your choice in 2–4 sentences, naming at least one mechanism by which the pattern lowers LDL.

Graded on Names one of the three patterns specifically · Justifies choice with a mechanism · Considers the person's context (LDL only, normal TG, environmental goal)

3Multiple choiceChecked instantly

Which dietary pattern typically provides the highest fibre intake per day?

  • AMediterranean diet
  • BWell-formulated plant-based diet
  • CCarbohydrate-restricted diet (<50 g/day net)
  • DStandard Western diet

Lesson 54

Mediterranean diet

Emphasis on olive oil, fish, vegetables, whole grains; evidence for heart health and longevity.

15 min4 assessments

The Mediterranean diet is not a single meal plan but a pattern of eating based on the traditional cuisines of Greece, Italy, Spain, and other countries bordering the Mediterranean Sea. You already know it as one of three major dietary patterns — here you'll learn the specific foods, the evidence for heart health and longevity, and the practical takeaways that distinguish it from a generic 'healthy diet.'

What makes it distinct is not just eating vegetables — most diets recommend those — but the consistent use of olive oil as the primary fat, regular fish intake (twice a week is a common benchmark), whole grains at every meal, and a low intake of red meat and processed foods. It also allows moderate consumption of red wine with meals, a feature that often surprises people.

Reference

Mediterranean Diet: What to Eat and Limit

Olive oil

What to Eat / Frequency
Primary cooking oil; dressings; daily
What to Limit / Avoid
Butter, margarine, coconut oil
Key Benefit
Rich in monounsaturated fats and polyphenols; linked to lower LDL

Vegetables

What to Eat / Frequency
At least 2 servings per meal; variety
What to Limit / Avoid
None
Key Benefit
Fiber, vitamins, antioxidants; high intake associated with reduced CVD risk

Fruits

What to Eat / Frequency
Fresh fruit for dessert; daily
What to Limit / Avoid
Sugary desserts, fruit juices
Key Benefit
Natural sugars with fiber; flavonoids support vascular health

Whole grains

What to Eat / Frequency
Bread, pasta, rice – whole grain versions at every meal
What to Limit / Avoid
Refined white flour products
Key Benefit
Sustained energy; lower glycemic response

Fish and seafood

What to Eat / Frequency
At least 2 servings per week; fatty fish (salmon, sardines) preferred
What to Limit / Avoid
Fried fish, farmed tilapia (low omega-3)
Key Benefit
Omega-3 fatty acids reduce triglycerides and inflammation

Legumes and nuts

What to Eat / Frequency
Several times per week; nuts as snacks
What to Limit / Avoid
Salted or candied nuts
Key Benefit
Plant protein; nuts provide vitamin E and magnesium

Red meat

What to Eat / Frequency
Rarely; lean cuts in small amounts
What to Limit / Avoid
Processed meats (sausage, bacon), fatty cuts
Key Benefit
Lower saturated fat intake when replaced

Dairy

What to Eat / Frequency
Moderate: yogurt, cheese in small amounts
What to Limit / Avoid
Full-fat milk, cream, sweetened yogurt
Key Benefit
Calcium without excess saturated fat

Red wine

What to Eat / Frequency
1 glass per day for women, 2 for men – with meals
What to Limit / Avoid
Binge drinking, spirits
Key Benefit
Resveratrol in moderation; alcohol is not mandatory

Herbs and spices

What to Eat / Frequency
Used liberally instead of salt
What to Limit / Avoid
Excessive salt
Key Benefit
Flavor without sodium; antimicrobial properties

This table reflects traditional Mediterranean patterns as studied in the PREDIMED and Lyon Diet Heart trials. Actual intake varies by region.

Practice
0/10 known
1 / 10
Go deeper

Read for historical context, regional variations, and the full list of foods beyond the table.

Check yourself

Check your understanding of the Mediterranean diet.

1Multiple choiceChecked instantly

A person claims that the Mediterranean diet is essentially a low-fat diet because it emphasizes vegetables and whole grains. Which statement best corrects this claim?

  • AThe diet actually has no specific recommendation on fat intake; it's about food choices.
  • BThe diet includes significant fat from olive oil, nuts, and fish, making it moderate-to-high in fat (35-40% of calories).
  • CThe traditional Mediterranean diet is indeed low in fat because olive oil is low in saturated fat.
  • DThe diet limits all fats except those from fish, so total fat is low.
2Select all that applyChecked instantly

Which three of the following are core food groups of the Mediterranean diet, as supported by major clinical trials? (Select exactly three.)

  • AOlive oil
  • BButter
  • CFish and seafood
  • DLegumes and nuts
  • EProcessed meats
  • FRefined grains
3Fill the blanksChecked instantly
4Short answerMarked by AI

Evaluate the following claim: "The Mediterranean diet is effective simply because it contains a lot of vegetables." In 2-4 sentences, explain why this claim is incomplete by naming at least two other components that are considered essential to the diet's health effects.

Graded on Identifies two essential components beyond vegetables · Clarity and correctness of evaluation

Lesson 55

Plant-based diets

Vegan and vegetarian patterns, ensuring adequate protein, B12, iron, and omega-3s.

15 min3 assessments

A well-planned plant-based diet (vegan or vegetarian) can meet all your nutritional needs, but it requires attention to a few nutrients that are scarce or absent in plant foods. The key challenges are:

  • Vitamin B12 – Not naturally found in any plant food. You must get it from fortified foods (nutritional yeast, plant milks, breakfast cereals) or a supplement. The RDA is 2.4 mcg/day.
  • Iron – Plant foods contain non-heme iron, which is less absorbable than the heme iron in meat. Boost absorption by pairing iron-rich foods (lentils, spinach, fortified cereals) with vitamin C (citrus, bell peppers, tomatoes).
  • Omega-3 fatty acids – Plant sources provide ALA (flaxseeds, chia, walnuts), but conversion to the active forms DHA and EPA is inefficient (only about 5–10%). Consider an algae-based DHA supplement.
  • Protein – A varied diet of legumes, soy, whole grains, nuts, and seeds provides all essential amino acids. The old idea of “protein complementing” at every meal is unnecessary if you eat a variety throughout the day.
  • Calcium and Zinc – Choose fortified plant milks (calcium), tofu made with calcium sulfate, and low-oxalate greens (kale, bok choy). For zinc, soak or sprout beans and grains to reduce phytates that block absorption.

With these adjustments, a plant-based diet can be nutritionally complete and linked to lower risks of heart disease, type 2 diabetes, and certain cancers.

Reference

Key Nutrients in Plant-Based Diets

Protein

Key Plant Sources
Legumes, tofu, tempeh, seitan, quinoa, nuts, seeds
Absorption / Conversion Notes
All essential amino acids available from a varied diet
Special Considerations
Ensure adequate calorie intake to meet protein needs

Vitamin B12

Key Plant Sources
Fortified foods (nutritional yeast, plant milks, cereals), supplements
Absorption / Conversion Notes
Not naturally present in plants
Special Considerations
Mandatory supplement or regular fortified foods; deficiency can cause neurological damage

Iron

Key Plant Sources
Lentils, chickpeas, spinach, fortified cereals, pumpkin seeds
Absorption / Conversion Notes
Non-heme iron; absorption 2–20% vs heme 15–35%
Special Considerations
Pair with vitamin C (e.g., squeeze lemon on lentils); avoid tea/coffee with meals

Omega-3s (DHA/EPA)

Key Plant Sources
Flaxseeds, chia seeds, walnuts, algae oil
Absorption / Conversion Notes
ALA converts to DHA/EPA at ~5–10% efficiency
Special Considerations
Consider algae-based DHA supplement (200–300 mg/day)

Calcium

Key Plant Sources
Fortified plant milks, tofu (calcium-set), kale, bok choy, almonds
Absorption / Conversion Notes
Oxalates in spinach and Swiss chard reduce absorption
Special Considerations
Choose low-oxalate greens; aim for 1000 mg/day from fortified sources

Zinc

Key Plant Sources
Beans, chickpeas, cashews, hemp seeds, whole grains
Absorption / Conversion Notes
Phytates in grains/legumes inhibit absorption
Special Considerations
Soak, sprout, or ferment to reduce phytates; include zinc-rich foods daily

Use this table to plan meals and check if you are covering these nutrients. The RDA values for adults are: B12 2.4 µg, iron 8–18 mg, calcium 1000 mg, zinc 8–11 mg.

Practice
0/8 known
1 / 8
Go deeper

For deeper dives into plant nutrients and dietary patterns, consult these Wikipedia articles.

Check yourself

Test your understanding of plant-based nutrition.

1Multiple choiceChecked instantly

A friend starts a vegan diet and is worried about getting enough protein. Which of the following is the best advice?

  • AEat only quinoa and soy for protein.
  • BCombine grains and legumes at every meal.
  • CEat a variety of plant proteins throughout the day; you'll get all essential amino acids.
  • DTake a protein supplement daily.
2Fill the blanksChecked instantly
3Select all that applyChecked instantly

Which of the following are good plant sources of iron? (Select all that apply)

  • ALentils
  • BSpinach
  • CDairy milk
  • DFortified breakfast cereals
  • EChicken breast

Lesson 56

Low-carb diets

Ketogenic and low-carb approaches, metabolic effects, and considerations for sustainability.

15 min3 assessments

You’ve seen the hype: low-carb diets help you lose weight fast, but are they safe? The real question is what happens inside your body when you drastically cut carbs. Unlike the Mediterranean or plant‑based patterns you’ve already compared, a low‑carb diet forces your metabolism into a different fuel‑burning state.

When carbohydrate intake drops below roughly 130 g per day (a “standard low‑carb” level), your body first depletes its glycogen stores — the glucose stored in your liver and muscles. Each gram of glycogen is stored with about 3–4 g of water, so the rapid drop on the scale in the first week is mostly water loss, not fat loss. Once glycogen runs low, the liver begins converting fatty acids into ketone bodies — acetoacetate, beta‑hydroxybutyrate, and acetone. When ketone levels rise high enough (below about 50 g carb per day), the body enters nutritional ketosis, a state where the brain can derive up to 70 % of its energy from ketones instead of glucose.

This metabolic shift has real clinical effects: triglycerides and HDL cholesterol often improve, and some people report better appetite control. But it also carries risks. Without careful planning, low‑carb diets can be low in fiber, potassium, and magnesium, leading to headaches, fatigue, and constipation — the “keto flu.” Long‑term adherence is hard because it eliminates entire food groups (grains, legumes, many fruits) and makes social eating awkward.

The bottom line: low‑carb isn’t magic and isn’t dangerous for most people when done properly. It’s one tool in the toolbox, and understanding how it works lets you evaluate any diet claim — not just the ones about bacon and butter.

  • A standard low‑carb diet restricts carbs to 50–130 g/day; a ketogenic diet goes below 50 g/day.
  • In ketosis, the liver turns fatty acids into ketone bodies that the brain and muscles can use as fuel.
  • Initial rapid weight loss on low‑carb diets is mostly water from glycogen depletion, not fat.
  • After one year, weight‑loss differences between low‑carb and low‑fat diets are typically small (1–3 kg).
  • Low‑carb diets can improve triglycerides and HDL cholesterol but may raise LDL cholesterol in some individuals.
  • Sustainability is limited by dietary restrictions, social inconvenience, and risk of nutrient deficiencies if unplanned.
Reference

Low‑carb and ketogenic diet approaches

Modified Atkins

Carbs per day
10–20 g
Protein (% kcal)
25–35%
Fat (% kcal)
60–70%
Key feature
Used for epilepsy; stricter carb limit
Typical foods
Meat, eggs, cheese, oils, non‑starchy vegetables

Very low‑carb / ketogenic

Carbs per day
<50 g
Protein (% kcal)
20–25%
Fat (% kcal)
70–80%
Key feature
Nutritional ketosis
Typical foods
Meat, eggs, cheese, oils, leafy greens, avocado

Standard low‑carb

Carbs per day
50–130 g
Protein (% kcal)
25–30%
Fat (% kcal)
45–60%
Key feature
Mild carb restriction
Typical foods
Meat, eggs, cheese, oil, legumes, berries, full‑fat dairy

Low‑carb high‑fat (LCHF)

Carbs per day
<130 g
Protein (% kcal)
20–25%
Fat (% kcal)
55–65%
Key feature
Flexible; emphasizes whole foods
Typical foods
Meat, fish, eggs, dairy, vegetables, nuts, seeds

Sorted from most to least restrictive by carbohydrate limit.

Practice
0/8 known
1 / 8
Go deeper

Use this reference to explore a wide range of named diets, including variants of low‑carb and ketogenic approaches.

Check yourself

Check your understanding of low‑carb diets.

1Multiple choiceChecked instantly

Which of the following best describes the primary metabolic fuel used by the brain during deep nutritional ketosis?

  • AGlycogen
  • BFree fatty acids
  • CKetone bodies
  • DAmino acids
2Select all that applyChecked instantly

Which of the following are true about the initial weight loss on a low‑carb diet? Select all that apply.

  • AIt is mostly water weight from glycogen depletion.
  • BIt indicates a permanent shift in metabolic rate.
  • CIt is often more rapid than fat loss from a low‑fat diet in the first few weeks.
  • DIt continues at the same rate indefinitely.
  • EIt is caused by loss of muscle mass.
3Fill the blanksChecked instantly

Lesson 57

Comparing patterns

Macronutrient profiles, health outcomes, and suitability for different goals and preferences.

10 min3 assessments

You already know the three major patterns — Mediterranean, well-formulated low-carb, and whole-food plant-based. Now you need to pick one. The mistake is asking which is 'best' in general. The right question is: best for whom, under what conditions, and measured by what outcome?

This node gives you the axes that actually decide the choice: macronutrient profile, satiety, and the evidence for specific goals like weight loss, diabetes management, and longevity. You'll leave able to match a pattern to a person's biology and preferences.

The table below compares the three patterns on the axes that matter for real-world decisions. Each row is a dimension; the 'best for' row tells you when to choose that pattern over the others.

Mediterranean

Carbohydrate % of total calories
40–50%
Fat % of total calories
30–40% (mostly monounsaturated)
Protein % of total calories
15–20%
Primary food emphasis
Olive oil, fish, legumes, whole grains, vegetables, moderate wine
Satiety and hunger control
Moderate — fibre slows digestion, but fat can be calorie-dense
Strength of evidence for weight loss (>6 months)
Strong — many RCTs and observational studies show 3–5 kg sustained loss

Best for A person who wants long-term heart health, enjoys shared meals, and has no urgent need to reverse diabetes or lose weight rapidly.

Well-formulated low-carb

Carbohydrate % of total calories
5–20% (<50g net carbs/day)
Fat % of total calories
60–70% (emphasis on unsaturated and saturated in balance)
Protein % of total calories
20–30%
Primary food emphasis
Non-starchy vegetables, meat, poultry, fish, eggs, nuts, seeds, healthy oils; avoids grains, legumes, sugars, most fruits
Satiety and hunger control
High — protein and fat suppress hunger hormones, spontaneous calorie reduction
Strength of evidence for weight loss (>6 months)
Strong — multiple RCTs show greater weight loss than low-fat at 6 months, equal at 12 months

Best for A person with type 2 diabetes, insulin resistance, or metabolic syndrome who needs rapid weight loss and blood sugar control.

Whole-food plant-based

Carbohydrate % of total calories
70–80%
Fat % of total calories
10–15% (very low, mostly polyunsaturated)
Protein % of total calories
10–15%
Primary food emphasis
Vegetables, fruits, legumes, whole grains, nuts, seeds; excludes all animal products
Satiety and hunger control
Moderate-to-high — high fibre and water content, but low fat can lead to hunger if not enough volume
Strength of evidence for weight loss (>6 months)
Moderate — calorie density is low, but adherence can be challenging; short-term weight loss comparable to Mediterranean

Best for A person who prioritizes environmental sustainability, wants to avoid animal products, and is willing to plan for B12, iron, and omega-3s.

Choosing a pattern for a person with type 2 diabetes and high triglycerides

Scenario: 52-year-old woman, diagnosed with type 2 diabetes two years ago, HbA1c 7.8%, fasting triglycerides 3.2 mmol/L, BMI 32. She has tried the Mediterranean diet but lost only 2 kg in six months and her HbA1c stayed at 7.5%. She is motivated to try something new.

Analysis:

  1. 1.Her primary goal is to lower blood glucose and triglycerides, ideally to reduce or eliminate medication.
  2. 2.Mediterranean already failed to produce significant change.
  3. 3.Low-carb diets are proven to lower triglycerides and HbA1c more rapidly than low-fat diets in the short term (Virta Health study, 2019: 60% of patients reversed diabetes at 1 year).
  4. 4.Whole-food plant-based could work, but it is high in carbohydrates (70–80%), which may not lower triglycerides as effectively; she would need to emphasize low-glycemic carbs and be careful with portions.

Decision: Well-formulated low-carb is the best fit. Her diet would shift to ~40g net carbs per day, with emphasis on non-starchy vegetables, healthy fats (olive oil, avocado), and moderate protein. Expected outcome: 5–10% weight loss in 3 months, HbA1c drop to 6.5% or lower, triglycerides normalised within 6 weeks.

Why this is not the general answer: If she had normal triglycerides and a family history of heart disease, Mediterranean might be better despite slower weight loss, because its longevity evidence is stronger.

  • The Mediterranean pattern has the strongest evidence for reducing all-cause mortality and cardiovascular disease in the general population.
  • Well-formulated low-carb is the most effective pattern for reversing type 2 diabetes and rapidly lowering triglycerides.
  • Whole-food plant-based requires careful planning for vitamin B12, iron, and omega-3s, but is associated with lower all-cause mortality in large observational studies.
  • The satiety advantage of low-carb (protein and fat) leads to spontaneous calorie reduction, making weight loss easier without conscious restriction.
  • No single pattern is 'best' — the choice depends on the person's metabolic health, preferences, and willingness to adhere long-term.
Common misconception

“A low-carb diet is high in saturated fat and therefore bad for heart health.”

Many low-carb advocates recommend eating bacon, butter, and red meat, which are high in saturated fat. Public health guidelines have long warned that saturated fat raises LDL cholesterol and increases heart disease risk.

What is actually true

Well-formulated low-carb emphasises unsaturated fats (olive oil, avocado, nuts) and limits processed meats. The diet's effect on heart disease risk is more nuanced: while LDL cholesterol may increase in some individuals, triglycerides drop significantly, HDL rises, and LDL particle size shifts to a less atherogenic pattern. Multiple long-term observational studies show no increased risk of heart disease or mortality among people on low-carb diets, and some show reduced risk when the diet is plant-based and low in processed foods.

Check yourself

Check your ability to match patterns to people.

1Multiple choiceChecked instantly

A 45-year-old sedentary office worker, with normal blood lipids and blood glucose, BMI 24, wants to reduce her long-term risk of heart disease and cancer. She enjoys cooking with family and having a glass of wine with dinner. Which dietary pattern is most appropriate for her?

  • AMediterranean diet
  • BWell-formulated low-carb diet
  • CWhole-food plant-based diet
  • DVery low-fat (Pritikin) diet
2Select all that applyChecked instantly

Which of the following are characteristics of a well-formulated low-carb pattern? Select all that apply.

  • AHigh intake of non-starchy vegetables
  • BEmphasis on lean meats and unsaturated fats
  • CRestriction of grains to less than 50g net carbs per day
  • DInclusion of legumes and whole grains as staple foods
  • EHigh intake of red meat and processed meats
  • FPrioritizes healthy fats like avocado, nuts, and olive oil
3Short answerMarked by AI

Analyze the nutrition label below for a can of sardines in olive oil. The label shows: Servings per container 2; Calories per serving 180; Total Fat 12g (Saturated Fat 2g); Cholesterol 60mg; Sodium 250mg; Total Carbohydrate 0g; Protein 18g. Which dietary pattern does this food best align with? Explain your reasoning in 2–4 sentences, referencing the macronutrient profile and the typical food list of that pattern.

Graded on Identifies the correct pattern and names it · Justifies with specific macronutrient and food details from the label

Lesson 58

Capstone: build and defend a day of eating

You will design a full day of meals for a specific goal, calculate its energy and macronutrient totals, and defend your choices using the principles from the course. Covers meal planning, label data, nutrient timing, and justifying choices with evidence. Prevents the habit of following a meal plan without understanding why it works.

60 min3 assessments
  • Total Daily Energy Expenditure (TDEE) is estimated with the Mifflin-St Jeor equation plus an activity factor; it is the starting point for any plan.
  • For fat loss, aim for a 300–500 kcal deficit while keeping protein at 1.6–2.2 g per kg of body weight to preserve lean mass.
  • Protein should be spread across at least three meals to maximise muscle protein synthesis each day.
  • Carbohydrate and fat fill the remaining calories after protein—prioritise whole grains, vegetables, fruit, and healthy fats for micronutrient density.
  • Nutrient density means choosing foods high in vitamins and minerals per calorie; this matters most when calories are restricted.
  • Evidence hierarchy ranks systematic reviews of randomised trials above single observational studies; rely on the best available evidence when justifying choices.
Project

Design a Day of Eating for a Specific Goal

Your client is a 25-year-old woman, 165 cm tall, 65 kg, with a sedentary job but who walks 30 min daily (PAL 1.375). Her goal is fat loss: a 500 kcal/day deficit. Using the Mifflin-St Jeor equation, her BMR is approx 1400 kcal; TDEE = 1925 kcal; target = 1425 kcal.

Your task:

  1. 1.Choose a dietary pattern (Mediterranean, balanced, or low-carb) that aligns with her goal.
  2. 2.Design a full day of eating (breakfast, lunch, dinner, and two snacks) with specific foods and quantities (grams or cups).
  3. 3.Calculate the total calories and macronutrients (protein, carb, fat) for each meal and for the day.
  4. 4.Write a justification paragraph (150–250 words) covering: why the energy deficit is appropriate, how protein is distributed and why, what food choices support nutrient density, and one piece of evidence (from the course) that supports your approach.

Deliverables:

  • A table showing each meal with foods, quantities, and macro breakdown.
  • A line stating total daily calories and grams of protein, carb, fat.
  • A justification paragraph.

Submit your plan through the assignment tool.

Deliverables

  • 01Table of meals (breakfast, lunch, dinner, 2 snacks) with foods, quantities, and macros per meal
  • 02Total daily calories and macronutrient grams
  • 03Justification paragraph (150–250 words)
ProjectMarked by AI

Upload your day-of-eating plan for the client described above. Include a table with foods, quantities, and macros, the total daily calories and macros, and a justification paragraph.

Graded on Energy adherence · Macronutrient distribution · Protein timing · Justification quality

Checklist
0/7

Before Submitting Your Meal Plan

Review each item before submitting. A plan that fails any of these checks is likely to need revision.

Check yourself
1EssayMarked by AI

Write a short essay (200–300 words) explaining how your meal plan supports the client's fat-loss goal and adheres to evidence-based nutrition principles. Cover: 1) how your plan creates the appropriate energy deficit, 2) why your macronutrient distribution (especially protein) is set as it is, 3) how your food choices promote nutrient density despite the reduced calorie intake, and 4) one specific piece of evidence from the course that supports your approach. Use the same client as in the project brief.

Graded on Energy deficit explanation · Macronutrient justification · Use of evidence

2Short answerMarked by AI

Calculate the approximate TDEE for a 30-year-old man who weighs 80 kg, is 180 cm tall, and exercises 3–4 days per week (moderate activity, PAL 1.55). Use the Mifflin-St Jeor equation: BMR = (10 × weight in kg) + (6.25 × height in cm) – (5 × age in years) + 5. Show your steps and state the final TDEE in kcal.

Graded on Correct formula and activity factor · Final numeric answer accuracy

For you · never graded

What was the most challenging part of designing this meal plan? What would you do differently next time, and what principle from the course would you apply more strongly?

Lesson 59

Setting a nutrition goal

Defining a specific goal (weight loss, muscle gain, maintenance) and calculating energy and macronutrient targets.

15 min3 assessments

You already know how to build a day of meals. Now you need a target — a specific number of calories and grams of each macronutrient that fits your goal. Every nutrition goal starts with energy balance: calories in versus calories out.

Total Daily Energy Expenditure (TDEE) is what you burn in a day: your Basal Metabolic Rate (BMR — the energy your body needs at rest) plus the energy used for activity and digestion. Your goal decides whether you eat above TDEE (surplus → muscle gain), below TDEE (deficit → fat loss), or at TDEE (maintain).

The most common equation for BMR is the Mifflin-St Jeor formula:

  • Men: 10 × weight(kg) + 6.25 × height(cm) – 5 × age(y) + 5
  • Women: 10 × weight(kg) + 6.25 × height(cm) – 5 × age(y) – 161

Multiply BMR by an activity factor: 1.2 (sedentary), 1.375 (light), 1.55 (moderate), 1.725 (active), 1.9 (very active). The result is your TDEE.

Once you have TDEE, adjust for your goal:

  • Weight loss: subtract 300–500 kcal (lose ~0.3–0.5 kg per week). Never go below your BMR.
  • Muscle gain: add 300–500 kcal (gain ~0.3–0.5 kg per week).
  • Maintenance: eat at TDEE.

Finally, split the target calories into macronutrients. A common starting point:

  • Protein: 1.6–2.2 g per kg of body weight (higher for weight loss or muscle gain).
  • Fat: 0.5–0.8 g per kg, or 20–35% of total calories.
  • Carbs: the remaining calories.

Protein and carbs supply 4 kcal per gram; fat supplies 9 kcal per gram.

Reference

Macronutrient ranges by goal

Weight loss

Calorie adjustment from TDEE
-300 to -500 kcal
Protein (% of total kcal)
30–35%
Fat (% of total kcal)
20–25%
Carb (% of total kcal)
40–50%

Muscle gain

Calorie adjustment from TDEE
+300 to +500 kcal
Protein (% of total kcal)
25–30%
Fat (% of total kcal)
20–25%
Carb (% of total kcal)
45–55%

Maintenance

Calorie adjustment from TDEE
0 kcal
Protein (% of total kcal)
15–20%
Fat (% of total kcal)
20–30%
Carb (% of total kcal)
50–65%

Percentages are approximate; adjust based on individual tolerance and performance.

  • TDEE = BMR × activity factor, where BMR is calculated from weight, height, age, and sex using the Mifflin-St Jeor equation.
  • For weight loss, create a deficit of 300–500 kcal/day from TDEE; for weight gain, a surplus of 300–500 kcal/day.
  • Never set your calorie target below your BMR — it risks metabolic slowdown and nutrient deficiency.
  • Protein needs are based on body weight (1.6–2.2 g/kg) rather than a percentage; higher for muscle gain or preservation during loss.
  • After setting protein and fat, fill the remaining calories with carbohydrates.

Sarah (female, 30 years old, 65 kg, 165 cm) exercises moderately 3–5 days per week. Her goal is to lose 0.5 kg per week (a deficit of ~500 kcal/day). Calculate her calorie target and macronutrient grams.

  1. 1

    BMR = 10 × 65 + 6.25 × 165 – 5 × 30 – 161

    The Mifflin-St Jeor formula for women: 10×weight (kg) + 6.25×height (cm) – 5×age (y) – 161.

1/7
Check yourself

Test your ability to calculate and interpret nutrition goals.

1Numeric answerChecked instantly

A 30-year-old woman weighs 70 kg and is 170 cm tall. She exercises moderately (activity factor 1.55). Using the Mifflin-St Jeor formula (BMR = 10×weight + 6.25×height – 5×age – 161), calculate her TDEE. Enter your answer in kcal, rounded to the nearest whole number.

2Short answerMarked by AI

A friend says she wants to lose weight by eating only 1200 calories a day. Her TDEE is 2200 kcal, and her BMR is 1400 kcal. Explain why this is likely unsafe or unsustainable. Use the concept of BMR and energy balance in your answer.

Graded on Identifies that 1200 kcal is below BMR and explains why this is problematic · Proposes a safer alternative using the deficit concept

3Short answerMarked by AI

A person weighing 60 kg wants to lose weight. Their TDEE is 2200 kcal. They choose a 500 kcal deficit and set a protein target of 1.8 g per kg of body weight. Calculate their protein grams and the percentage of total calories that will come from protein. Is this percentage within a healthy range for weight loss (30–35% of total calories)? Show your calculations and explain.

Graded on Correctly calculates protein grams and percentage · Compares to the recommended range and offers a reasoned judgment

Lesson 60

Meal planning with labels

Selecting foods, reading labels, and assembling meals to meet targets.

15 min3 assessments

You have targets—calories, protein, fat, carbs—but the grocery store doesn’t sell ‘meals’. It sells ingredients with labels, and your job is to combine them into a day that hits your numbers without going over. This is where label reading meets arithmetic.

In the previous capstone you designed a day of eating on principle. Now you’ll turn that design into actual foods by using the Nutrition Facts panel for every item. The process has four passes: pick, check, adjust, and balance. Do them in order.

Steps
0/7

Walk through planning a single day for a 2000 kcal target with 25 % protein (125 g), 30 % fat (67 g), and 45 % carbs (225 g). You'll use labels from five common foods. Have the labels in front of you or look up the values in the table below the steps.

  1. Pick your base foods from each meal slot

    Choose one food per breakfast, lunch, dinner, and one snack. Write down the serving sizes you plan to eat. Example: breakfast oatmeal (dry 40 g), lunch turkey sandwich (2 slices bread, 100 g turkey, 30 g mayo), dinner spaghetti with meat sauce (85 g pasta dry, 150 g sauce, 80 g ground beef), snack Greek yogurt (200 g).

    Don’t skip a meal slot—you’ll end up guessing macros later.

  2. Record the Nutrition Facts per serving for each food

    For each ingredient, write down serving size (the label’s stated serving), calories, protein (g), total fat (g), total carbohydrate (g). If a label lists % Daily Value, ignore it—you need grams, not percentages. Use the table below for our example foods.

    FoodServingCalProteinFatCarbs
    Dry oatmeal40 g1505327
    White bread, 1 slice30 g803114
    Turkey breast, sliced50 g501010
    Mayo, full-fat15 g1000110
    Dry spaghetti85 g30010163
    Tomato sauce, jar125 g702212
    Ground beef, 80/2080 g24018180
    Greek yogurt, plain200 g16022012

    Labels list values per serving, not per package. If you eat 120 g of yogurt and the serving is 100 g, multiply by 1.2.

    Every item you listed has a row in your table with numbers for all four macros.

  3. Scale each food to the amount you actually eat

    Multiply the per-serving numbers by (your serving size / label serving size). For example, if you eat 40 g oatmeal and label serving is 40 g, multiplier is 1. If you eat 60 g oatmeal, multiplier = 60/40 = 1.5 → 150 cal × 1.5 = 225 cal. Do this for each row.

    Forgetting to scale is the most common error—one day of wrong macros comes from one un-scaled ingredient.

    Your scaled numbers feel reasonable: 300 cal for pasta, 160 cal for yogurt, etc.

  4. Sum up total day’s calories and macros

    Add all scaled calories together, then all protein, then all fat, then all carbs. Use a calculator or spreadsheet. For our example:

    • Oatmeal: 150 cal, 5g P, 3g F, 27g C
    • Sandwich (2 bread + turkey + mayo): 80×2 + 50 + 100 = 310 cal, (3×2)+10+0 = 16g P, (1×2)+1+11 = 14g F, (14×2)+0+0 = 28g C
    • Spaghetti dinner: 300+70+240 = 610 cal, 10+2+18 = 30g P, 1+2+18 = 21g F, 63+12+0 = 75g C
    • Yogurt snack: 160 cal, 22g P, 0g F, 12g C
    • Totals: 150+310+610+160 = 1230 cal; 5+16+30+22 = 73g P; 3+14+21+0 = 38g F; 27+28+75+12 = 142g C.

    Calories from labels are rounded—two different brands of the same food may differ by 5–10 cal. ±50 cal per day is fine.

    Your total calories are within 10 % of your target. For 2000 kcal target, 1800–2200 is acceptable for a first draft.

  5. Compare to your targets and identify gaps

    Targets: 2000 cal, 125g P, 67g F, 225g C. Our draft: 1230 cal, 73g P, 38g F, 142g C. Everything is low. So you need to add foods (or increase portions) to close the gap. Note which macro is furthest behind—here, protein is only 58 % of target, fat 57 %, carbs 63 %.

    Don’t try to fix all three at once. Address the biggest gap first.

    You have written down exactly how many grams of each macro you are short.

  6. Adjust by adding or swapping higher-macro foods

    Add foods that deliver the missing macros efficiently. For protein short by 52g, add a chicken breast (100g cooked: 165 cal, 31g P, 4g F, 0g C). For fat short by 29g, add olive oil to dinner (1 tbsp: 120 cal, 0g P, 14g F, 0g C). For carbs short by 83g, add a banana (100g: 89 cal, 1g P, 0g F, 23g C) and an extra slice of bread (80 cal, 3g P, 1g F, 14g C). Recalculate totals: 1230 + 165 + 120 + 89 + 80 = 1684 cal; 73+31+0+1+3 = 108g P; 38+4+14+0+1 = 57g F; 142+0+0+23+14 = 179g C. Still short of 2000 cal and all macros. Add more: another 50g chicken (83 cal, 15g P, 2g F), another tbsp oil (120 cal, 14g F), another banana (89 cal, 23g C). New totals: 1684+83+120+89 = 1976 cal; 108+15 = 123g P; 57+2+14 = 73g F; 179+23 = 202g C. Now very close. Small tweak: reduce oil to 1.5 tbsp total to hit 67g fat.

    Adding foods blindly can unbalance another macro. Recheck all four after every addition.

    Your adjusted totals are within 5 % of each target (2000±100 cal, 125±6g P, 67±3g F, 225±11g C).

  7. Balance across meals (optional, for satiety)

    Spread the macros so no single meal is extreme. Aim for 20–35g protein per meal, 10–30g fat, 40–80g carbs. Redistribute if needed—move some chicken to lunch, etc. Our final example: Breakfast: oatmeal + 1 scoop whey (120 cal, 24g P) → 270 cal, 29g P, 3g F, 27g C. Lunch: sandwich + side banana → 480 cal, 20g P, 15g F, 51g C. Dinner: 150g chicken + spaghetti dinner → 830 cal, 61g P, 30g F, 75g C. Snack: yogurt → 160 cal, 22g P, 0g F, 12g C. Totals: 1740 cal? Wait recalc: 270+480=750, +830=1580, +160=1740 cal. Still low. Add 2 tbsp peanut butter with yogurt (190 cal, 8g P, 16g F, 6g C). New totals: 1740+190=1930 cal, 29+20+61+22+8=140g P (too high), 3+15+30+0+16=64g F, 27+51+75+12+6=171g C (short). Need to adjust further—this illustrates the iterative nature. For this step just check balance not precision.

    Balancing is about feel, not hard rules. Don’t stress a 5g difference.

    No meal exceeds 40g fat or 100g carbs. Protein per meal is at least 15g.

Checklist
0/8

Meal planning with labels – field checklist

Print this or keep it open in a second tab while you build your day.

  • The Nutrition Facts panel gives per-serving values; you must scale by your actual portion size.
  • Calories are rounded to the nearest 5 or 10 kcal—don't expect exact sums.
  • Protein is listed in grams directly; fat and carbs include subcategories but you only need totals for planning.
  • Always sum all four macros (calories, protein, fat, carbs) together—fixing one in isolation can unbalance others.
  • A day's plan is an iterative loop: pick, check, adjust, balance. Expect 2–3 rounds.
  • Use a spreadsheet or a notes app; mental arithmetic leads to errors above 5 foods.
Go deeper

Wikipedia articles on meal preparation and meal replacements like Soylent. They give context on batch cooking and complete nutrition, but in this node we focus on label-based planning with whole foods.

Check yourself

Check your understanding of the process before you do it on your own.

1Put in orderChecked instantly

Put these steps for planning a day of eating from labels in the correct order. Start with the first action you take.

  • AScale each food's values to your portion size
  • BSum all scaled values to get day totals
  • CPick base foods for each meal slot
  • DRecord the Nutrition Facts per serving for each food
  • ECompare totals to your targets and identify gaps
  • FAdjust portions or add foods to close gaps
2Short answerMarked by AI

You are planning a 1800 kcal day with 120g protein, 60g fat, 180g carbs. After your first draft, you have 1400 kcal, 70g protein, 40g fat, 160g carbs. Which macro is most behind relative to its target, and name one specific food adjustment (with approximate macros) that would help close that gap first.

Graded on Identifies correct macro with reasoning · Suggests a food that targets that macro with plausible macros · Acknowledges secondary effects on other macros

Project

Plan one day for your own goal

Your task: plan a full day of eating (at least 4 meal/snack occasions) that meets the following targets:

  • Total calories: (your choice, between 1800 and 3000 kcal)
  • Protein: 20–30 % of calories
  • Fat: 25–35 % of calories
  • Carbs: the rest

Use real Nutrition Facts labels from items you have at home or look up brand-name products online (record the brand and serving size). You must include a minimum of 6 different foods. Produce a table showing each food, the label serving, your portion, scaled macros, and a final row with totals. Then write a short paragraph explaining which macro was hardest to meet and how you adjusted.

Deliverables:

  1. 1.A table as described (can be a photo of a handwritten table or a spreadsheet).
  2. 2.A paragraph of 100–200 words explaining your adjustments.
  3. 3.An overall statement: whether your final plan is within 5 % of each target (yes/no for each macro).

Deliverables

  • 01Complete food table with servings and scaled macros
  • 02100–200 word explanation of adjustments
  • 03Statement of accuracy per macro
ProjectMarked by AI

Submit your completed day plan as described in the project brief. Include the table, explanation, and accuracy statement.

Graded on Table completeness and accuracy · Explanation of adjustment process · Accuracy relative to self-chosen targets

Lesson 61

Defending your choices

Justifying food selections using principles from the course: nutrient density, balance, evidence.

10 min2 assessments

You've designed a day of eating. Now someone asks: Why that? A friend, a client, a headline, or your own doubt. Defending a food choice isn't arguing — it's explaining the reasoning that led to it, using the same principles you've already applied: nutrient density, energy balance, and evidence.

You're not defending yourself. You're defending the decision. And the best defense is a short chain: Goal → Principle → Food → Portion. For example: "I chose oatmeal for breakfast because I need sustained energy until lunch (goal), and oatmeal has a low glycemic index with 4 g of fiber per serving (principle: nutrient density). I measured 40 g dry, which gives 150 kcal — fitting my 400 kcal breakfast budget (principle: energy balance)."

That's it. Four links. No opinion, no emotion. If the evidence changes — a new study, a different goal — the chain updates. That's not weakness; that's how science works.

  • A defendable choice is justified by a chain: Goal → Principle → Food → Portion.
  • Nutrient density means more vitamins, minerals, and fiber per calorie — not fewer calories.
  • Energy balance is about fitting the food into your daily calorie budget, not about 'good' or 'bad' foods.
  • Evidence means citing a source you can name (study, guideline, or your tracked data), not a feeling or a fad.
  • A good defense sounds like explanation, not argument — it invites discussion, not debate.
Say it

Listen to each phrase, then say it twice out loud. These are the actual sentences you'll use when someone asks about your food choices.

I chose this because it fits my calorie target for the meal.

I chose this because it fits my calorie target for the meal.

/eye chohz thihs bih-kawz it fits my kal-oh-ree tar-get for the meel/

This has more fiber and vitamins per calorie than the alternative.

This has more fiber and vitamins per calorie than the alternative.

/thihs haz mor fye-ber and vy-tah-mins pur kal-oh-ree than the al-ter-nuh-tiv/

The evidence shows that whole grains reduce heart disease risk.

The evidence shows that whole grains reduce heart disease risk.

/thee ev-ih-dents showz that hohl graynz rih-doos hart dih-zeez risk/

Can you show me the study that supports that claim?

Can you show me the study that supports that claim?

/kan yoo show me the stud-ee that suh-portz that klaym/

Role-play

You're at a family dinner. Your aunt notices you chose a smaller portion of pasta and an extra serving of vegetables. She says, "Why are you eating so little? You're already thin!"

You are the you; you're talking to the aunt.

Goal: Explain your choice using one of the four defense chains (Goal → Principle → Food → Portion) without sounding defensive or criticizing her eating.

Check yourself

Check your understanding of defending food choices.

1Multiple choiceChecked instantly

A friend says: 'Carbs are bad for you; I cut them all out.' Which response best defends your own choice to include oats in your breakfast?

  • A"Actually, carbs are essential for brain function."
  • B"I include oats because my goal is sustained morning energy, and their fiber and low glycemic index fit my 400 kcal breakfast budget."
  • C"You should read the latest research on carbs."
  • D"Well, I need energy for my workout."
2Short answerMarked by AI

Your coworker says they're trying a new 'detox tea' because 'it flushes out toxins.' Using the principles from this course, write a 2–4 sentence response that defends your choice not to use it, without attacking theirs.

Graded on Identifies the missing evidence chain · Applies a course principle (nutrient density, energy balance, or evidence) · Tone is non-confrontational

Go deeper

For an example of how to defend a choice with evidence, see how the characters in 'How to Train Your Dragon' defend their unconventional decisions with reasoning — not just emotion.